Related Experiment Video
Updated: Nov 19, 2025


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Risk factors for subsequent vertebral fracture after acute osteoporotic vertebral fractures
Hiroyuki Inose1, Tsuyoshi Kato2,3, Shoichi Ichimura4
1Department of Orthopaedic and Trauma Research, Graduate School, Tokyo Medical and Dental University, 1-5-45 Yushima, Bunkyo-Ku, Tokyo, 113-8519, Japan. inose.orth@tmd.ac.jp.

Purpose:
To investigate the incidence and characteristics of subsequent vertebral fracture after osteoporotic vertebral fractures (OVFs) and identify risk factors for subsequent vertebral fractures.
Methods:
This post-hoc analysis from a prospective randomized multicenter trial included 225 patients with a 48-week follow-up period. Differences between the subsequent and non-subsequent fracture groups were analyzed.
Results:
Of the 225 patients, 15 (6.7%) had a subsequent fracture during the 48-week follow-up. The annual incidence of subsequent vertebral fracture after fresh OVFs in women aged 65-85 years was 68.8 per 1000 person-years. Most patients (73.3%) experienced subsequent vertebral fractures within 6 months. At 48 weeks, European Quality of Life-5 Dimensions, the Japanese Orthopedic Association Back Pain Evaluation Questionnaire pain-related disorder, walking ability, social life function, and lumbar function scores were significantly lower, while the visual analog scale (VAS) for low back pain was higher in patients with subsequent fracture. Cox proportional hazards analysis showed that a VAS score ≥ 70 at 0 weeks was an independent predictor of subsequent vertebral fracture. After adjustment for history of previous fracture, there was a ~ 67% reduction in the risk of subsequent vertebral fracture at the rigid-brace treatment.
Conclusion:
Women with a fresh OVF were at higher risk for subsequent vertebral fracture within the next year. Severe low back pain and use of soft braces were associated with higher risk of subsequent vertebral fractures. Therefore, when treating patients after OVFs with these risk factors, more attention may be needed for the occurrence of subsequent vertebral fractures.
Level Of Evidence:
III.
More Related Videos
 07:12
Semiautomated Longitudinal Microcomputed Tomography-based Quantitative Structural Analysis of a Nude Rat Osteoporosis-related Vertebral Fracture Model
Published on: September 28, 2017
 06:58
Method and Instrumented Fixture for Femoral Fracture Testing in a Sideways Fall-on-the-Hip Position
Published on: August 17, 2017
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:40
Bone Remodeling
 01:16
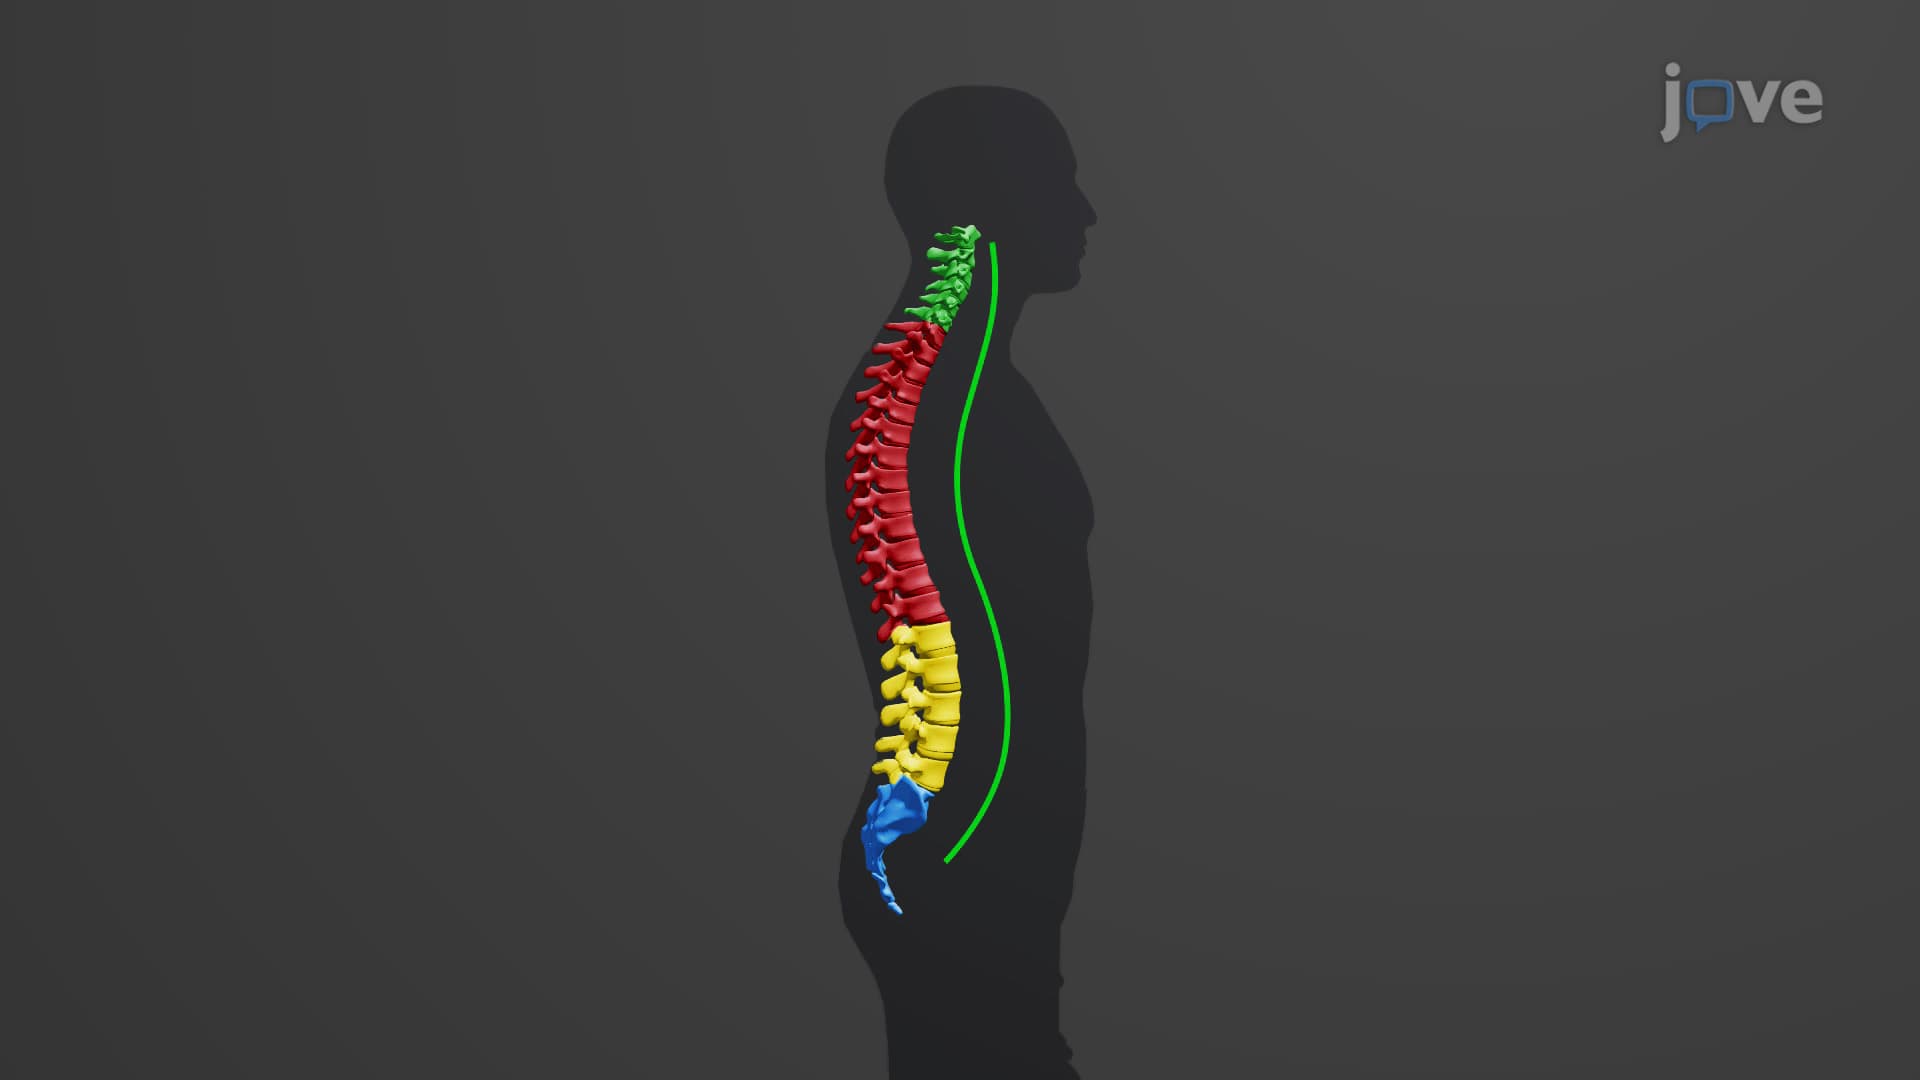
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...