Related Experiment Video
Updated: Nov 19, 2025


Rapid Point-of-Care Assay of Enoxaparin Anticoagulant Efficacy in Whole Blood
Published on: October 12, 2012
Pharmacokinetics and dialytic clearance of apixaban during in vitro continuous renal replacement therapy
Lauren Andrews1, Scott Benken1, Xing Tan1
1College of Pharmacy, University of Illinois at Chicago, 833 South Wood Street, Room 164 (M/C 886),, Chicago, IL, 60612, USA.

Background:
To evaluate the transmembrane clearance (CLTM) of apixaban during modeled in vitro continuous renal replacement therapy (CRRT), assess protein binding and circuit adsorption, and provide initial dosing recommendations.
Methods:
Apixaban was added to the CRRT circuit and serial pre-filter bovine blood samples were collected along with post-filter blood and effluent samples. All experiments were performed in duplicate using continuous veno-venous hemofiltration (CVVH) and hemodialysis (CVVHD) modes, with varying filter types, flow rates, and point of CVVH replacement fluid dilution. Concentrations of apixaban and urea were quantified via liquid chromatography-tandem mass spectrometry. Plasma pharmacokinetic parameters for apixaban were estimated via noncompartmental analysis. CLTM was calculated via the estimated area under the curve (AUC) and by the product of the sieving/saturation coefficient (SC/SA) and flow rate. Two and three-way analysis of variance (ANOVA) models were built to assess the effects of mode, filter type, flow rate, and point of dilution on CLTM by each method. Optimal doses were suggested by matching the AUC observed in vitro to the systemic exposure demonstrated in Phase 2/3 studies of apixaban. Linear regression was utilized to provide dosing estimations for flow rates from 0.5-5 L/h.
Results:
Mean adsorption to the HF1400 and M150 filters differed significantly at 38 and 13%, respectively, while mean (± standard deviation, SD) percent protein binding was 70.81 ± 0.01%. Effect of CVVH point of dilution did not differ across filter types, although CLTM was consistently significantly higher during CRRT with the HF1400 filter compared to the M150. The three-way ANOVA demonstrated improved fit when CLTM values calculated by AUC were used (adjusted R2 0.87 vs. 0.52), and therefore, these values were used to generate optimal dosing recommendations. Linear regression revealed significant effects of filter type and flow rate on CLTM by AUC, suggesting doses of 2.5-7.5 mg twice daily (BID) may be needed for flow rates ranging from 0.5-5 L/h, respectively.
Conclusion:
For CRRT flow rates most commonly employed in clinical practice, the standard labeled 5 mg BID dose of apixaban is predicted to achieve target systemic exposure thresholds. The safety and efficacy of these proposed dosing regimens warrants further investigation in clinical studies.

Related Concept Videos
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:06
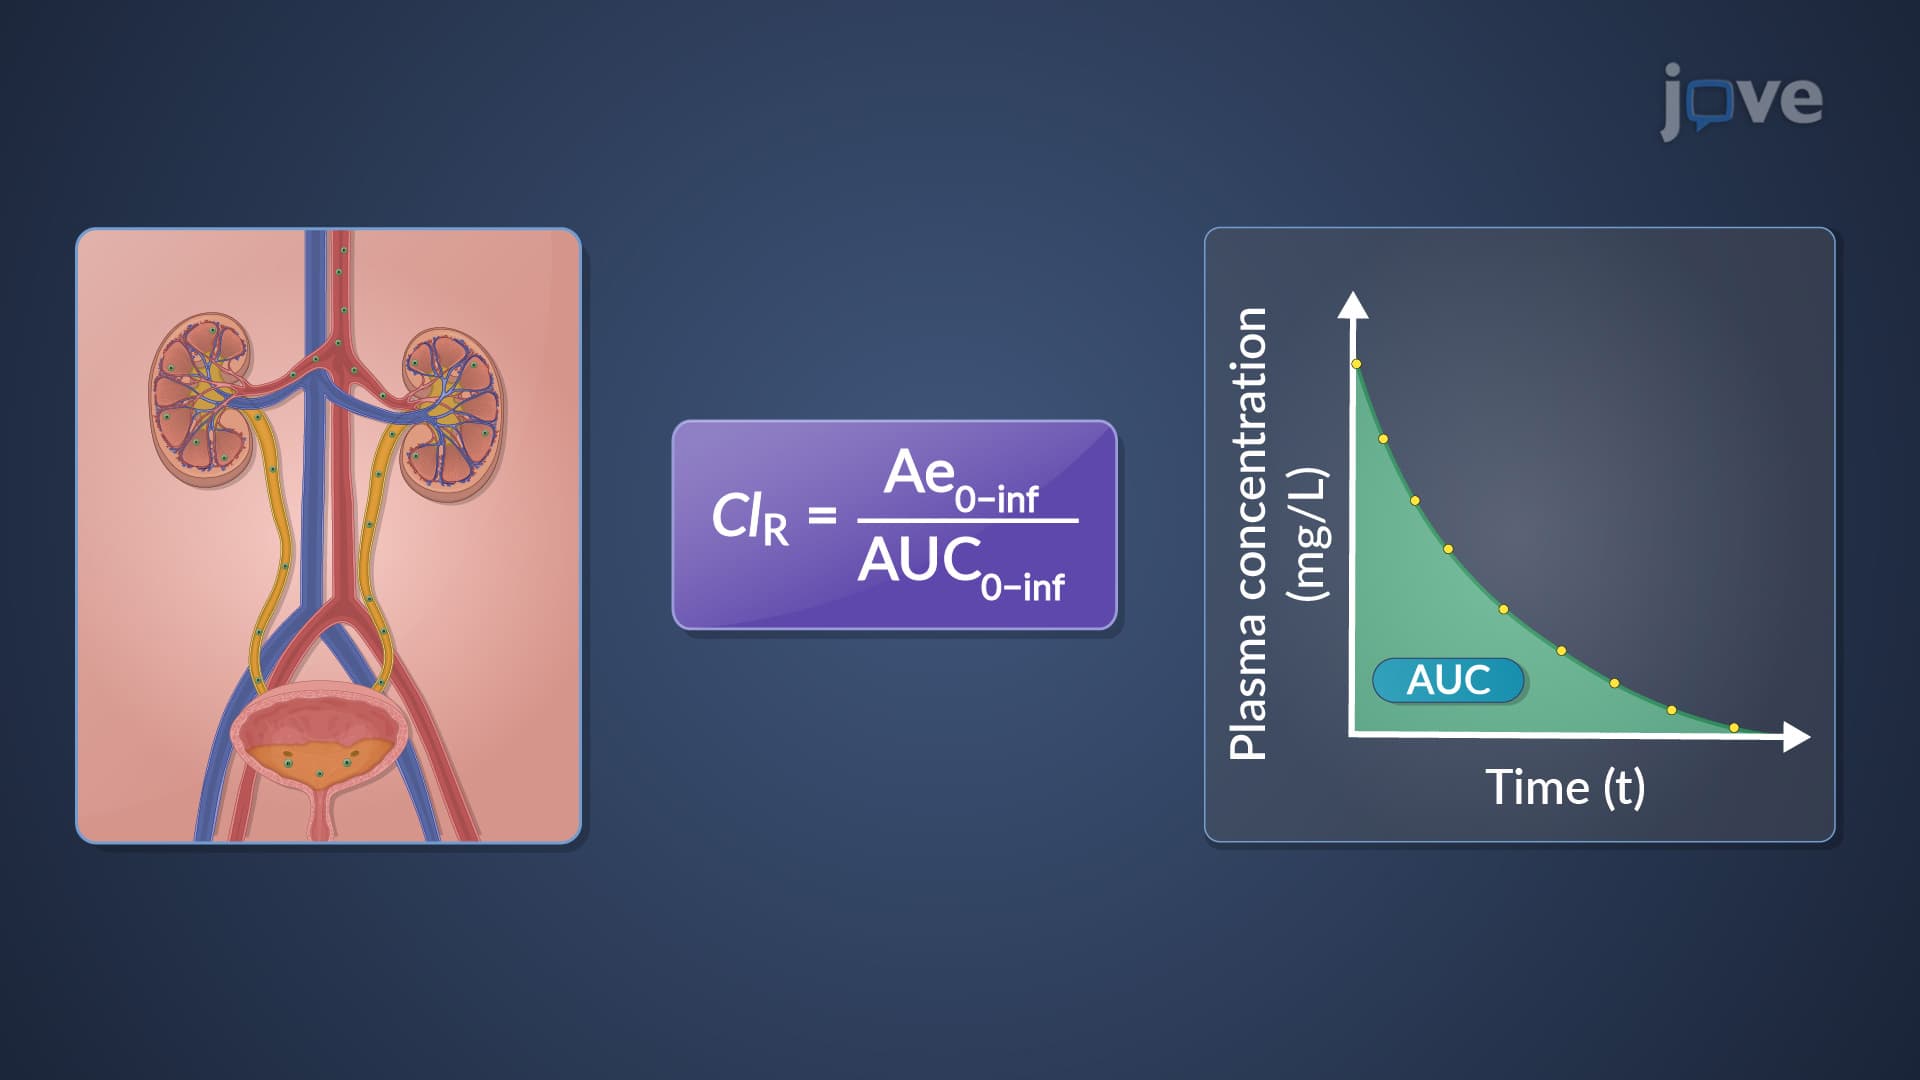
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:30
Continuous Renal Replacement Therapy
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:31
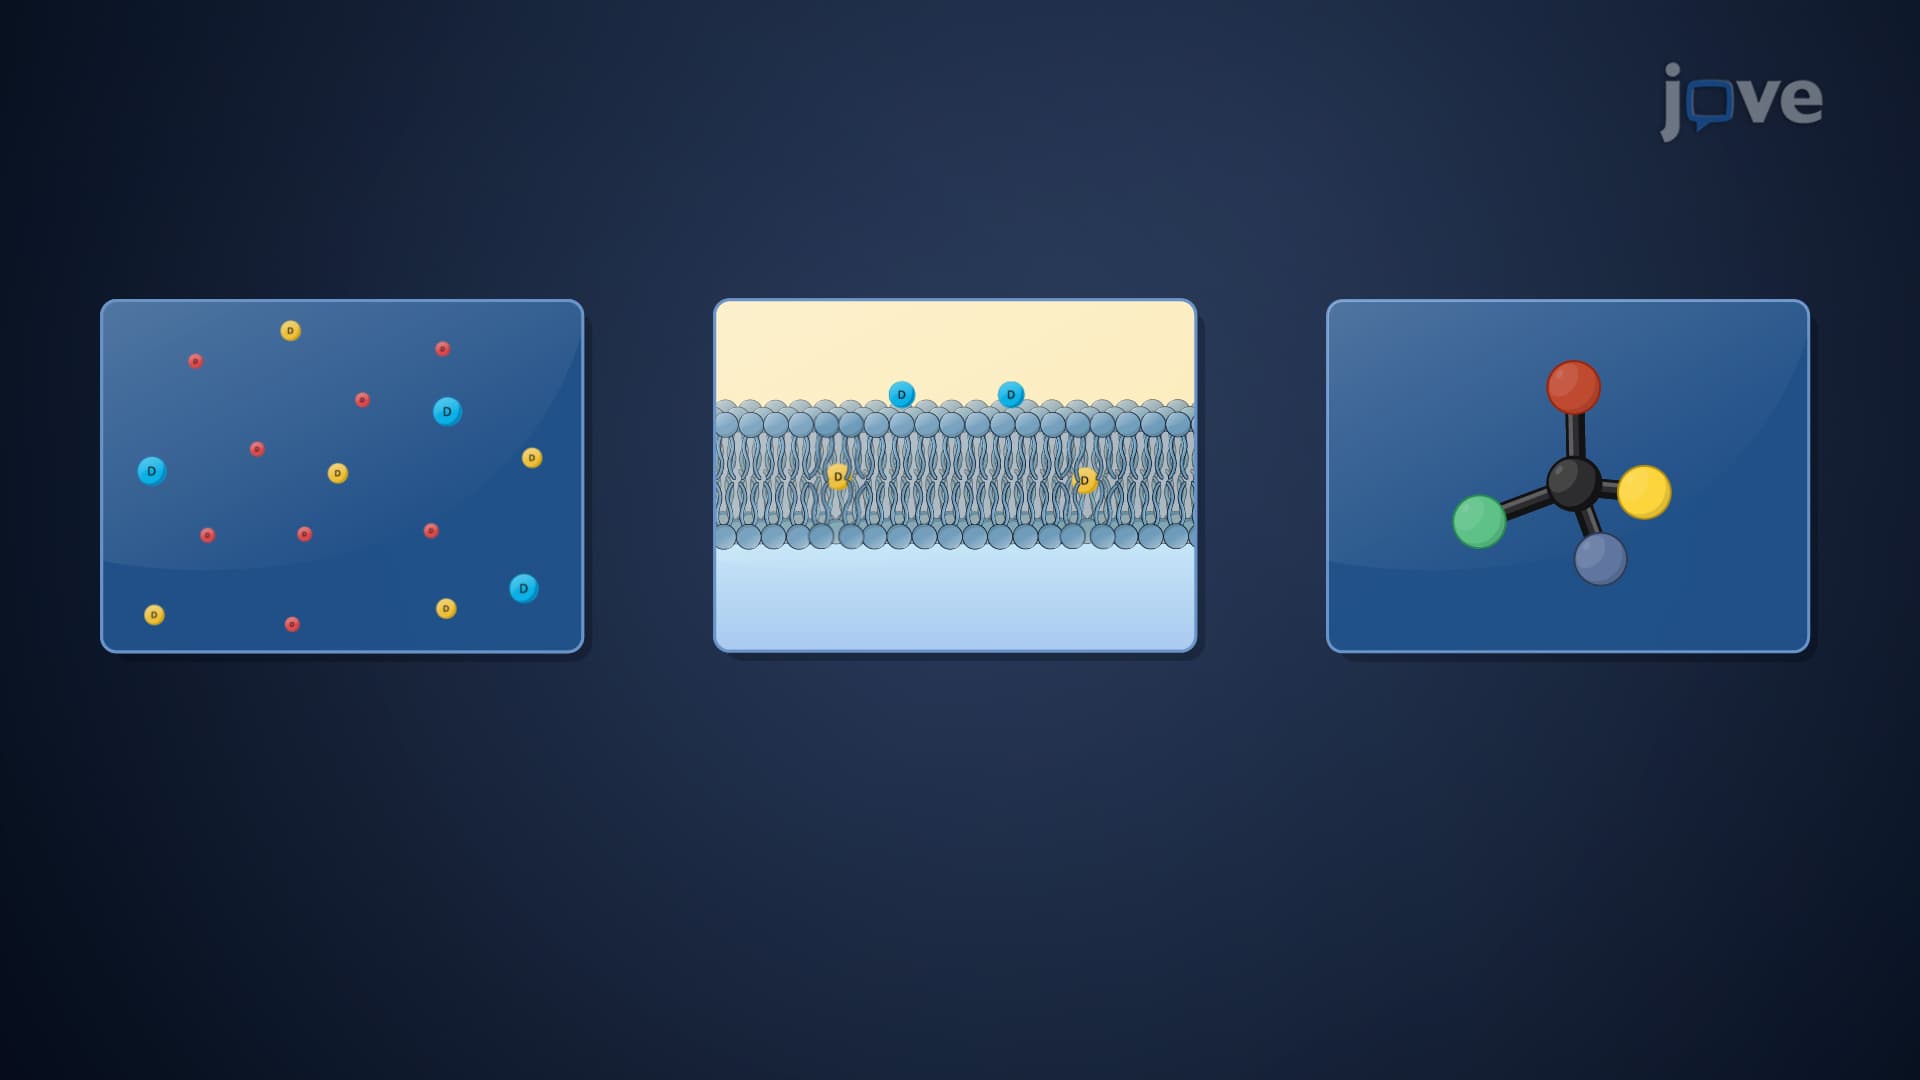
Factors Affecting Renal Clearance: Drug's Physicochemical Properties and Plasma Levels
One important factor is the drug's molecular size. The kidneys readily excrete smaller molecules below 300 Daltons (Da). On the other hand, molecules weighing between 300 and 500 Da are excreted through both urine and bile. Larger molecules above 500 Da tend to be excreted...
 01:08
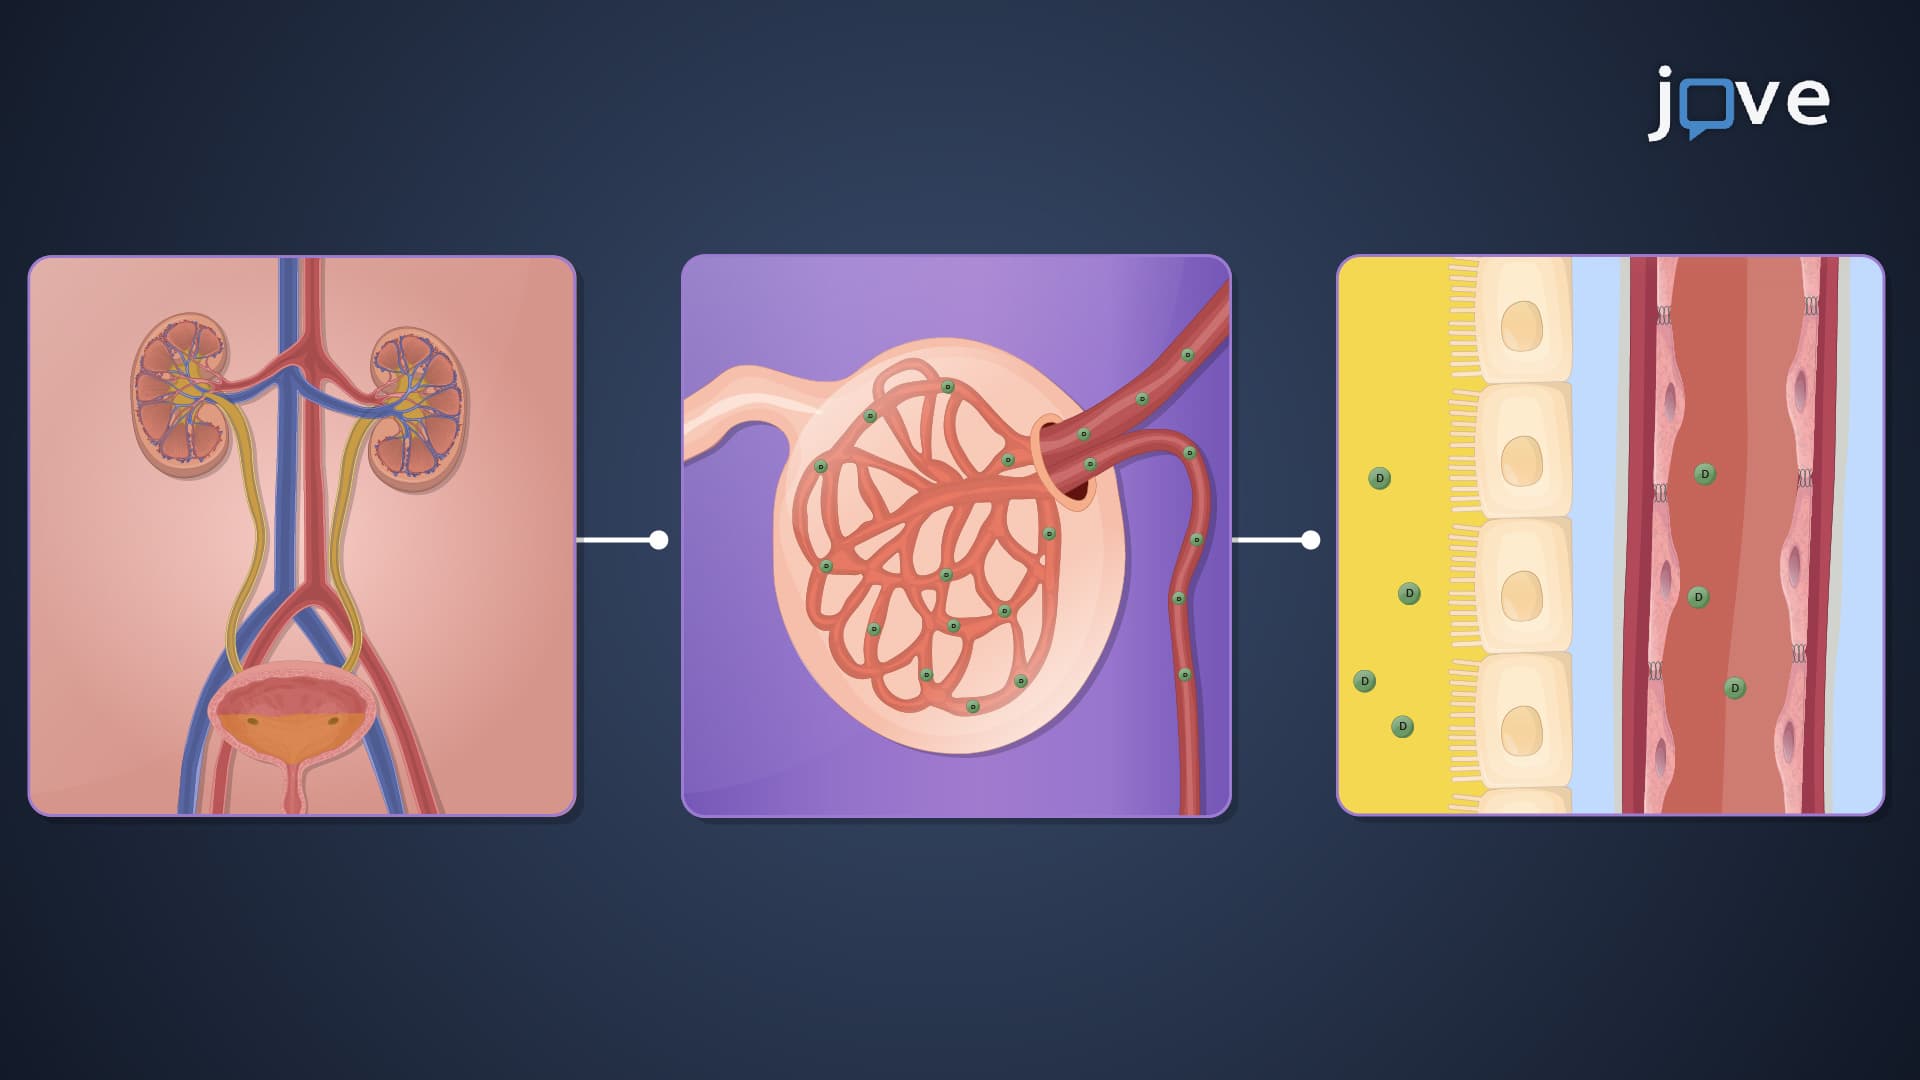
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...