Related Experiment Video
Updated: Nov 19, 2025

Establishing Human Lung Organoids and Proximal Differentiation to Generate Mature Airway Organoids
Published on: March 23, 2022
A fatal outcome from SARS-CoV-2 infection: One case report of a young man with multiple organ damage
Yingting Zeng1, Xiaoyue Zhou2, Yadong Gang1
1Department of Radiology, Zhongnan Hospital of Wuhan University, Wuhan, Hubei 430071, China.

Insights
This case study highlights how coronavirus disease 2019 (COVID-19) can cause severe systemic inflammation and rapid organ damage, leading to acute respiratory distress syndrome (ARDS). It emphasizes the critical condition progression in some COVID-19 patients.
Area of Science:
- Infectious Diseases
- Critical Care Medicine
- Pathology
Background:
- Coronavirus disease 2019 (COVID-19), caused by SARS-CoV-2, emerged globally in late 2019.
- A previously healthy 36-year-old male presented with persistent fever, weakness, and diarrhea.
Observation:
- The patient tested positive for SARS-CoV-2.
- Laboratory results indicated systemic inflammation and multi-organ damage.
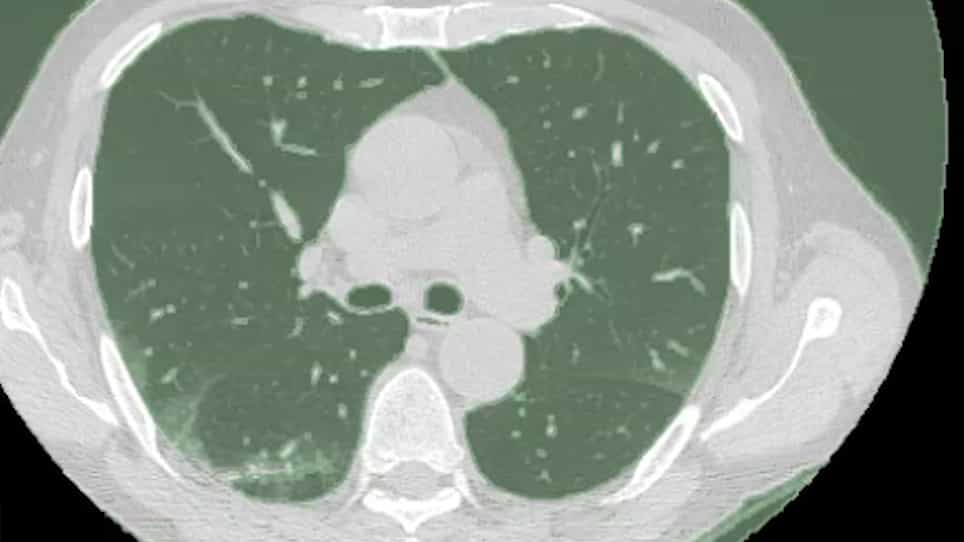
- Chest radiographs showed dynamic lung lesions consistent with clinical deterioration.
Findings:
- The patient rapidly progressed to severe acute respiratory distress syndrome (ARDS).
- Systemic inflammation and multi-organ damage, particularly pancreatic damage, were observed.
- The patient died on hospital day 13.
Implications:
- SARS-CoV-2 infection can trigger severe inflammatory responses and multi-organ damage.
- COVID-19 patients can experience rapid clinical deterioration, especially when critically ill.
- Close monitoring and understanding of inflammatory markers are crucial for managing severe COVID-19 cases.
Abstract:
The coronavirus disease 2019 (COVID-19) first emerged in Wuhan, China on December 2019 and has become a severe public health issue worldwide. A 36-year-old man was presented to the hospital staff with a fever that had already persisted for a three-day period, general weakness and diarrhea. He had no chronic diseases and was tested positive for COVID-19 with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) nucleic acid. During his hospitalization, several abnormal indicators appeared in his laboratory tests, which implied systemic inflammation and multiple organ damage. A series of chest radiographs monitored the dynamic process of lung lesions, which could predict the clinical changes of the patient. His condition deteriorated rapidly, resulting in death due to acute respiratory distress syndrome (ARDS) on hospital day 13. The case indicates that inflammatory response may appear in people infected with SARS-CoV-2 and may lead to multiple organ damage (especially pancreatic damage). When a COVID-19 patient is entering into the critical stage, their condition could rapidly deteriorate.
More Related Videos
 08:05
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
 08:41
Live Imaging and Quantification of Viral Infection in K18 hACE2 Transgenic Mice Using Reporter-Expressing Recombinant SARS-CoV-2
Published on: November 5, 2021
Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:29
Pneumonia II: Pathophysiology
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:30
Acute Respiratory Failure-III