Related Experiment Video
Updated: Nov 19, 2025
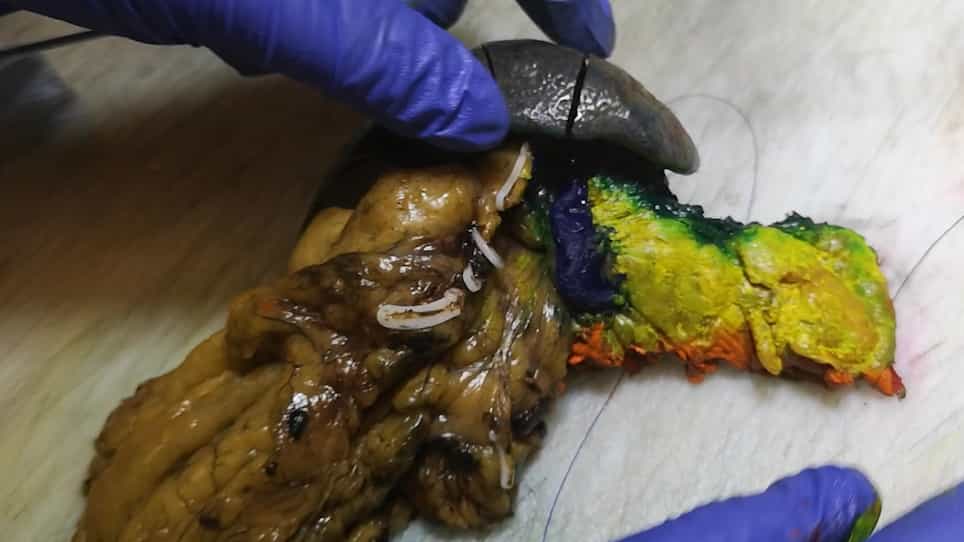
DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Prognostic Factors in Patients With Borderline Resectable Pancreatic Ductal Adenocarcinoma Undergoing Resection
Weizheng Ren1,2,3, Dimitrios Xourafas2,3, Stanley W Ashley2,3
1Faculty of Hepato-Pancreato-Biliary Surgery, First Center, 104607Chinese PLA General Hospital, Beijing, China.

Background:
Neoadjuvant treatment (NT) has become standard in the management of borderline resectable pancreatic cancer (BR-PDAC), improving prognosis. The primary mechanism for this improvement remains unclear.
Methods:
Clinicopathological data of patients with BR-PDAC who underwent resection between January 2008 and December 2018 at a single institution were retrospectively reviewed. Univariable and multivariate analyses were used to compare survival between patients who received NT vs. those who underwent upfront resection (UR).
Results:
A total of 138 patients were included, 64 underwent UR and 74 NT. Neoadjuvant treatment resulted in higher margin-negative (R0) resection rate (68.9%) than UR (43.8%, P = .005). Neoadjuvant treatment was associated with improved overall survival (OS, P = .009) and progression-free survival (PFS, P = .027). R0 resection was also associated with improved OS (P < .001) and PFS (P < .001). On multivariable analysis, when adjusting for clinically relevant variables without considering R status, NT was an independent predictor for improved OS (P = .046) and PFS (P = .040). When additionally accounting for margin status, R0 was an independent predictor for improved OS (P < .001) and PFS (P < .001), while NT was not. Subgroup analysis, stratified by margin status, revealed that NT was not an independent predictor for OS or PFS for either subgroup.
Discussion:
Neoadjuvant treatment is associated with improved OS and PFS in patients with BR-PDAC; however, this effect is outweighed by margin status. These results suggest that the primary benefit of NT was dependent on facilitating R0 resection. Upfront resection might remain a valid treatment option if R0 resection could be accurately predicted.
