Related Experiment Video
Updated: Nov 18, 2025
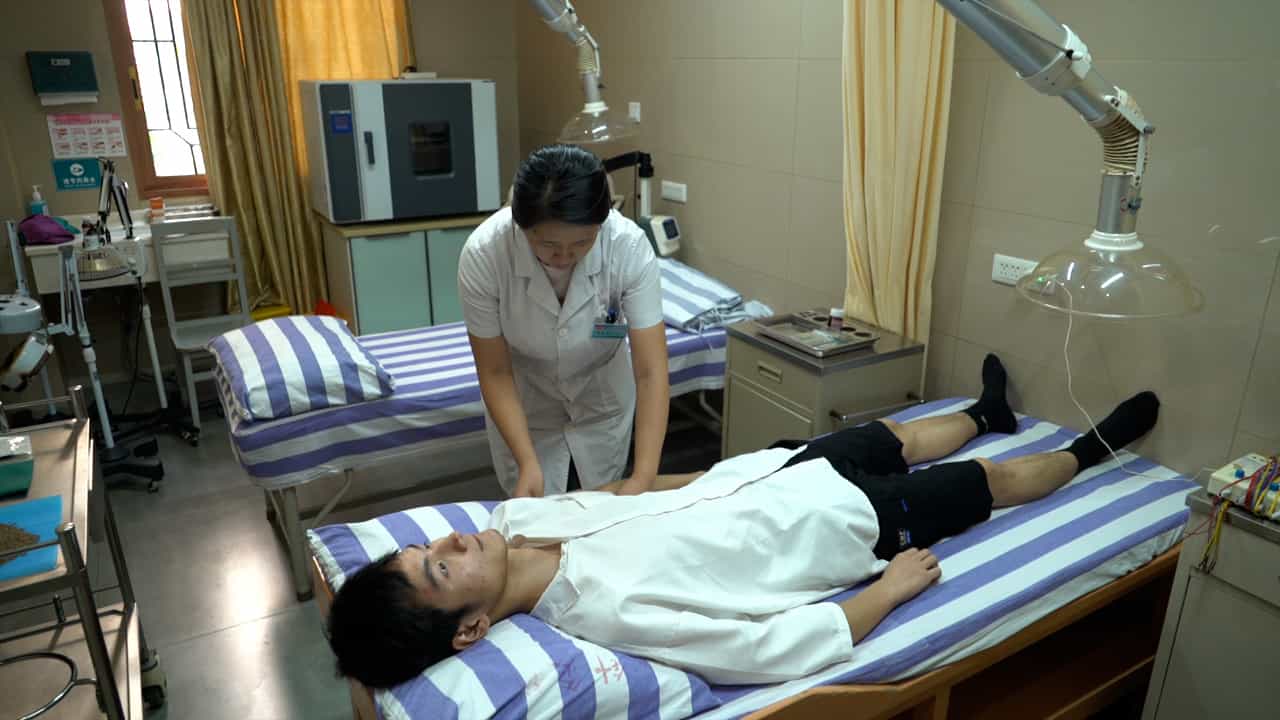

Electroacupuncture Combined with Chinese Medicine Ironing Therapy for Functional Constipation
Published on: July 5, 2024
Evidence-based clinical practice guidelines for irritable bowel syndrome 2020
Shin Fukudo1,2, Toshikatsu Okumura3, Masahiko Inamori3
1Guidelines Committee for Creating and Evaluating the "Evidence-Based Clinical Practice Guidelines for Irritable Bowel Syndrome", The Japanese Society of Gastroenterology, 6F Shimbashi i-MARK Building, 2-6-2 Shimbashi, Minato-ku, Tokyo, 105-0004, Japan. sfukudo@med.tohoku.ac.jp.

Managing irritable bowel syndrome (IBS) has attracted international attention because single-agent therapy rarely relieves bothersome symptoms for all patients. The Japanese Society of Gastroenterology (JSGE) published the first edition of evidence-based clinical practice guidelines for IBS in 2015. Much more evidence has accumulated since then, and new pharmacological agents and non-pharmacological methods have been developed. Here, we report the second edition of the JSGE-IBS guidelines comprising 41 questions including 12 background questions on epidemiology, pathophysiology, and diagnostic criteria, 26 clinical questions on diagnosis and treatment, and 3 questions on future research. For each question, statements with or without recommendations and/or evidence level are given and updated diagnostic and therapeutic algorithms are provided based on new evidence. Algorithms for diagnosis are requisite for patients with chronic abdominal pain or associated symptoms and/or abnormal bowel movement. Colonoscopy is indicated for patients with one or more alarm symptoms/signs, risk factors, and/or abnormal routine examination results. The diagnosis is based on the Rome IV criteria. Step 1 therapy consists of diet therapy, behavioral modification, and gut-targeted pharmacotherapy for 4 weeks. For non-responders, management proceeds to step 2 therapy, which includes a combination of different mechanistic gut-targeted agents and/or psychopharmacological agents and basic psychotherapy for 4 weeks. Step 3 therapy is for non-responders to step 2 and comprises a combination of gut-targeted pharmacotherapy, psychopharmacological treatments, and/or specific psychotherapy. These updated JSGE-IBS guidelines present best practice strategies for IBS patients in Japan and we believe these core strategies can be useful for IBS diagnosis and treatment globally.
Managing irritable bowel syndrome (IBS) has attracted international attention because single-agent therapy rarely relieves bothersome symptoms for all patients. The Japanese Society of Gastroenterology (JSGE) published the first edition of evidence-based clinical practice guidelines for IBS in 2015. Much more evidence has accumulated since then, and new pharmacological agents and non-pharmacological methods have been developed. Here, we report the second edition of the JSGE-IBS guidelines comprising 41 questions including 12 background questions on epidemiology, pathophysiology, and diagnostic criteria, 26 clinical questions on diagnosis and treatment, and 3 questions on future research. For each question, statements with or without recommendations and/or evidence level are given and updated diagnostic and therapeutic algorithms are provided based on new evidence. Algorithms for diagnosis are requisite for patients with chronic abdominal pain or associated symptoms and/or abnormal bowel movement. Colonoscopy is indicated for patients with one or more alarm symptoms/signs, risk factors, and/or abnormal routine examination results. The diagnosis is based on the Rome IV criteria. Step 1 therapy consists of diet therapy, behavioral modification, and gut-targeted pharmacotherapy for 4 weeks. For non-responders, management proceeds to step 2 therapy, which includes a combination of different mechanistic gut-targeted agents and/or psychopharmacological agents and basic psychotherapy for 4 weeks. Step 3 therapy is for non-responders to step 2 and comprises a combination of gut-targeted pharmacotherapy, psychopharmacological treatments, and/or specific psychotherapy. These updated JSGE-IBS guidelines present best practice strategies for IBS patients in Japan and we believe these core strategies can be useful for IBS diagnosis and treatment globally.

Related Concept Videos
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:17
Irritable Bowel Syndrome I: Introduction
IBS is a chronic condition that can persist over a long period or recur frequently.
The pathogenesis of IBS involves a complex interplay of the following factors:
Altered...
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...