[Cone-beam CT evaluation of temporomandibular joint in skeletal class Ⅱ female adolescents with different vertical patterns]
Related Experiment Video
Updated: Nov 18, 2025
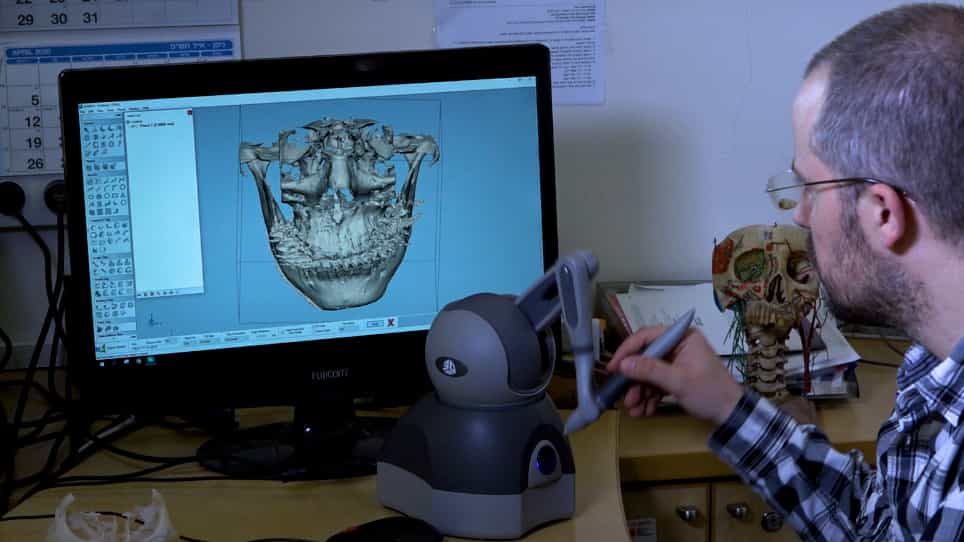
Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
1Department of Orthodontics, Peking University School and Hospital of Stomatology & National Clinical Research Center for Oral Diseases & National Engineering Laboratory for Digital and Material Technology of Stomatology & Beijing Key Laboratory of Digital Stomatology, Beijing 100081, China.

Objective:
To compare temporomandibular joint (TMJ) morphology and position among skeletal class Ⅱ female adolescents with different vertical patterns using cone-beam CT (CBCT).
Methods:
Diagnostic CBCT images of 80 female patients aged 11 to 14 years were assessed retrospectively. According to subspinale-nasion-supramental angle (ANB) and Frankfort horizontal plane-gonion-gnathion angle (FH-GoGn), the participants were categorized into four groups (20 subjects each), i.e. class Ⅰ normal angle (group 1, 0°≤ANB < 4°, 22°≤FH-GoGn≤32°), class Ⅱ low (group 2, ANB≥4°, FH-GoGn < 22°), normal (group 3, ANB≥4°, 22°≤FH-GoGn≤32°) and high angle (group 4, ANB≥4°, FH-GoGn > 32°). Cephalometrics, morphology and position of TMJ were measured in Dolphin software. Using paired-samples t test to analyze TMJ symmetry, One-way analysis of variance (One-way ANOVA) and Chi-square tests to detect differences among the groups. The correlations between cephalometrics and TMJ measurements were also analysed within the skeletal class Ⅱ patients.
Results:
(1) Analysing TMJ morphologic symmetry, some measurements differed statistically although the mean diffe-rences were negligibly relative to their values. No statistically significant difference was found among the groups though group 4 showed the highest probability of condylar position asymmetry (65%). (2) Comparing group 1 with group 3, statistical difference was found in condylar position (χ2=6.936, P < 0.05) instead of morphologic measurements. Anterior and concentric condylar position were more frequently observed in group 1, yet posterior position was more prevalent in group 3. (3) In groups 2, 3, and 4, statistically, group 2 had the deepest glenoid fossa depth (H2&4=10.517, P=0.002), biggest superior (LSD-t2&3=3.408, LSD-t2&4=5.369, P < 0.001) and lateral (LSD-t2&3=2.767, LSD-t2&4=3.350, P=0.001) joint spaces, whereas group 4 showed the shortest condylar long axis diameter (H2&4=13.374, P < 0.001), largest glenoid fossa vertical distance (LSD-t2&4=4.561, P < 0.001, LSD-t3&4=2.713, P=0.007), smallest medial (LSD-t2&4=-4.083, P < 0.001) and middle (LSD-t2&4=-4.201, P < 0.001) joint spaces. The posterior condylar position proportion gradually increased from groups 2 to 3 to 4. Correlation analysis revealed ANB correlated with anterior joint space positively (r=0.270, P=0.037) and condylar long axis angle negatively (r=-0.296, P=0.022). FH-GoGn correlated with superior (r=-0.488, P < 0.001), posterior (r= -0.272, P=0.035), mesial (r=-0.390, P=0.002), middle (r=-0.425, P=0.001), and lateral (r=-0.331, P=0.010) joint spaces, articular eminence inclination (r=-0.259, P=0.046), as well as condylar long axis diameter (r=-0.327, P=0.011) negatively, and glenoid fossa depth (r=0.370, P=0.004) positively.
Conclusion:
TMJ characteristics of skeletal class Ⅱ sagittal pattern mainly reflected in condylar position rather than morphology. TMJs of different vertical patterns differed more in joint spaces, position of condyle and glenoid fossa than in morphologic measurements. Vertical position of glenoid fossa and proportion of posterior condyle increased gradually from hypodivergent to hyperdivergent. Highest glenoid fossa position, maximum ratio of posterior positioned condyle, smallest joint spaces, shallowest glenoid fossa depth, and narrowest condylar long axis diameter were found in skeletal class Ⅱ high angle group, which means that patients with this facial type have considerable joint instable factors, and we should especially pay attention when orthodontic treatment is carried out on them.


Related Concept Videos
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:27
Imaging Studies III: Computed Tomography
 01:27
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:18
Classification of Bones
Long and Short Bones
The appendicular skeleton, particularly the upper and lower limbs, is primarily made of long and short bones. The...
 01:21
Tooth Anatomy
The Crown, Neck, and Root
The visible part of the tooth is referred to as the crown. It's covered by enamel, the hardest substance in the human body. The crown is uniquely shaped for each type of tooth, allowing for different functions such as cutting, tearing, or...