Related Experiment Video
Updated: Nov 18, 2025
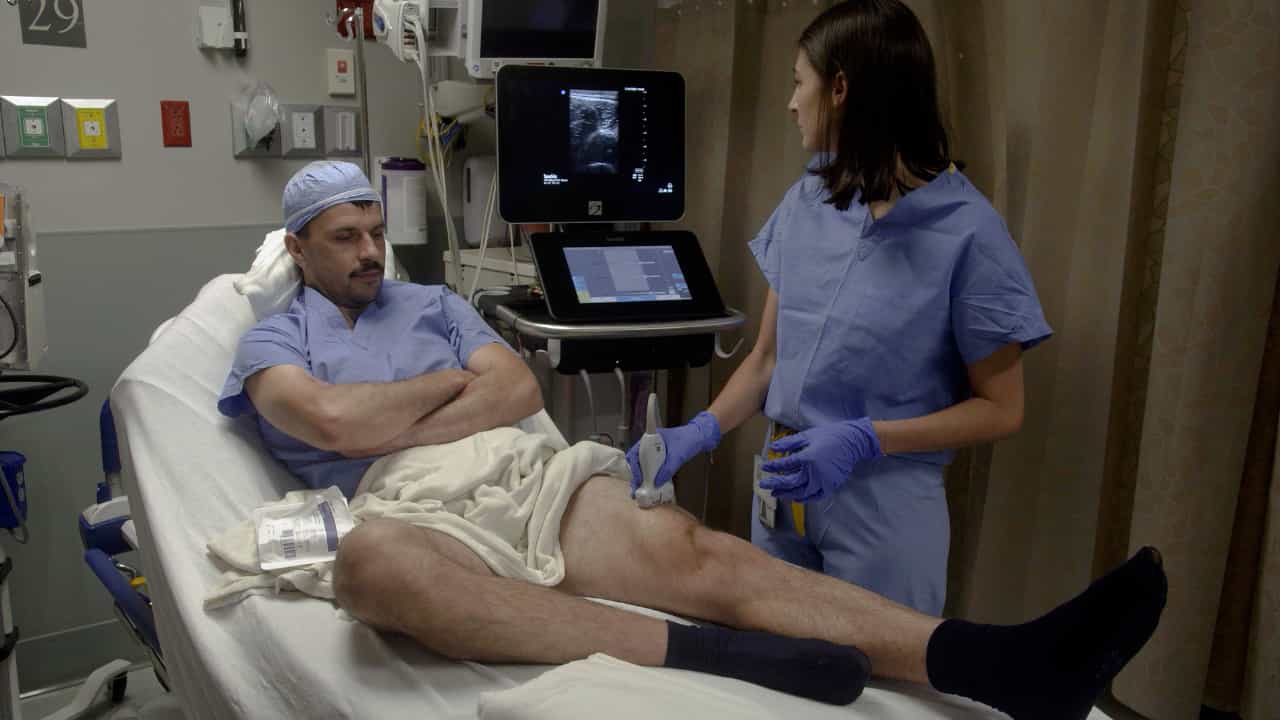
Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Impact of Frailty on Clinical Outcomes after Carotid Artery Revascularization
Ava D Mandelbaum1, Joseph Hadaya1, Jesus G Ulloa2
1Cardiovascular Outcomes Research Laboratories (CORELAB), Division of Cardiac Surgery, David Geffen School of Medicine, University of California Los Angeles, Los Angeles, CA.

Background:
Frailty has been increasingly recognized as an important risk factor for vascular procedures. To assess the impact of frailty on clinical outcomes and resource utilization in patients undergoing carotid revascularization using a national cohort.
Methods:
The 2005-2017 National Inpatient Sample was used to identify patients who underwent carotid endarterectomy (CEA) or carotid stenting (CAS). Patients were classified as frail using diagnosis codes defined by the Johns Hopkins Adjusted Clinical Groups frailty indicator. Multivariable regression was used to evaluate associations between frailty and in-hospital mortality, postoperative stroke, myocardial infarction (MI), hospitalization costs, and length of stay (LOS).
Results:
Of 1,426,343 patients undergoing carotid revascularization, 59,158 (4.2%) were identified as frail. Among frail patients, 79.4% underwent CEA and 20.6% underwent CAS. Compared to CEA, a greater proportion of patients undergoing CAS were frail (6.0% vs. 3.8%, P < 0.001). Compared to the nonfrail cohort, frail patients had higher rates of mortality (2.2% vs. 0.5%, P < 0.001), postoperative stroke (2.6% vs. 1.0%, P < 0.001), MI (2.2% vs. 0.8%, P < 0.001), and stroke/death (4.4% vs. 1.4%, P < 0.001). After adjustment, frailty was associated with increased odds of mortality (AOR = 1.59, 95% CI: 1.30-1.80, P < 0.001), stroke (AOR = 1.66, 95% CI: 1.38-1.83 P < 0.001), MI (AOR = 1.51, 95% CI: 1.29-1.72, P < 0.001), and stroke/death (AOR = 1.62, 95% CI: 1.45-1.81, P < 0.001). Furthermore, frailty was associated with increased hospitalization costs (β = +$5,980, 95% CI: $5,490-$6,470, P < 0.001) and LOS (β = +2.6 days, 95% CI: 2.4-2.8, P < 0.001).
Conclusions:
Frailty is associated with adverse outcomes and greater resource use for those undergoing carotid revascularization. Risk models should include an assessment of frailty to guide management and improve outcomes for these high-risk patients.
More Related Videos
 05:53
Measuring Frailty in HIV-infected Individuals. Identification of Frail Patients is the First Step to Amelioration and Reversal of Frailty
Published on: July 24, 2013
 05:07
Author Spotlight: Improved Localization and Monitoring of Coronary Flow Reserve Using Modified PLAX View in Mice
Published on: August 25, 2023
Related Concept Videos
 01:26
Atherosclerosis III: Management
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:23
Atherosclerosis IV: Nursing Management
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations