

Latent class cluster analysis identified hidden headache phenotypes in COVID-19: impact of pulmonary infiltration and
Ömer Karadaş1,2, Bilgin Öztürk3, Ali Rıza Sonkaya3
1Neurology Department, Gülhane School of Medicine, University of Health Science, Ankara, Turkey. dromerkaradas@gmail.com.

Background And Objective:
Clinical studies on COVID-19 headache are limited. This prospective study aimed to define headache characteristics, associated clinical and laboratory factors, and treatment response in COVID-19.
Methods:
Cross-sectional study enrolled 287 patients diagnosed with COVID-19 and hospitalized on a regular ward during the pandemic. All patients were examined face to face and followed by a neurologist during their stay in the hospital. The characteristics, concomitant symptoms, treatment responses, and laboratory findings of COVID-19-associated headaches were recorded.
Results:
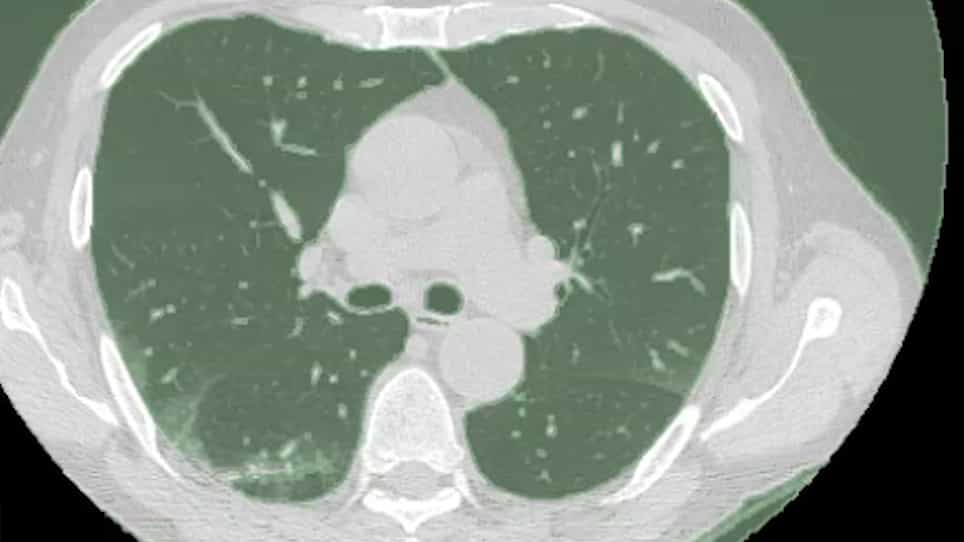
Eighty-three COVID-19 patients reported headache (28.9%), in which 85.5% had no prior headaches. Mean age was 48.40 ± 15.90 and 58% was men. Compared to COVID-19 patients without headache (n = 204), patients with headache showed significantly higher frequency of pulmonary involvement (76%) and increased D-dimer levels. Fifty-nine percent of headaches responded iv paracetamol 1000 mg, and 85% of the paracetamol unresponsive headaches were relieved by greater occipital nerve (GON) blocks. Latent class cluster analysis identified 2 distinct class of bilateral, frontal, throbbing headaches: severe (VAS > 84), longer (> 14 h), frequent (> 7 headache days), paracetamol unresponsive-GON responsive headaches (85%), with pulmonary involvement (100%), and higher IL-6 levels (> 90 pg/mL) were classified in cluster 1. Cluster 2 included moderately affected patients (VAS > 54, > 6 h, > 4 days, 60% pulmonary involvement, > 20 pg/mL IL-6) and paracetamol responsive headaches (96%). VAS scores showed positive linear correlation with IL-6 levels (p < 0.001; r = 0.567).
Conclusion:
The intensity, duration, frequency, bilateral frontal location, and treatment response of COVID-19 headache was related to pulmonary involvement and IL-6 levels, which indicated a role of inflammation in determining the headache manifestations in moderately affected hospitalized patients. ROC curve cutoff values pointed that VAS > 70 severity, > 9 h duration, > 5 headache days, and IL-6 > 43 pg/mL levels can be diagnostic for COVID-19 headache. GON blocks can effectively abort headache when patients are unresponsive to paracetamol, and other NSAIDs are avoided during the SARS-CoV-2 infection.
More Related Videos

Related Concept Videos
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:17
Classification of Illness
An illness is a response to a disease in which the person's level of functioning is changed compared with a previous level. The general classification of illness includes acute and chronic.
Acute illness is severe...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction