Related Experiment Video
Updated: Nov 16, 2025
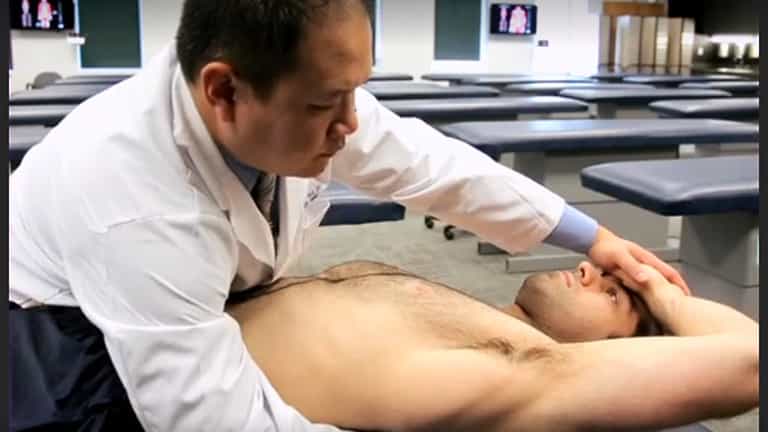

Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Antimicrobial Therapy for Pneumonia or Fluid Overload?
Uche J Mbadugha1, Salim Surani2,3, Nana Akuffo4
1Pharmacy, Corpus Christi Medical Center, Corpus Christi, USA.

Abstract:
Patients with evidence of fluid overload or heart failure (HF) without clinical symptoms of pneumonia are often treated with antimicrobial therapy for pneumonia. We conducted a retrospective study to evaluate the use of antimicrobial therapy in critically ill patients with fluid overload or heart failure diagnosed as pneumonia. A retrospective chart review of patients on antimicrobial therapy treated for pneumonia in the intensive care unit was conducted. The study's primary outcome was the number of cases with no evidence of pneumonia, including fluid overload or heart failure, managed with antimicrobial therapy for pneumonia. Patients on antimicrobial therapy for other infections were excluded. Appropriateness of antimicrobial therapy was based on radiographic evidence, clinical data, and presentation. Patient group categories were A (pneumonia) and B (no evidence of pneumonia, fluid overload, and heart failure). Based on the subdivision of patients in Group B, where there was no evidence of pneumonia, we further classified it into two subgroups: heart failure (HF)/fluid overload (Group B1) and no evidence of HF or fluid overload (Group B2). Patients with evidence of pneumonia (Group A) were compared to the group with fluid overload and heart failure (Group B1). A p-value of < 0.05% was considered significant for detecting statistical difference. Post-screening, data on 56 patients were collected for the study and analyzed. Mean body temperature and white blood cell count were 37.6 + 0.6 oC, and 17.4 + 6.88 x10³ µL, respectively. Based on radiographic evidence, clinical data, and presentation, 29 (52%) were classified under Group A, while 27 (48%) were classified under Group B. Median brain natriuretic peptide (BNP) for Group A vs. Group B was 514 (IQR: 1077) vs. 758 (2212) pg/mL p=0.14. The median duration of inpatient antimicrobial therapy was 7 (interquartile range [IQR]: 6) vs. 6 (IQR: 4) days, p=0.52, while the median duration of the total (inpatient and discharge prescription) antimicrobial therapy was 11 (IQR: 6) vs. 11 (IQR: 5), p=0.21. Patients with evidence of pneumonia (Group A) were compared to the group with fluid overload and heart failure (Group B1). The median BNP for the two groups was 514 (IQR: 1077) vs. 1040 (2094) pg/mL, p=0.04. Patients with documented echocardiographic evidence of ejection fraction < 55% were 4 vs. 14 for Groups A and B1, respectively. Additionally, the median BNP for Group A vs. Group B2 was 514 (IQR: 1077) vs. 189 (418) pg/mL, p=0.02. These findings demonstrate a 48% inappropriate use of antimicrobial therapy in patients with congestive heart failure (CHF), or fluid congestion misdiagnosed as pneumonia. There was a significant difference in the median BNP observed in patients with pneumonia compared to those with fluid overload and heart failure treated as pneumonia. More cases of patients with elevated BNP and reduced left ventricular ejection fraction (LVEF) were observed in patients with fluid overload or CHF treated as pneumonia than those diagnosed with pneumonia alone. Appropriate interpretation of radiographic evidence, laboratory data, and critical clinical assessment for the use of empiric antimicrobial therapy in this population is warranted.
More Related Videos
 09:17
A Robust Pneumonia Model in Immunocompetent Rodents to Evaluate Antibacterial Efficacy against S. pneumoniae, H. influenzae, K. pneumoniae, P. aeruginosa or A. baumannii
Published on: January 2, 2017
 11:17
Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Related Concept Videos
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:30
Pneumonia III: Complications and Assessment