Related Experiment Video
Updated: Nov 16, 2025
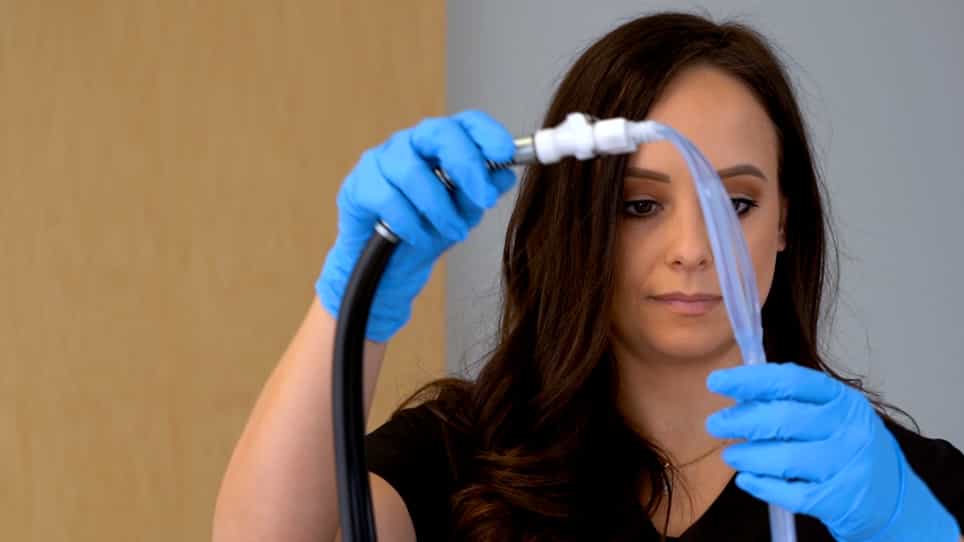
Cooling or Warming the Esophagus to Reduce Esophageal Injury During Left Atrial Ablation in the Treatment of Atrial Fibrillation
Published on: March 15, 2020
Active esophageal cooling for the prevention of thermal injury during atrial fibrillation ablation: a randomized
Cory M Tschabrunn1,2, Sara Attalla3, Jonathan Salas4
1Cardiac Electrophysiology Section, Division of Cardiovascular Medicine, Hospital of the University of Pennsylvania, 3400 Spruce Street, 9 Founders Pavilion, Philadelphia, PA, 19104, USA. coryt@pennmedicine.upenn.edu.

Background:
Severe endoscopically detected esophageal thermal lesions (EDELs) have been associated with higher risk of progression to atrio-esophageal fistula (AEF) following radiofrequency catheter ablation (RFCA) of atrial fibrillation (AF). We sought to evaluate safety and feasibility of active esophageal cooling using the Attune Medical Esophageal Heat Transfer Device (EnsoETM) to limit frequency or severity of EDELs.
Objective:
We sought To evaluate safety and feasibility of active esophageal cooling using the Attune Medical Esophageal Heat Transfer Device (EnsoETM) to limit frequency or severity of EDELs METHODS: Consecutive patients undergoing first-time RFCA were randomized in a 1:1 fashion to esophageal cooling (device group) or standard temperature monitoring (control group). Ablation on the posterior wall was performed with a maximum power of 30W for up to 20s. All patients underwent EGD within 48 h. Endoscopy findings were classified as 1, erythema-mild injury; 2, superficial ulceration-moderate injury; 3, deep ulceration-significant injury; and 4, fistula/perforation. Severe EDELs were defined as grade 3 or 4 lesions.
Results:
Forty-four patients completed the study (22 device group, 22 control group). Adjunctive posterior wall isolation was performed more frequently in the device group (11/22, 50% vs. 4/22, 18%). EDELs were detected in 5/22 (23%) control group patients, with mild or moderate injury in 2/5 patients (40%) and severe thermal injury in 3/5 patients (60%). In the device group, EDELs were detected in 8/22 (36%) patients, with mild or moderate injury in 7/8 (87%) patients and severe thermal injury in 1/8 (12%) patients. There was no acute perforation or AEF during follow-up.
Conclusions:
Active esophageal cooling may reduce the occurrence of severe EDELs. A larger randomized study is warranted to further evaluate the benefit of this strategy.
More Related Videos
 04:58
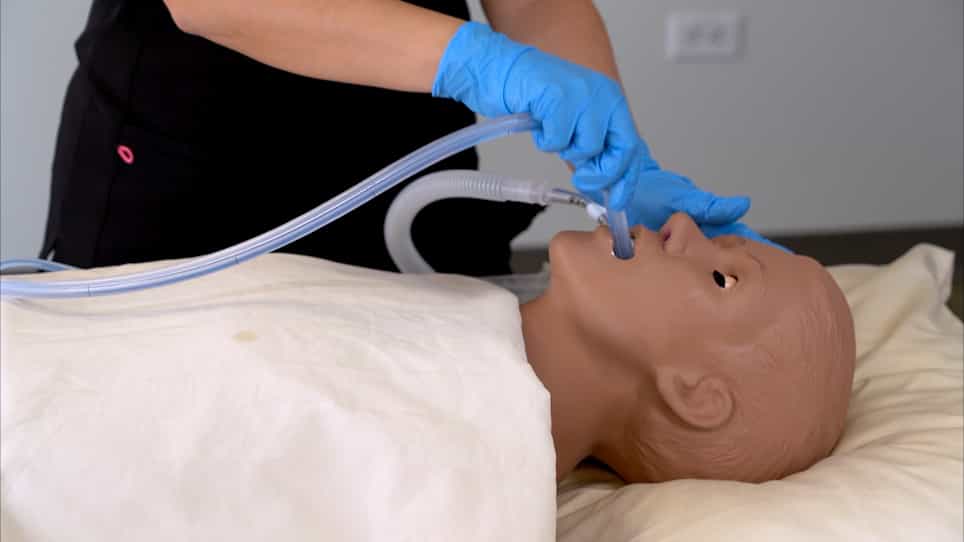
Reduced Procedure Time and Variability with Active Esophageal Cooling During Radiofrequency Ablation for Atrial Fibrillation
Published on: August 25, 2022
 05:43
Author Spotlight: Improving Lesion Contiguity in Pulmonary Vein Isolation via Proactive Esophageal Cooling
Published on: April 19, 2024
