Related Experiment Video
Updated: Nov 16, 2025
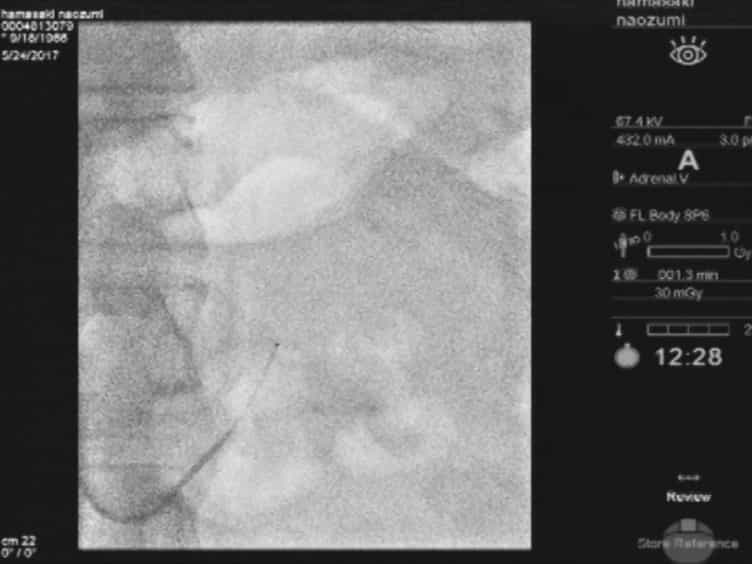
A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Primary aldosteronism due to bilateral micronodular hyperplasia and concomitant subclinical Cushing's syndrome: A
Hiroki Teragawa1, Chikage Oshita2, Yuichi Orita2
1Department of Cardiovascular Medicine, JR Hiroshima Hospital, Hiroshima 732-0057, Japan. hiroki-teragawa@jrhh.or.jp.

Background:
Adrenal incidentaloma (AI) has been frequently encountered in the clinical setting. It has been shown that primary aldosteronism (PA) or subclinical Cushing's syndrome (SCS) are the representative causative diseases of AI. However, the coexistence of PA and SCS has been reportedly observed. Recently, we encountered a case of AI, in which PA and SCS coexisted, confirmed by histopathological examinations after a laparoscopic adrenalectomy. We believe that there were some clinical implications in the diagnosis of the present case.
Case Summary:
A 58-year-old man presented with lower right abdominal pain with a blood pressure of 170/100 mmHg. A subsequent computed tomography scan revealed right ureterolithiasis, which was the cause of right abdominal pain, and right AI measuring 22 mm × 25 mm. After the disappearance of right abdominal pain, subsequent endocrinological examinations were performed. Aldosterone-related evaluations, including adrenal venous sampling, revealed the presence of bilateral PA. In addition, several cortisol-related evaluations showed the presence of SCS on the right adrenal adenoma. A laparoscopic right adrenalectomy was then performed. The histopathological examination of the resected right adrenal revealed the presence of a cortisol-producing adenoma, while CYP11B2 immunoreactivity was absent in this adenoma. However, in the adjacent non-neoplastic adrenal, multiple CYP11B2-positive adrenocortical micronodules were detected, showing the presence of aldosterone-producing adrenocortical micronodules.
Conclusion:
Careful clinical and pathological examination should be performed when a patient harboring AI presents with concomitant SCS and PA.
More Related Videos
 07:43
Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
 07:36
Induction of Atherosclerotic Plaques Through Activation of Mineralocorticoid Receptors in Apolipoprotein E-deficient Mice
Published on: September 26, 2018
Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:31
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and...
 01:24
Nephrotic Syndrome I : Introduction
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:17
Anatomy of the Adrenal Glands
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct...