Related Experiment Video
Updated: Nov 15, 2025


Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Proposal of initial and maintenance dosing regimens with linezolid for renal impairment patients
Hitoshi Kawasuji1, Yasuhiro Tsuji2, Chika Ogami3
1Department of Clinical Infectious Diseases, Toyama University Graduate School of Medicine and Pharmaceutical Sciences, 2630 Sugitani, Toyama, 930-0194, Japan.

Background:
Linezolid is administered as a fixed dose to all patients despite evidence of overexposure and thrombocytopenia in renal impairment. The aims of this study were to evaluate the risk of thrombocytopenia and the utility of therapeutic drug monitoring (TDM), and to propose alternate dosing regimens in patients with renal impairment.
Methods:
We retrospectively reviewed patients ≥13 years old for whom serum linezolid trough concentration (Cmin) was measured during linezolid treatment. Patients with episodes of infection were divided into groups by presence of renal impairment (RI group) or absence of renal impairment (non-RI group), and by use of Cmin-based TDM (TDM group) or not (non-TDM group) during linezolid treatment.
Results:
In the 108 patients examined by multivariable analyses, renal impairment was independently associated with increased risk of thrombocytopenia (OR 3.17, 95%CI 1.10-9.12) and higher Cmin. Analysis of the utility of TDM in the RI group showed that clinical failure rate was significantly lower in the TDM subgroup than in the non-TDM subgroup. Furthermore, in the RI group, dosage adjustments were needed in 90.5% of the TDM subgroup. All episodes administered a reduced dose of 300 mg every 12 h in the RI group showed Cmin ≥ 2.0 mg/L. Additional analysis of 53 episodes in which Cmin was measured within 48 h after starting administration showed that the initial standard dose for 2 days was sufficient to rapidly reach an effective therapeutic concentration in the RI group.
Conclusions:
Empirical dose reduction to 300 mg every 12 h after administration of the initial fixed dose for 2 days and Cmin-based TDM may improve safety outcomes while maintaining appropriate efficacy among patients with renal impairment.


Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady...
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:28
Dosage Regimens: Designs and Approaches
 01:24
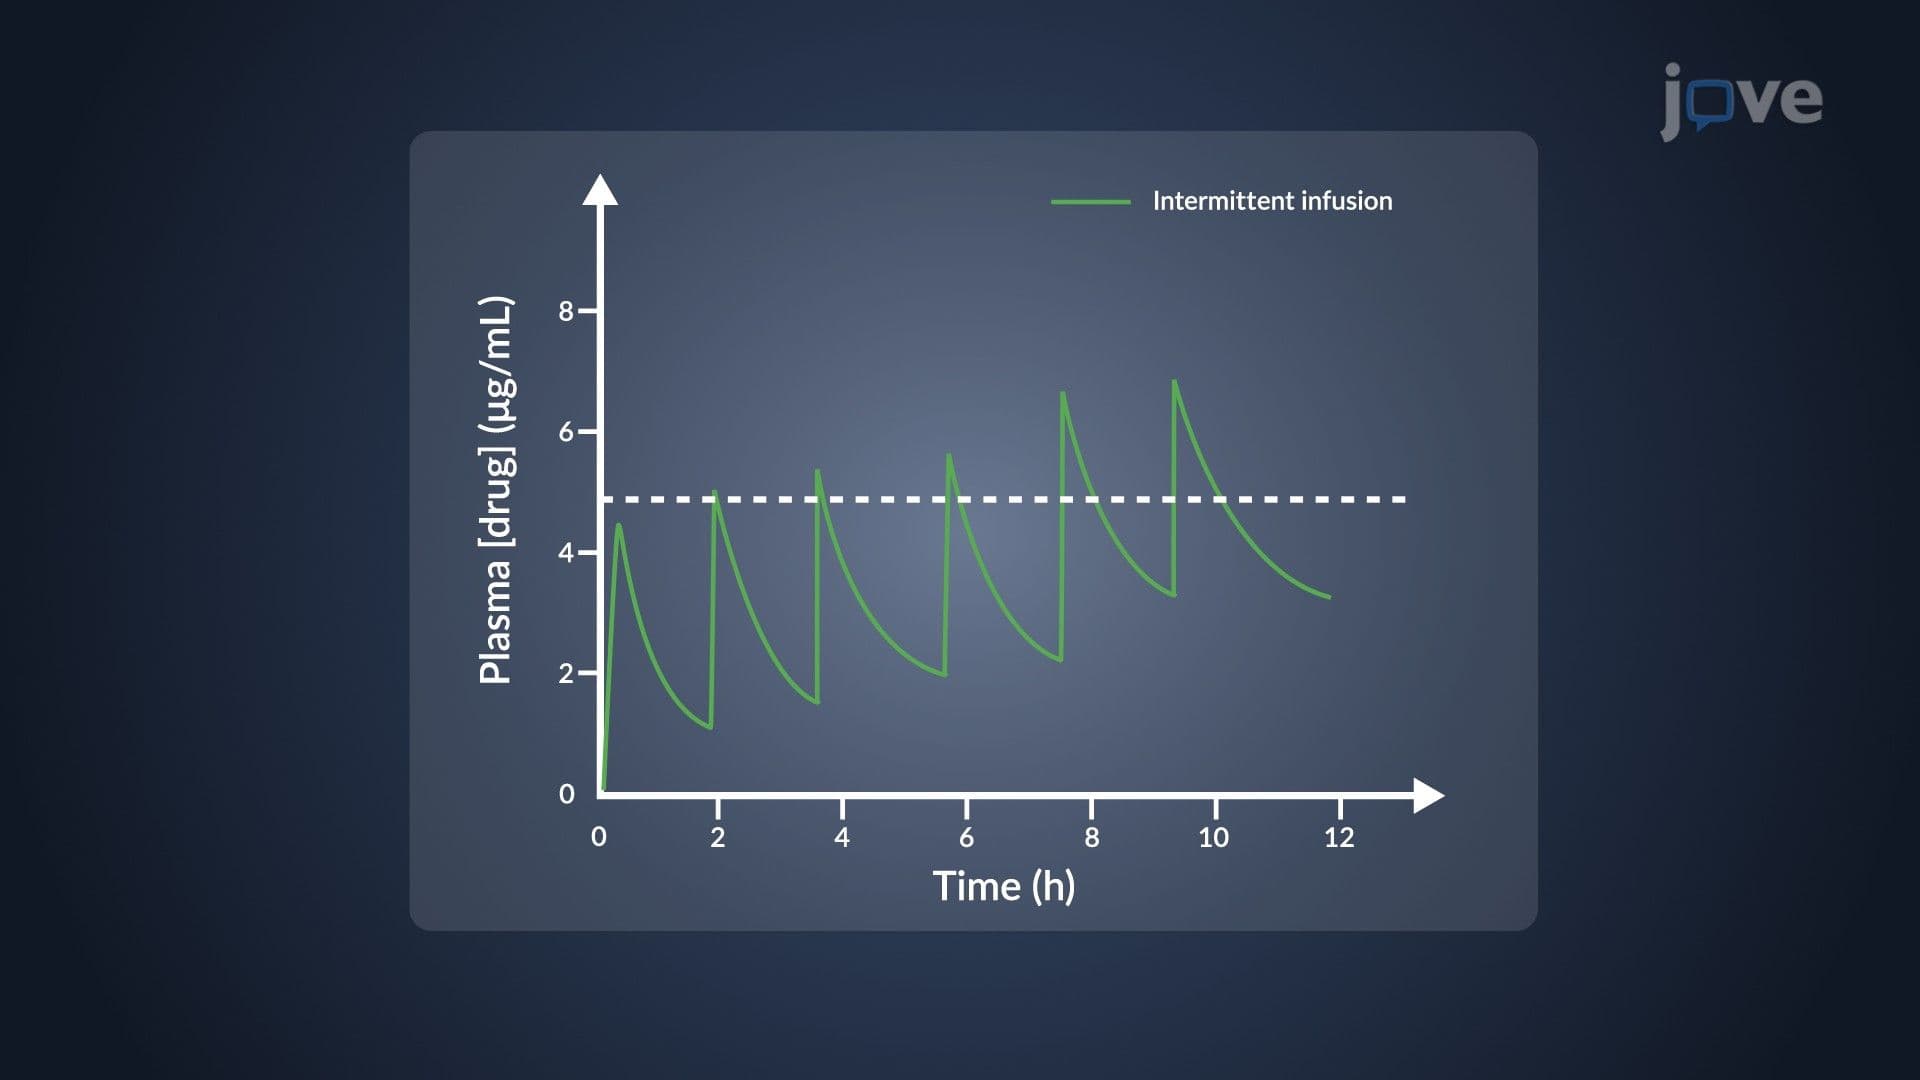
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions