Related Experiment Video
Updated: Nov 15, 2025

Anterior Capsular Reconstruction with Human Dermal Allograft for Irreparable Subscapularis Tears
Published on: May 9, 2025
Quantitative and Qualitative Surgical Anatomy of the Acromioclavicular Joint Capsule and Ligament: A Cadaveric Study
Philip-C Nolte1,2, Joe J Ruzbarsky1,3, Kaare S Midtgaard1,4,5
1Steadman Philippon Research Institute, Vail, Colorado, USA.

Background:
The acromioclavicular (AC) capsule and ligament have been found to play a major role in maintaining horizontal stability. To reconstruct the AC capsule and ligament, precise knowledge of their anatomy is essential.
Purpose/Hypothesis:
The purposes of this study were (1) to determine the angle of the posterosuperior ligament in regard to the axis of the clavicle, (2) to determine the width of the attachment (footprint) of the AC capsule and ligament on the acromion and clavicle, (3) to determine the distance to the AC capsule from the cartilage border of the acromion and clavicle, and (4) to develop a clockface model of the insertion of the posterosuperior ligament on the acromion and clavicle. It was hypothesized that consistent angles, attachment areas, distances, and insertion sites would be identified.
Study Design:
Descriptive laboratory study.
Methods:
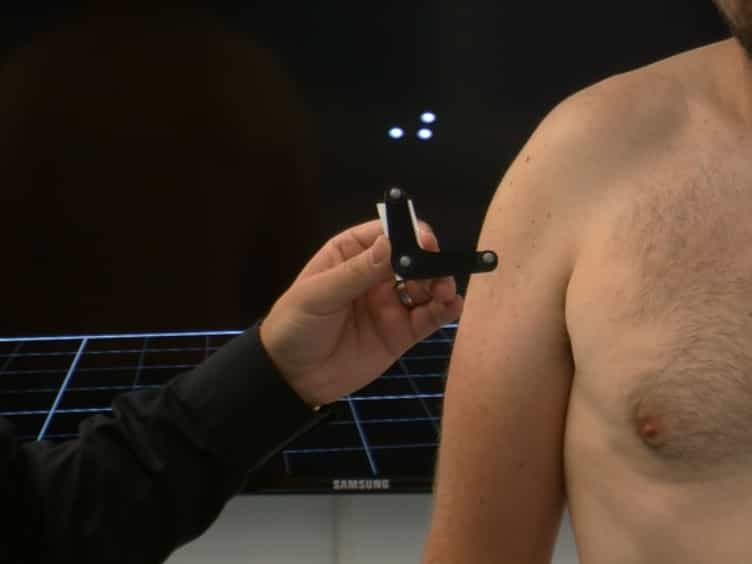
A total of 12 fresh-frozen shoulders were used (mean age, 55 years [range, 41-64 years]). All soft tissue was removed, leaving only the AC capsule and ligament intact. After a qualitative inspection, a quantitative assessment was performed. The AC joint was fixed in an anatomic position, and the attachment angle of the posterosuperior ligament was measured using a digital protractor. The capsule and ligament were removed, and a coordinate measuring device was utilized to assess the width of the AC capsule footprint and the distance from the footprint to the cartilage border of the acromion and clavicle. The AC joint was then disarticulated, and the previously marked posterosuperior ligament insertion was transferred into a clockface model. The mean values across the 12 specimens were demonstrated with 95% CIs.
Results:
The mean attachment angle of the posterosuperior ligament was 51.4° (95% CI, 45.2°-57.6°) in relation to the long axis of the entire clavicle and 41.5° (95% CI, 33.8°-49.1°) in relation to the long axis of the distal third of the clavicle. The mean clavicular footprint width of the AC capsule was 6.4 mm (95% CI, 5.8-6.9 mm) at the superior clavicle and 4.4 mm (95% CI, 3.9-4.8 mm) at the inferior clavicle. The mean acromial footprint width of the AC capsule was 4.6 mm (95% CI, 4.2-4.9 mm) at the superior side and 4.0 mm (95% CI, 3.6-4.4 mm) at the inferior side. The mean distance from the lateral clavicular attachment of the AC capsule to the clavicular cartilage border was 4.3 mm (95% CI, 4.0-4.6 mm), and the mean distance from the medial acromial attachment of the AC capsule to the acromial cartilage border was 3.1 mm (95% CI, 2.9-3.4 mm). On the clockface model of the right shoulder, the clavicular attachment of the posterosuperior ligament ranged from the 9:05 (range, 8:00-9:30) to 11:20 (range, 10:00-12:30) position, and the acromial attachment ranged from the 12:20 (range, 11:00-1:30) to 2:10 (range, 13:30-14:40) position.
Conclusion:
The finding that the posterosuperior ligament did not course perpendicular to the AC joint but rather was oriented obliquely to the long axis of the clavicle, in combination with the newly developed clockface model, may help surgeons to optimally reconstruct this ligament.
Clinical Relevance:
Our results of a narrow inferior footprint and a short distance from the inferior AC capsule to cartilage suggest that proposed reconstruction of the AC joint capsule should focus primarily on its superior portion.
Related Concept Videos
 01:09
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:17
Structural Joints: Cartilaginous Joints
There are two types of cartilaginous joints:
Synchondrosis
A synchondrosis ("joined by cartilage") is a cartilaginous joint where bones are connected by hyaline cartilage. Synchondrosis may be temporary...
 01:19
Bones of the Upper Limb: Humerus
 01:17
Gross Anatomy of Bone
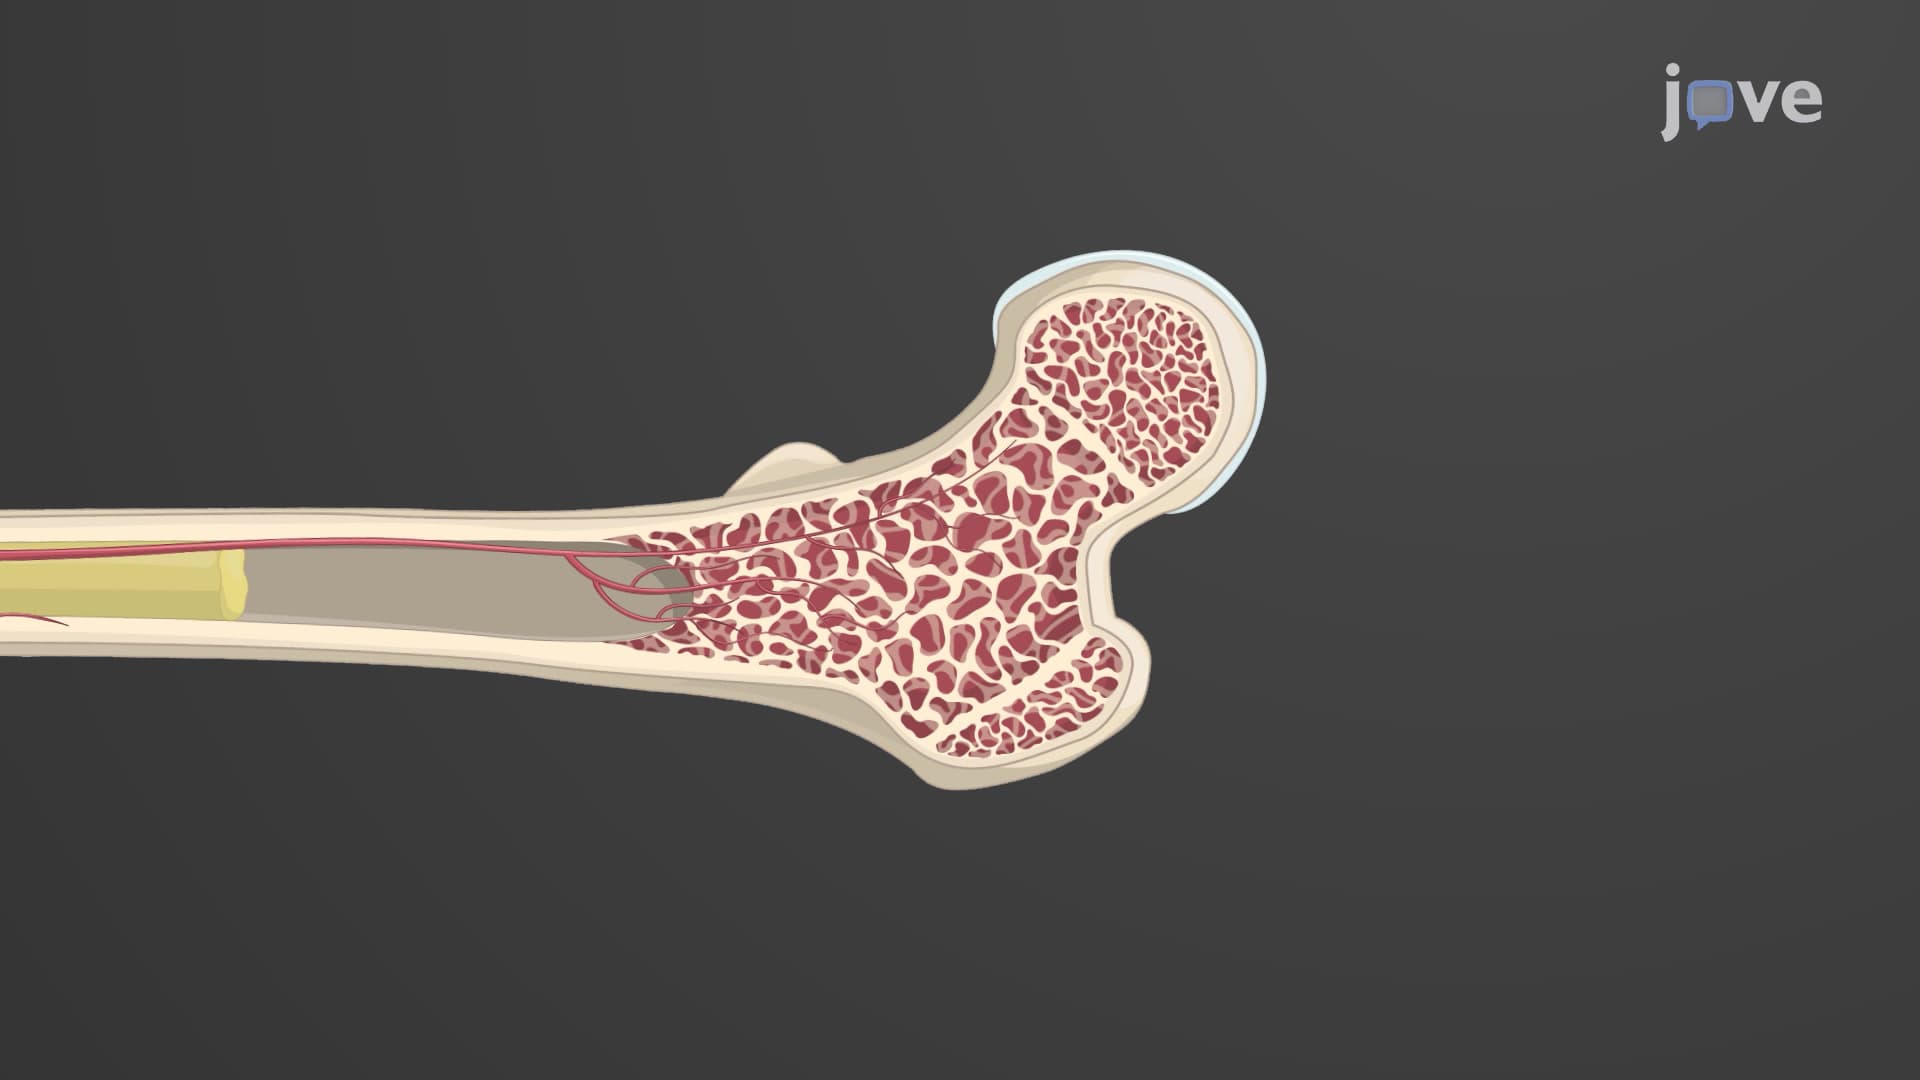
The diaphysis is the tubular shaft that runs between the proximal and distal ends of the bone. The walls of the diaphysis are composed of dense and hard compact bone made of numerous osteons — the functional unit of the compact bone. The hollow region in the diaphysis is called the medullary cavity, which harbors the bone marrow. In infants and children, this marrow cavity is filled with red marrow, whereas in...
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...