Related Experiment Video
Updated: Nov 15, 2025
Transcutaneous Microcirculatory Imaging in Preterm Neonates
Published on: December 31, 2015
The indirect calorimetry in very low birth weight preterm infants: An easier and reliable procedure
Michela Perrone1, Domenica Mallardi1, Chiara Tabasso1
1Neonatal Intensive Care Unit, Fondazione IRCCS Ca' Granda Ospedale Maggiore Policlinico, Milan, Italy.

Insights
Determining resting energy expenditure (REE) in preterm infants requires shorter calorimetry durations. Twenty minutes of steady-state measurement is sufficient for reliable REE data in stable, very low birth weight infants.
Area of Science:
- Neonatal nutrition and metabolism
- Pediatric critical care
Background:
- Preterm infants face risks of extrauterine growth restriction and associated adverse health outcomes.
- Accurate measurement of resting energy expenditure (REE) is crucial for nutritional management but challenging in infants due to motion artifacts during indirect calorimetry.
- Existing methods for REE assessment in neonates are hampered by the prolonged measurement times needed to achieve reliable data.
Purpose of the Study:
- To determine the minimum duration of indirect calorimetry required to obtain reliable resting energy expenditure (REE) measurements in preterm infants.
- To address the practical limitations of prolonged calorimetry in a neonatal intensive care unit setting.
Main Methods:
- Indirect calorimetry was performed on 26 very low birth weight preterm infants for a mean duration of 90 minutes.
- Oxygen consumption (VO2) and carbon dioxide production (VCO2) were recorded, and REE was calculated.
- Data from 10, 20, 30, 40, and 50-minute steady-state intervals (T1-T5) were compared to the entire steady-state period.
Main Results:
- No significant differences were observed in mean VO2 and REE values between the 10, 20, 30, 40, and 50-minute intervals compared to the full steady-state period.
- Median VCO2 values showed significant differences only when the 10-minute interval (T1) was compared to other time points.
- These findings suggest that shorter measurement durations can yield comparable results for REE.
Conclusions:
- Twenty minutes of steady-state measurement during indirect calorimetry is sufficient to obtain reliable REE data in stable, very low birth weight preterm infants.
- This finding can help optimize indirect calorimetry protocols, reducing examination time and improving feasibility in neonatal care.
- Shorter, reliable REE measurements can aid in precise nutritional support for preterm infants, potentially mitigating extrauterine growth restriction.
Objectives:
Preterm infants are at increased risk of developing extrauterine growth restriction, which is associated with worse health outcomes. The energy needs are not well known, as the measurement of resting energy expenditure (REE) using indirect calorimetry has critical issues when applied to infants. One of the main issues is the time required to obtain reliable data owing to the difficulty in keeping infants quiet during the entire examination. Thus, the aim of this study was to define the minimum duration of calorimetry to obtain reliable data.
Methods:
The volume of oxygen consumption (VO2) and the volume of carbon dioxide production (VCO2) were recorded for a mean duration of 90 consecutive minutes. REE was calculated using a neonatal prototype calculator. We extracted data regarding VO2, VCO2, and REE at 10(T1), 20(T2), 30(T3), 40(T4), and 50(T5) minutes of steady state and compared these data to those of entire steady state period.
Results:
Twenty-six very low birth weight preterm infants were evaluated at 36.58 ± 0.99 wk corrected age. Infants were appropriate for gestational age and clinically stable without comorbidities. There were no significant differences between mean VO2 and REE at T1 (8.26 ± 1.45 mL/kg to 57.80 ± 10.51 kcal/kg), T2 (8.15 ± 1.41 mL/kg to 56.87 ± 10.05 kcal/kg), T3 (8.04 ± 1.41 mL/kg to 56.32 ± 9.73 kcal/kg), T4 (8.05 ± 1.41 mL/kg to 56.07 ± 10.28 kcal/kg), and T5 (8.06 ± 1.55 mL/kg to 57.17 ± 11.62 kcal/kg), respectively, compared to steady state (8.13 ± 1.33 mL/kg to 56.77 ± 9.34 kcal/kg). The median values of VCO2 were significantly different only when T1 data were compared with other time slots (7.02 ± 1.02 mL/kg at steady state; 7.26 ± 1.23 mL/kg at T1; 7.13 ± 1.20 mL/kg at T2; 7.02 ± 1.19 mL/kg at T3; 6.85 ± 1.16 mL/kg at T4; 6.91 ± 1.24 mL/kg at T5).
Conclusion:
Twenty consecutive minutes in steady state condition are sufficient to obtain reliable data on REE in stable, very low birth weight infants.
More Related Videos
 04:54
Using a Combination of Indirect Calorimetry, Infrared Thermography, and Blood Glucose Levels to Measure Brown Adipose Tissue Thermogenesis in Humans
Published on: June 2, 2023
 11:39
Non-invasive Optical Measurement of Cerebral Metabolism and Hemodynamics in Infants
Published on: March 14, 2013
Related Concept Videos
 01:14
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...
 02:41
Constant Volume Calorimetry
 03:02
Constant Pressure Calorimetry
 01:27
Assessing Body Temperature - Rectal
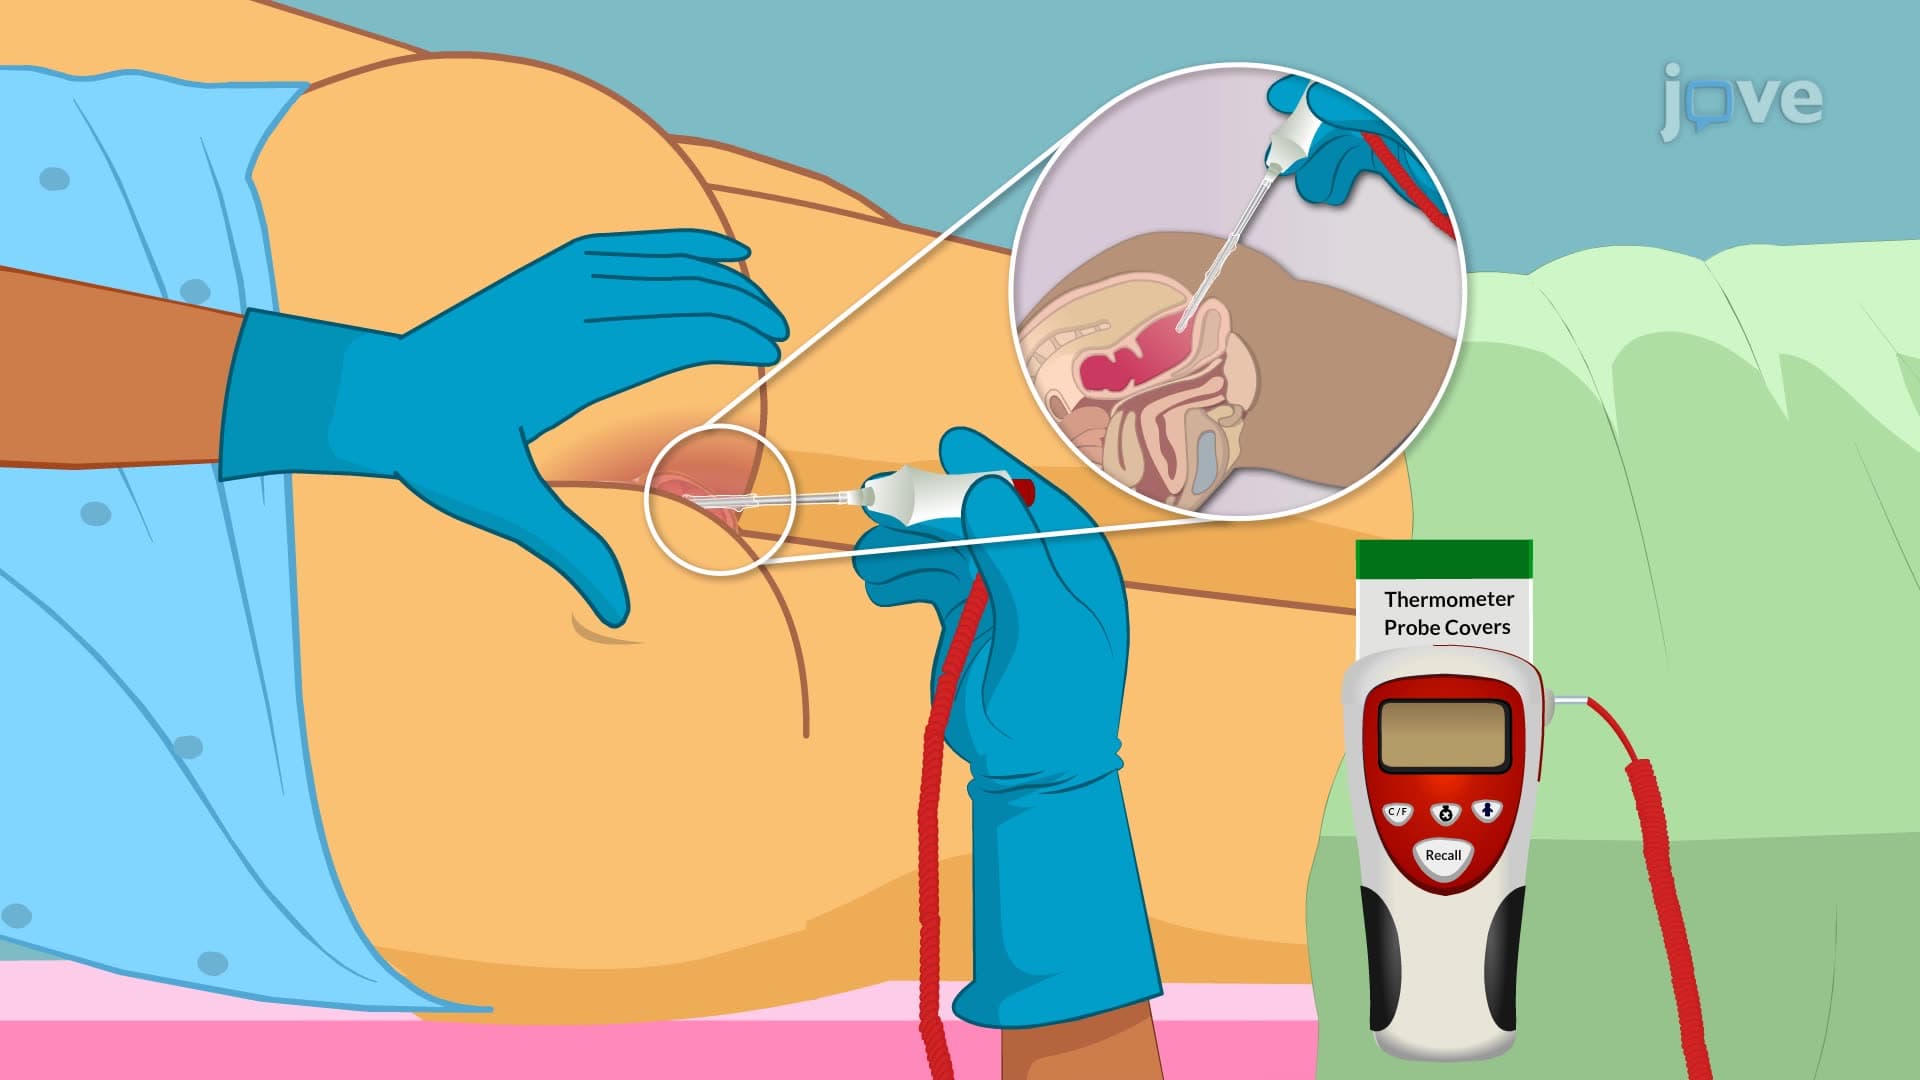
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:29
Decreased Body Temperature