Pulmonary interstitial emphysema--a radiological and pathological correlation

A E Boothroyd1, A J Barson

  • 1Department of Radiology, St. Mary's Hospital, Manchester, UK.

Pediatric Radiology
|January 1, 1988
PubMed

Related Concept Videos

Pulmonary Embolism I: Introduction01:29

Pulmonary Embolism I: Introduction

Pulmonary embolism (PE) occurs when a thrombus, fat or air embolus, amniotic fluid, or tumor tissue blocks one or more pulmonary arteries. These blockages originate in the venous system or the right side of the heart.EtiologyPE primarily arises from deep vein thrombosis (DVT) and other hypercoagulable states, such as inherited thrombophilias. Additional etiological factors include venous stasis, commonly seen in obesity, and endothelial injury from surgery and trauma. Less common causes include...
Atelectasis II: Pathophysiology01:10

Atelectasis II: Pathophysiology

Atelectasis develops when alveoli lose their air and collapse inward. Because lung tissue is naturally elastic, these air sacs shrink rather than remaining open. Collapsed alveoli are no longer ventilated, reducing their role in gas exchange. Blood flow may continue in these regions, creating a ventilation–perfusion mismatch. Clinical findings include decreased breath sounds, dullness to percussion, reduced chest expansion, and decreased tactile fremitus as sound transmission through collapsed...
Chronic Obstructive Pulmonary Disease II: Emphysema01:23

Chronic Obstructive Pulmonary Disease II: Emphysema

Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features01:24

Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
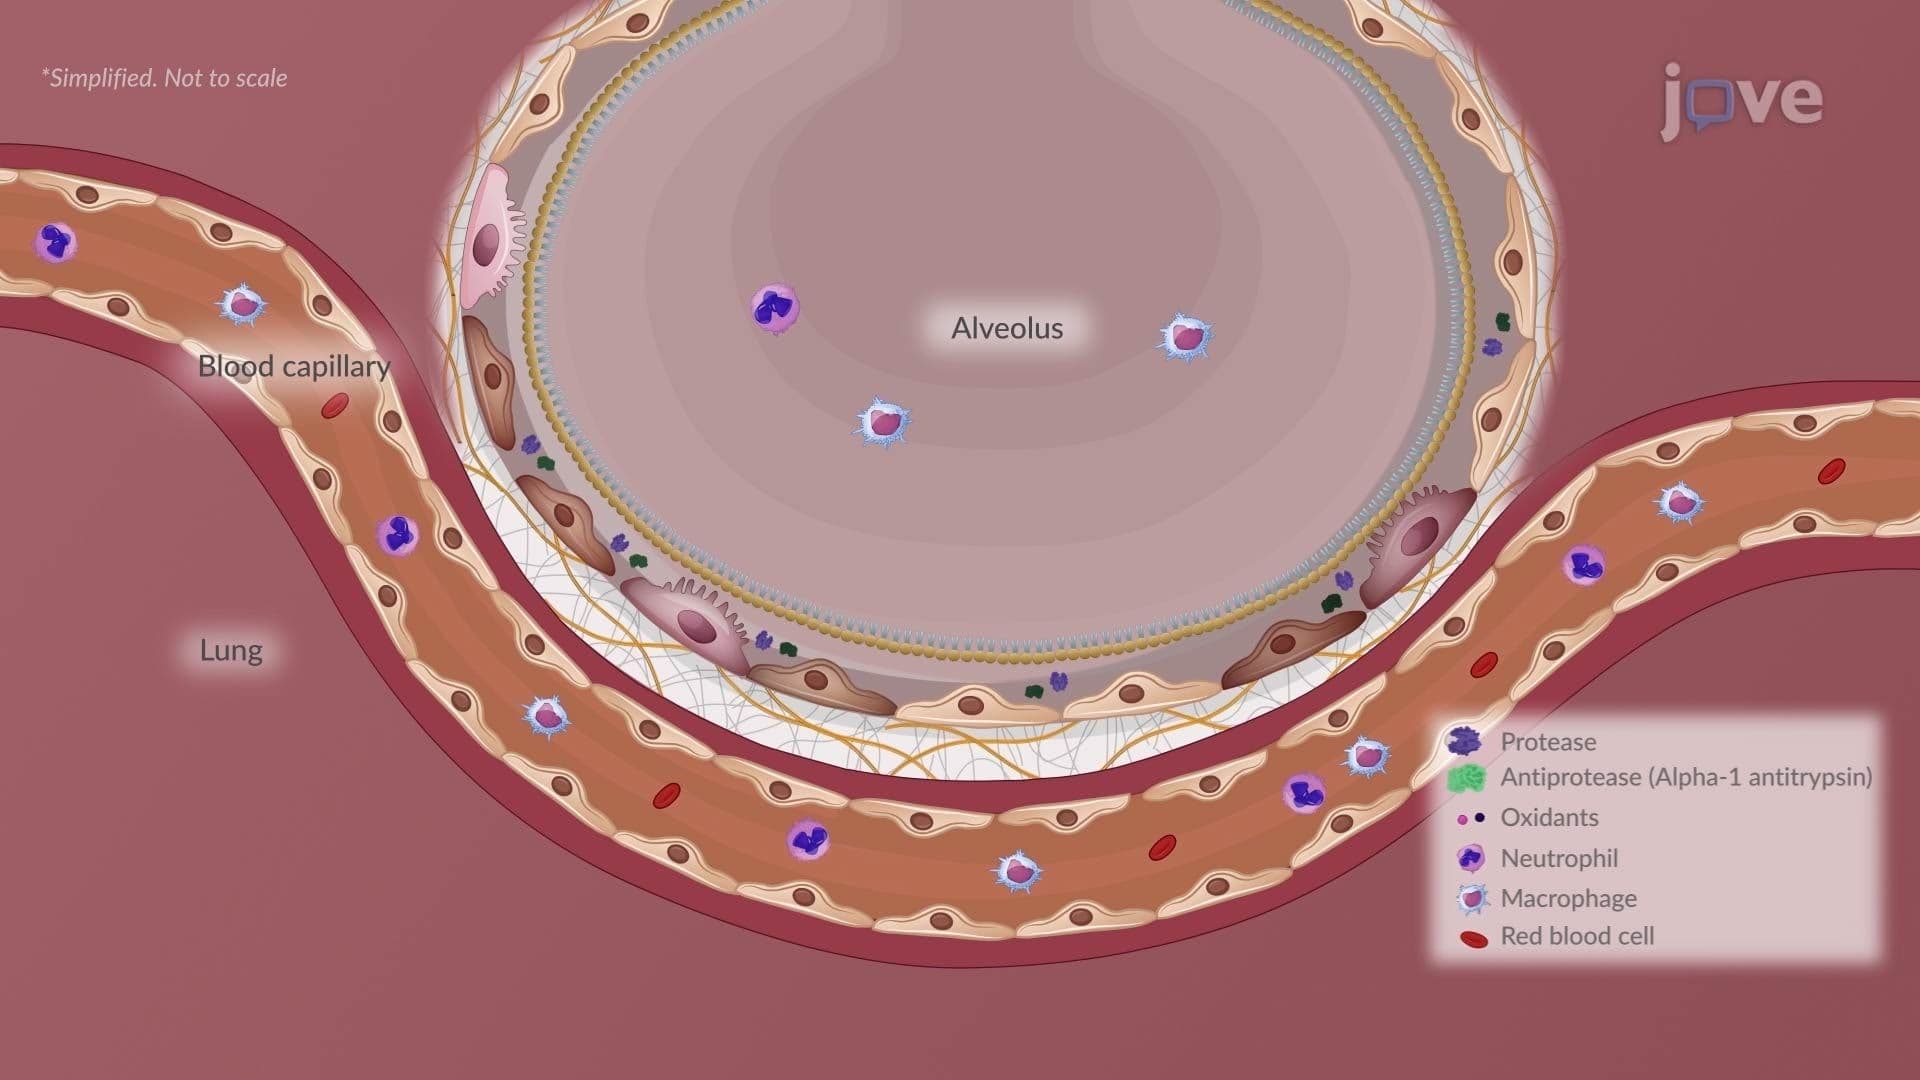
Chronic bronchitis is a key phenotype of chronic obstructive pulmonary disease (COPD), characterized by airway-centered inflammation and mucus overproduction. It develops from long-term exposure to harmful particles or gases, most commonly cigarette smoke, which triggers a persistent inflammatory response.Cellular and Structural ChangesInflammation initially affects the large bronchi and later the smaller airways, with infiltration by immune cells, including neutrophils, macrophages, and...
Pulmonary Edema II: Pathophysiology01:18

Pulmonary Edema II: Pathophysiology
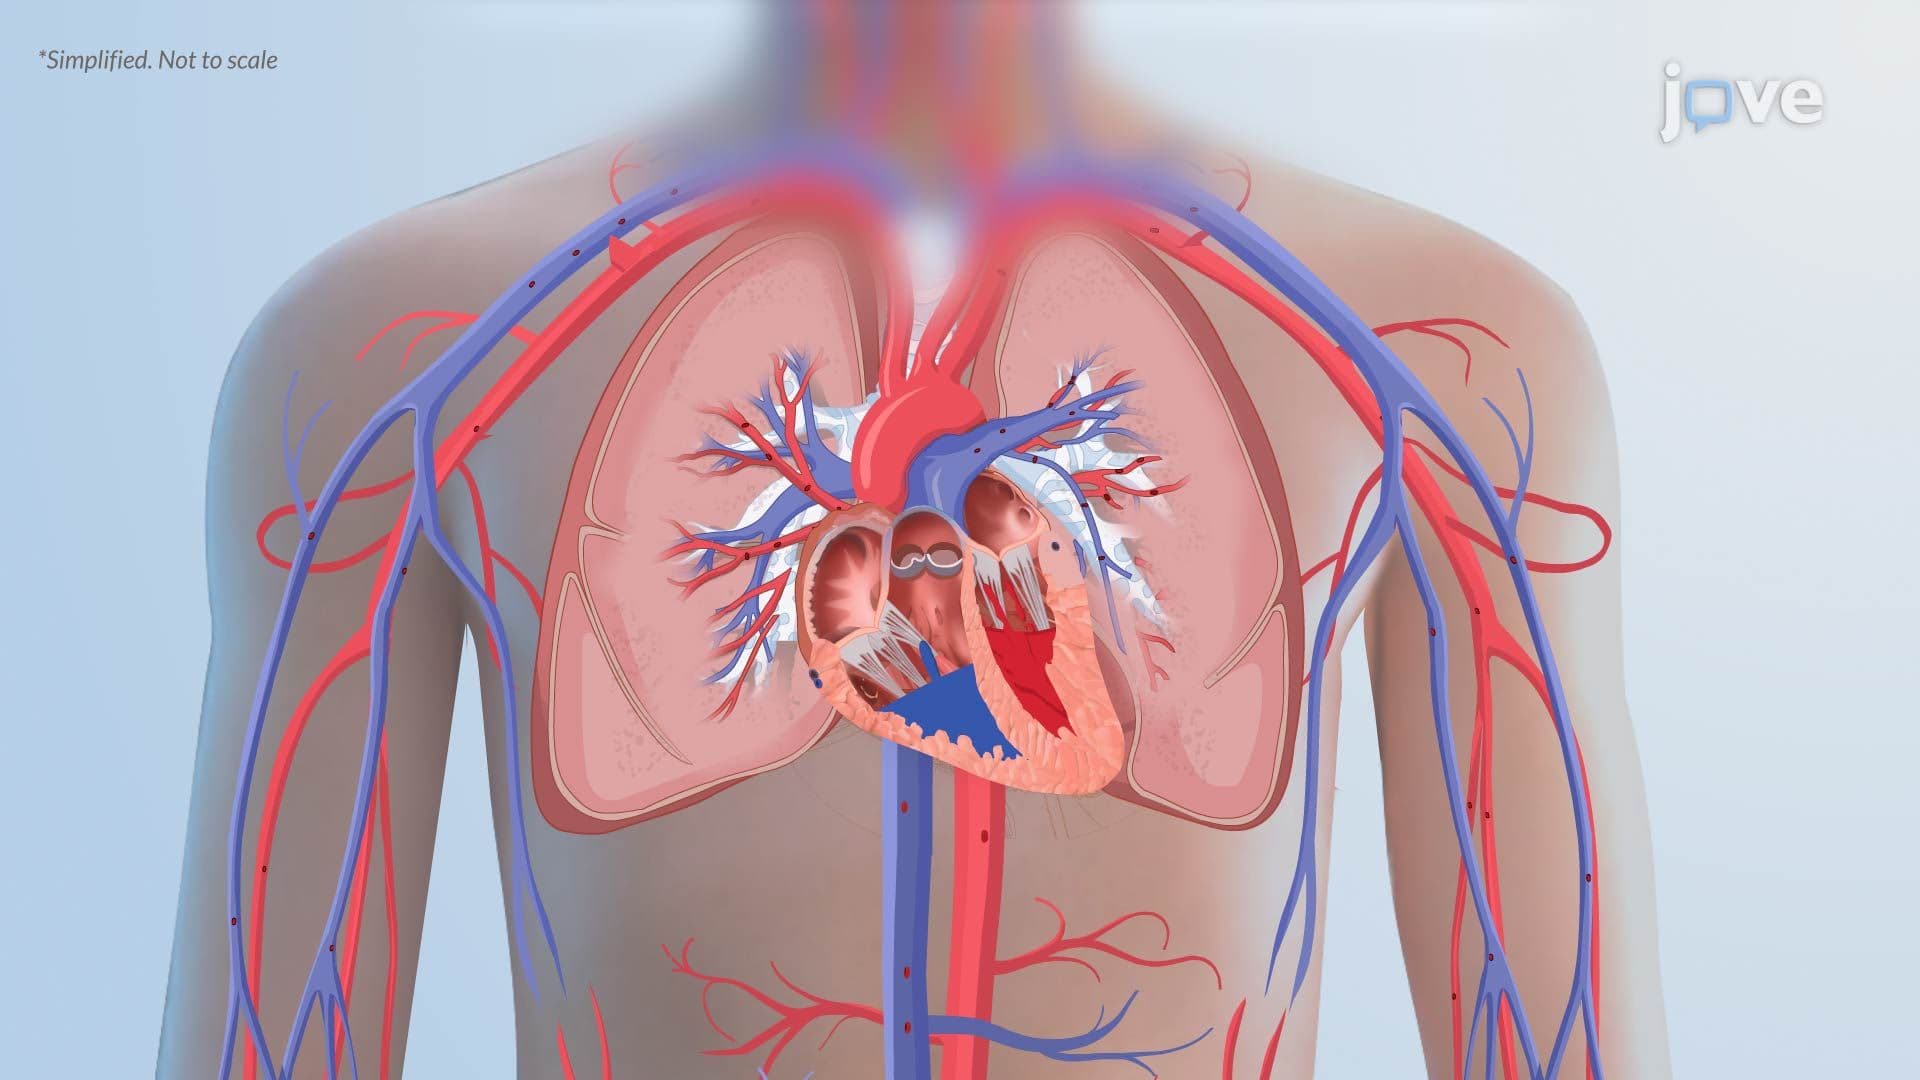
Pulmonary edema is the accumulation of fluid in the interstitial and alveolar spaces of the lungs, impairing gas exchange and oxygen delivery. It may be cardiogenic or noncardiogenic, but both reduce oxygenation and lung compliance.Cardiogenic Pulmonary EdemaCardiogenic edema results from increased hydrostatic pressure in pulmonary capillaries, usually due to left ventricular dysfunction from myocardial infarction, heart failure, or valvular disease. Ineffective cardiac pumping causes blood to...
Pulmonary Embolism I: Introduction01:19

Pulmonary Embolism I: Introduction

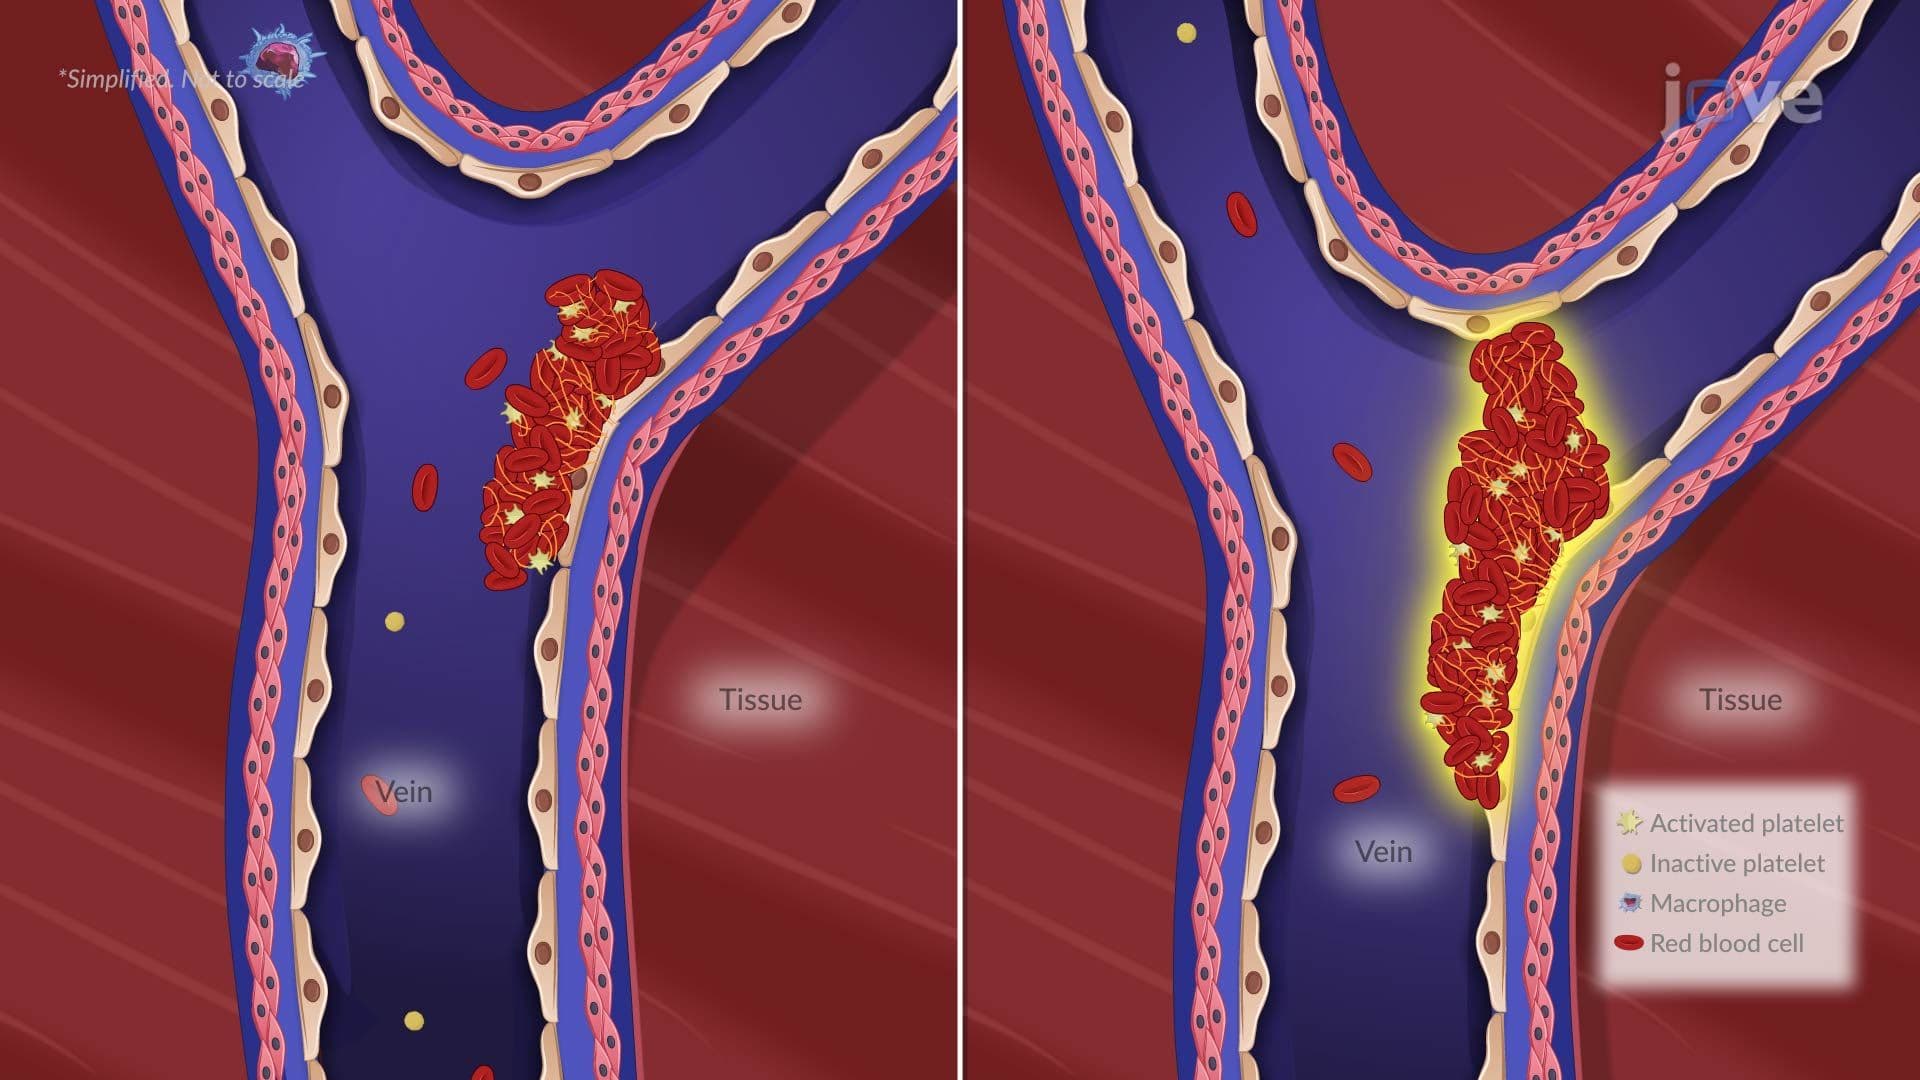
A blood clot, or thrombus, is a semi-solid mass composed of fibrin, platelets, and red blood cells. When it forms within a vessel, it can obstruct blood flow, known as thrombosis. If part of the clot detaches, it becomes an embolus that can travel and block distant vessels. When this occurs in the pulmonary arteries, it causes a condition known as pulmonary embolism (PE).Origin and ImpactMost often, the embolus originates from a thrombus in the deep veins of the lower limbs, a condition called...