Related Experiment Video
Updated: Nov 14, 2025
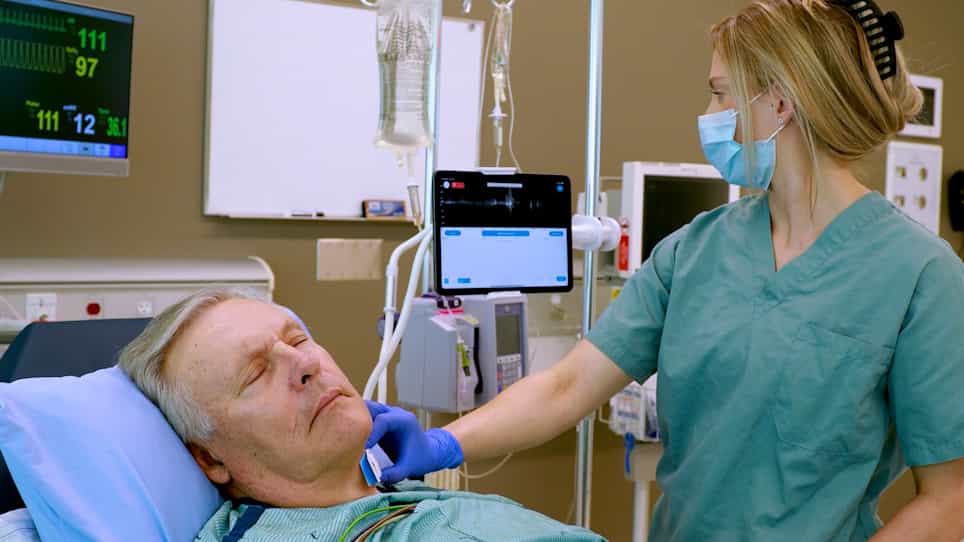

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Estimation of cardiac output variations induced by hemodynamic interventions using multi-beat analysis of arterial
Arthur Le Gall1,2,3,4, Fabrice Vallée5,6,7,8, Jona Joachim5,6,7,8
1Inria Paris-Saclay, 01, avenue Honoré d'Estienne d'Orves, 91120, Palaiseau, France. arthur.le-gall@aphp.fr.

Abstract:
Multi-beat analysis (MBA) of the radial arterial pressure (AP) waveform is a new method that may improve cardiac output (CO) estimation via modelling of the confounding arterial wave reflection. We evaluated the precision and accuracy using the trending ability of the MBA method to estimate absolute CO and variations (ΔCO) during hemodynamic challenges. We reviewed the hemodynamic challenges (fluid challenge or vasopressors) performed when intra-operative hypotension occurred during non-cardiac surgery. The CO was calculated offline using transesophageal Doppler (TED) waveform (COTED) or via application of the MBA algorithm onto the AP waveform (COMBA) before and after hemodynamic challenges. We evaluated the precision and the accuracy according to the Bland & Altman method. We also assessed the trending ability of the MBA by evaluating the percentage of concordance with 15% exclusion zone between ΔCOMBA and ΔCOTED. A non-inferiority margin was set at 87.5%. Among the 58 patients included, 23 (40%) received at least 1 fluid challenge, and 46 (81%) received at least 1 bolus of vasopressors. Before treatment, the COTED was 5.3 (IQR [4.1-8.1]) l min-1, and the COMBA was 4.1 (IQR [3-5.4]) l min-1. The agreement between COTED and COMBA was poor with a 70% percentage error. The bias and lower and upper limits of agreement between COTED and COMBA were 0.9 (CI95 = 0.82 to 1.07) l min-1, -2.8 (CI95 = -2.71 to-2.96) l min-1 and 4.7 (CI95 = 4.61 to 4.86) l min-1, respectively. After hemodynamic challenge, the percentage of concordance (PC) with 15% exclusion zone for ΔCO was 93 (CI97.5 = 90 to 97)%. In this retrospective offline analysis, the accuracy, limits of agreements and percentage error between TED and MBA for the absolute estimation of CO were poor, but the MBA could adequately track induced CO variations measured by TED. The MBA needs further evaluation in prospective studies to confirm those results in clinical practice conditions.
More Related Videos
 04:48
Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
 11:50
High-frequency High-resolution Echocardiography: First Evidence on Non-invasive Repeated Measure of Myocardial Strain, Contractility, and Mitral Regurgitation in the Ischemia-reperfused Murine Heart
Published on: July 9, 2010
Related Concept Videos
 01:19
Assessing Blood pressure using a doppler ultrasound
Pre-Procedural Guidelines for Doppler Ultrasound Blood Pressure Assessment:
Preparation of Equipment:
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
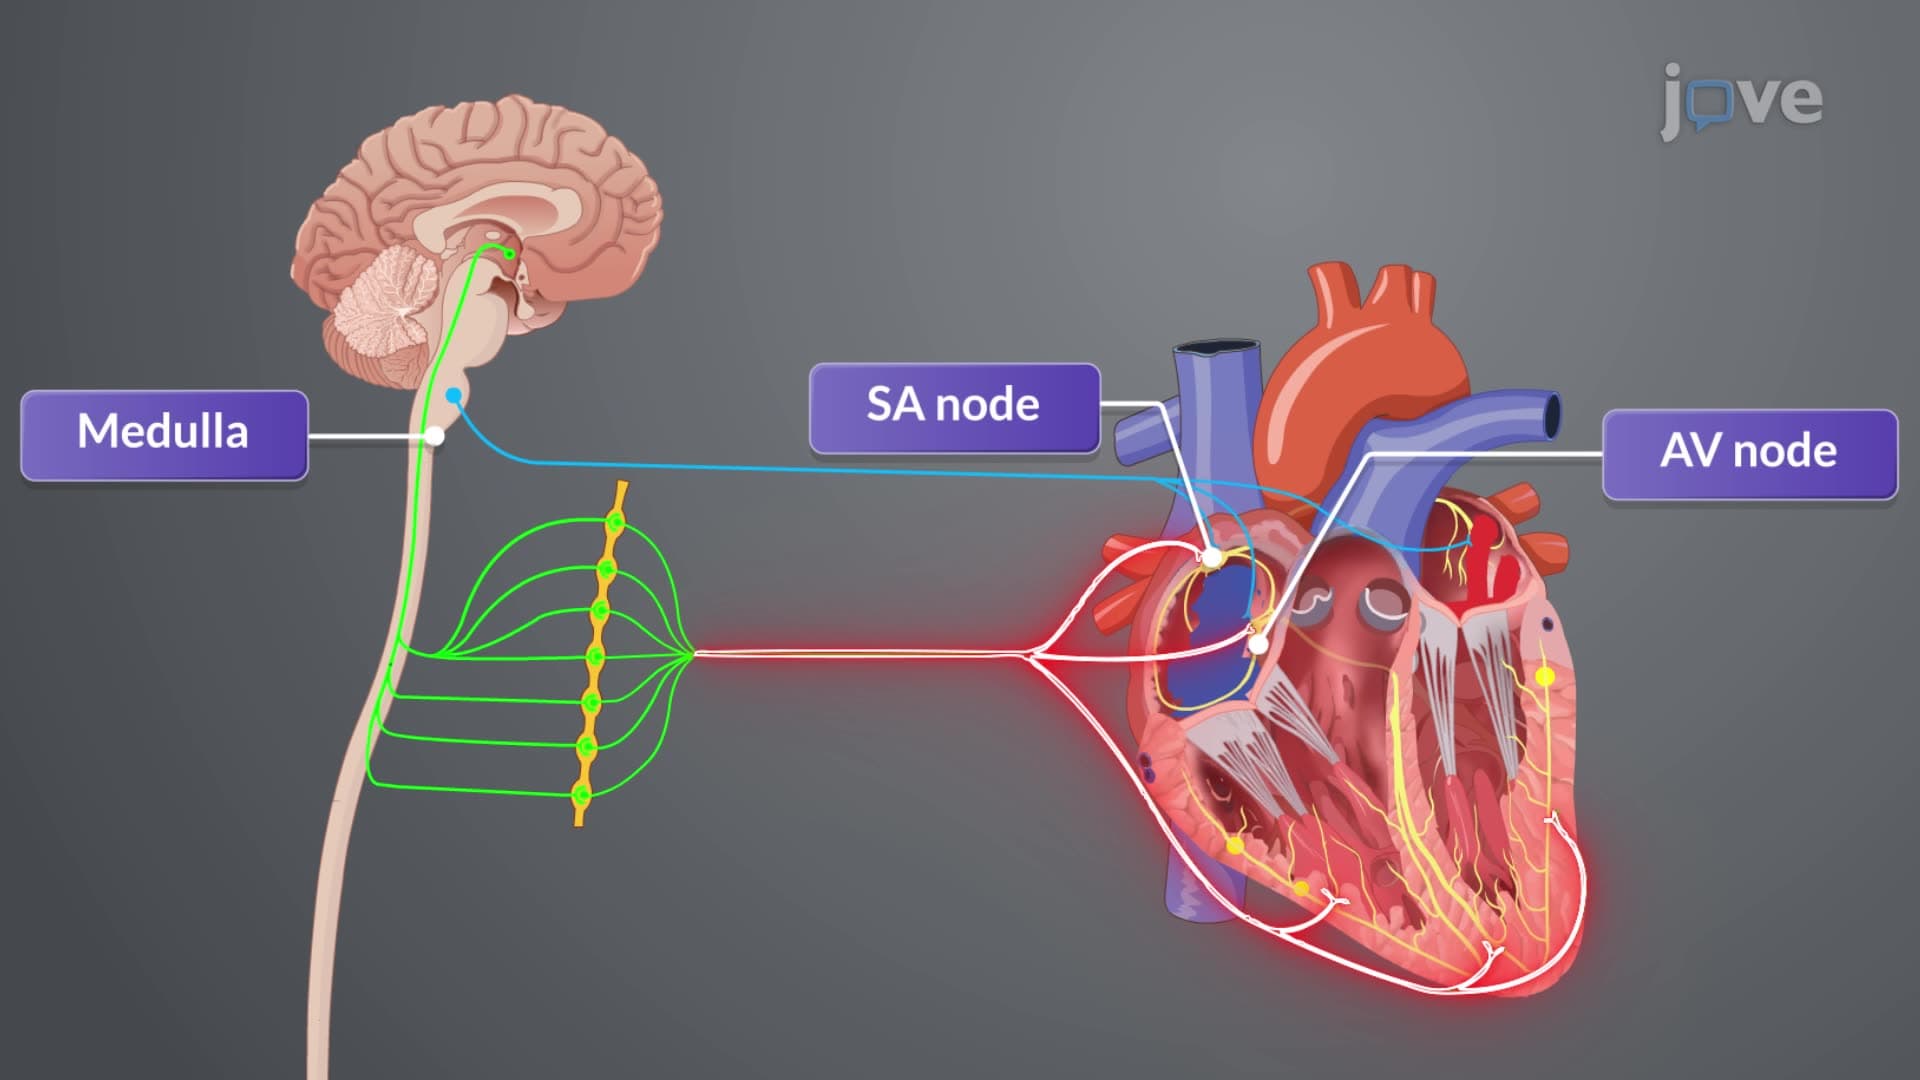
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...