Related Experiment Video
Updated: Nov 14, 2025


An Automated Culture System for Use in Preclinical Testing of Host-Directed Therapies for Tuberculosis
Published on: August 16, 2021
Low-dose amikacin in the treatment of Multidrug-resistant Tuberculosis (MDR-TB)
Natasha F Sabur1, Mantaj S Brar2, Lisa Wu3
1Department of Respirology, St. Michael's Hospital and West Park Healthcare Centre, Rm 6-049, 30 Bond St, Toronto, ON, M5B 1W8, Canada. natasha.sabur@westpark.org.

Background:
The World Health Organization recommends intravenous amikacin for the treatment of MDR-TB at a dose of 15 mg/kg. However, higher doses are associated with significant toxicity.
Methods:
Patients with MDR-TB treated at our institution receive amikacin at 8-10 mg/kg, with dose adjustment based on therapeutic drug monitoring. We conducted a retrospective cohort study of patients with MDR-TB who received amikacin between 2010 and 2016.
Results:
Forty-nine patients were included in the study. The median starting dose of amikacin was 8.9 mg/kg (IQR 8, 10), and target therapeutic drug levels were achieved at a median of 12 days (IQR 5, 26). The median duration of amikacin treatment was 7.2 months (IQR 5.7, 8), and median time to sputum culture conversion was 1 month (IQR 1,2). Six patients (12.2%) experienced hearing loss based on formal audiometry testing (95% CI 4.6-24.8%); 22.2% had subjective hearing loss (95% CI 11.2-37.1%) and 31.9% subjective tinnitus (95% CI 19.1-47.1%). Ten patients (23%) had a significant rise in serum creatinine (95% CI 11.8-38.6%), but only 5 patients had a GFR < 60 at treatment completion. 84% of patients had a successful treatment outcome (95% CI 84-99%).
Conclusions:
Low dose amikacin is associated with relatively low rates of aminoglycoside-related adverse events. We hypothesize that low-dose amikacin can be used as a safe and effective treatment for MDR-TB in situations where an adequate regimen cannot be constructed with Group A and B drugs, and where careful monitoring for adverse events is feasible.
Insights
Lower doses of amikacin (8-10 mg/kg) effectively treat multidrug-resistant tuberculosis (MDR-TB) with fewer adverse events. This approach offers a safer alternative when standard regimens are not feasible.
Area of Science:
- Pharmacology
- Infectious Diseases
- Clinical Medicine
Background:
- The World Health Organization (WHO) recommends intravenous amikacin at 15 mg/kg for multidrug-resistant tuberculosis (MDR-TB).
- Higher amikacin doses are linked to significant toxicity, posing a challenge for MDR-TB treatment.
Purpose of the Study:
- To evaluate the safety and efficacy of a lower-dose amikacin regimen (8-10 mg/kg) for MDR-TB.
- To assess adverse events and treatment outcomes in patients receiving adjusted-dose amikacin therapy.
Main Methods:
- A retrospective cohort study included 49 patients with MDR-TB treated with amikacin between 2010 and 2016.
- Amikacin doses were initiated at 8-10 mg/kg and adjusted based on therapeutic drug monitoring.
- Key outcomes included time to sputum culture conversion, adverse events (hearing loss, renal dysfunction), and treatment success.
Main Results:
- The median starting amikacin dose was 8.9 mg/kg, with target therapeutic levels reached in a median of 12 days.
- Treatment success was achieved in 84% of patients.
- Adverse events included hearing loss in 12.2% (audiometry) and 22.2% (subjective), tinnitus in 31.9%, and elevated creatinine in 23%.
Conclusions:
- Lower-dose amikacin (8-10 mg/kg) demonstrates acceptable safety and efficacy for MDR-TB treatment.
- This regimen is a viable option when standard MDR-TB drugs are insufficient, provided careful adverse event monitoring is in place.

Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:20
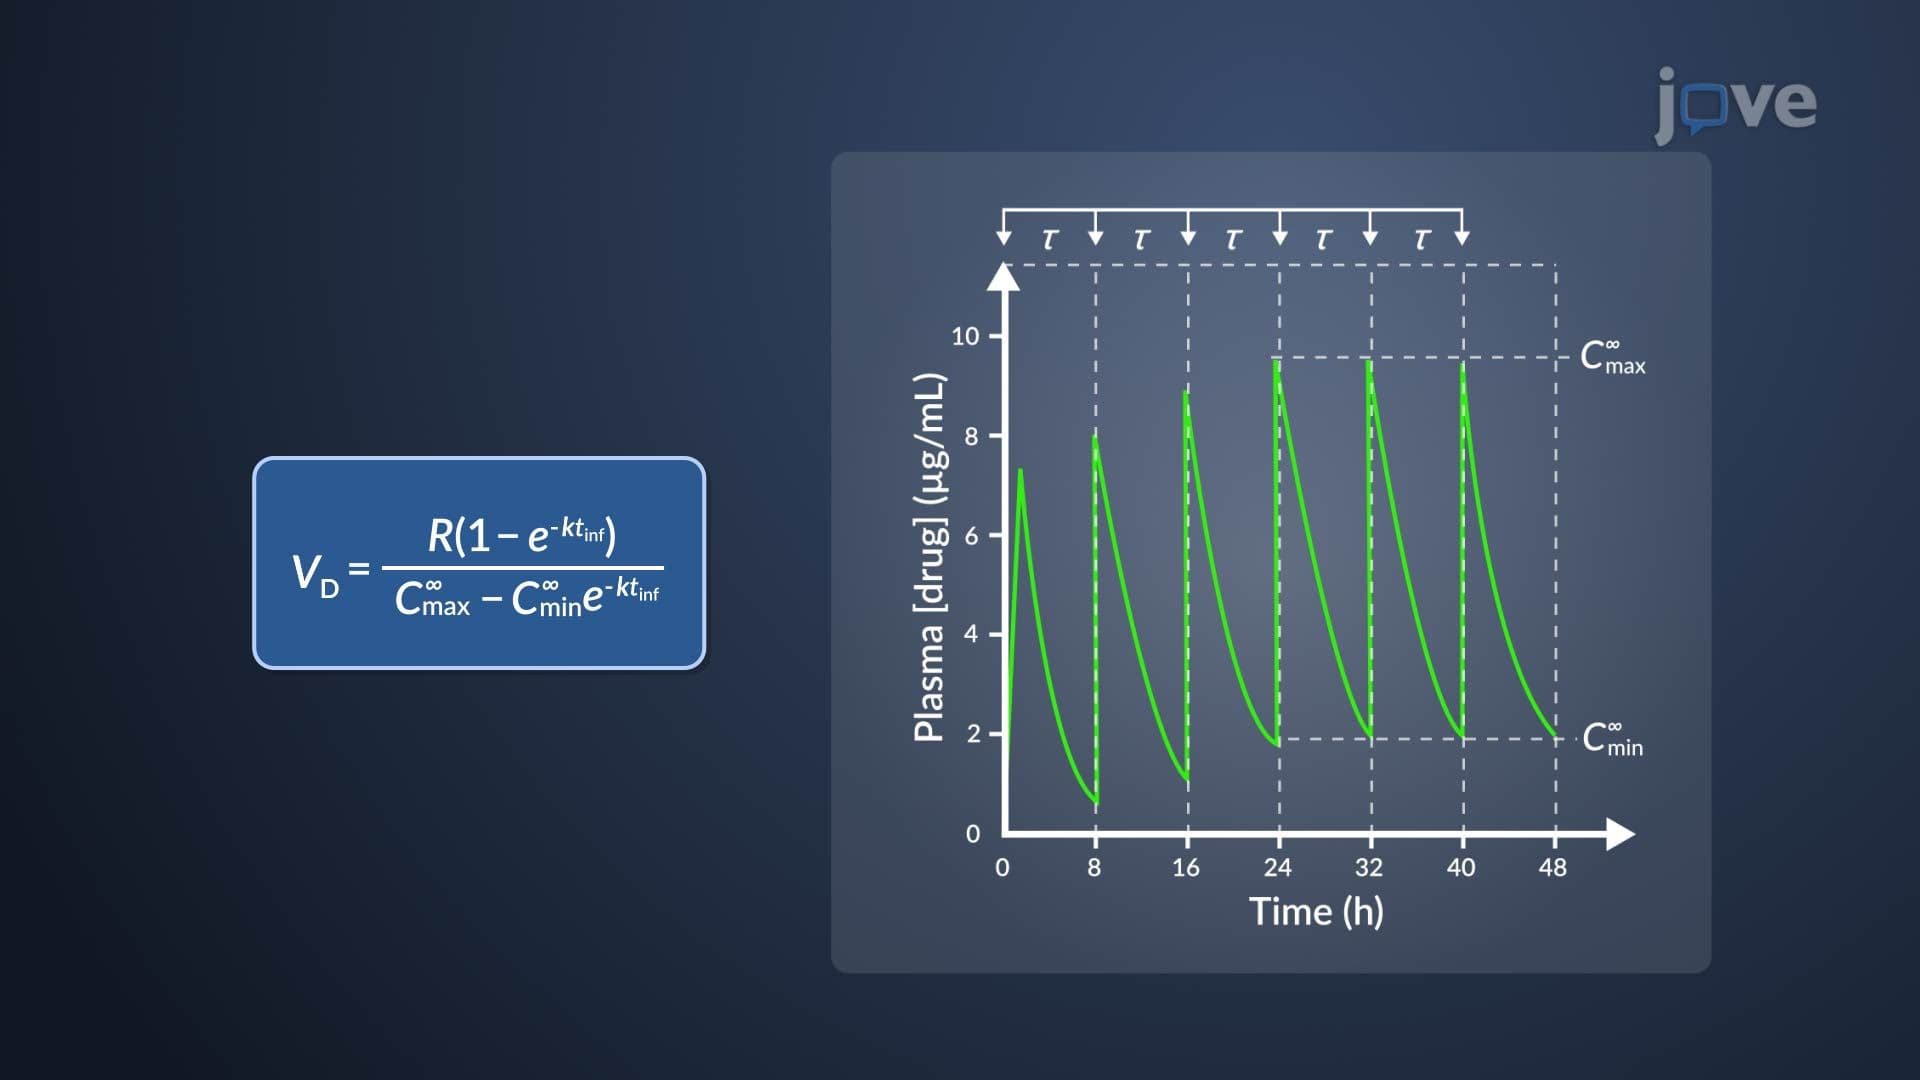
Estimation of k and VD of Aminoglycosides
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...