Related Experiment Video
Updated: Nov 14, 2025
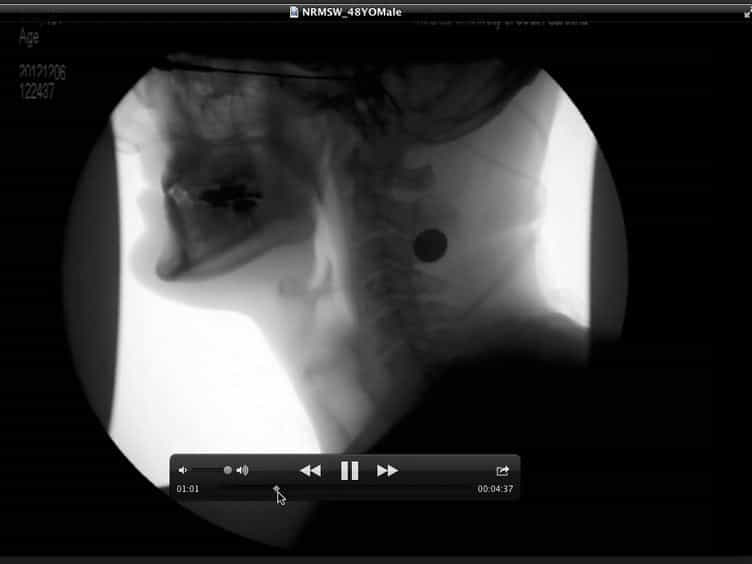
Coordinate Mapping of Hyolaryngeal Mechanics in Swallowing
Published on: May 6, 2014
Velopharyngeal Incompetence in Children With 22q11.2 Deletion Syndrome: Velar and Pharyngeal Dimensions
Rimante Seselgyte1, Marc C Swan1, Malcolm J Birch2
1North Thames Cleft Centre Great Ormond Street Hospital for Children.

Abstract:
The surgical management of velopharyngeal incompetence (VPI) in children with 22q11.2 deletion syndrome (22q11.2 DS) is challenging. There are numerous approaches and children often undergo more than one operation. Our aim was to develop a method using images from routine lateral videofluoroscopy to study the dimensions of the velopharynx in this cohort.We analyzed 22 pre-operative lateral videofluoroscopy recordings of children with 22q11.2 DS and VPI. Fourteen had a submucous cleft palate (SMCP) and 8 had no obvious palatal abnormality but who were subsequently labelled as having an occult submucous cleft palate (OSMCP). The control data were 10 historic records of children with cleft lip and an intact palate. The authors identified key points on radiographs of the velum at rest and when elevated to measure the total velar length, functional velar length and pharyngeal depth and compared them ratiometrically.The intra-observer reliability was > 0.9 whereas the inter-observer reliability was > 0.74. The velopharyngeal depth/total velar length was significantly greater in 22q11.2 DS than the control group P < 0.001. There was no difference between SMCP and OSMCP patients, P = 0.556. There was no difference in the functional velar length/total velar length between 22q11.2 DS and controls (P = 0.763).In this study, the authors demonstrate a reliable method to gain useful ratiometric measurements of the velopharynx. This may help with treatment planning. Children with 22q11.2 DS and VPI have a larger velopharyngeal depth/total velar length ratio that may explain some of the difficulty in management.
More Related Videos
 07:22
Minimally Invasive Murine Laryngoscopy for Close-Up Imaging of Laryngeal Motion During Breathing and Swallowing
Published on: December 1, 2023
 08:32
Adapting Human Videofluoroscopic Swallow Study Methods to Detect and Characterize Dysphagia in Murine Disease Models
Published on: March 1, 2015
Related Concept Videos
 01:25
Suctioning the Oropharyngeal Airway
After assembling the equipment, the nurse should practice hand hygiene and don appropriate PPE according to infection control guidelines to avoid the...
 01:20
Pharynx
Nasopharynx
The nasopharynx, bordered by the conchae of the nasal cavity, serves exclusively as an air conduit. In its superior region, the pharyngeal tonsils or adenoids are located. These tonsils are clusters of lymphoid reticular tissue akin to a lymph node. The precise...
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:25
Deglutition
Swallowing can be divided into three stages: the voluntary phase, the pharyngeal phase, and the esophageal phase. Although the...