Related Experiment Video
Updated: Nov 13, 2025


Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Effects of continuous venovenous hemofiltration on vancomycin trough concentrations in critically ill children
Lengyue Peng1, Yawen Gao1, Guangli Zhang1
1Department of Respiratory Medicine Children's Hospital of Chongqing Medical University, National Clinical Research Center for Child Health and Disorders, Ministry of Education Key Laboratory of Child Development and Disorders, Chongqing Key Laboratory of Pediatrics, Chongqing, China.

Insights
Continuous venovenous hemofiltration (CVVH) in critically ill children may increase vancomycin trough concentrations, leading to supratherapeutic levels. High Pediatric Risk of Mortality (PRISM) III scores are linked to these elevated levels.
Area of Science:
- Pediatric Critical Care Medicine
- Pharmacokinetics
- Nephrology
Background:
- Vancomycin trough concentrations are crucial for clinical outcomes and minimizing adverse drug effects in critically ill patients.
- Understanding factors influencing vancomycin levels is essential for optimizing therapy in vulnerable pediatric populations.
Purpose of the Study:
- To investigate the impact of continuous venovenous hemofiltration (CVVH) on vancomycin trough concentrations in critically ill children.
- To identify risk factors associated with supratherapeutic vancomycin trough concentrations during CVVH therapy.
Main Methods:
- Retrospective analysis of critically ill children (January 2016-December 2019) with steady-state vancomycin trough concentrations.
- Patients were categorized into CVVH and non-CVVH groups based on treatment and renal function.
- Comparison of vancomycin trough concentrations and logistic regression analysis for risk factors of supratherapeutic levels (>20 mg/L).
Main Results:
- The CVVH group (n=35) exhibited significantly higher median vancomycin trough concentrations compared to the non-CVVH group (n=84) [14.9 vs. 9.3 mg/L].
- While therapeutic concentrations (10-20 mg/L) were similar, the CVVH group had a higher proportion of supratherapeutic concentrations (20.0% vs. 1.2%).
- Pediatric Risk of Mortality (PRISM) III score ≥28 was identified as an independent risk factor for supratherapeutic vancomycin trough concentrations (OR =13.7).
Conclusions:
- Continuous venovenous hemofiltration (CVVH) therapy significantly influences vancomycin trough concentrations in critically ill children, increasing the risk of supratherapeutic levels with a 40-60 mg/kg/day dosage.
- Elevated Pediatric Risk of Mortality (PRISM) III scores (≥28) are independently associated with supratherapeutic vancomycin trough concentrations in pediatric patients undergoing CVVH.
Background:
Vancomycin trough concentrations are associated with clinical outcomes and drug adverse effects. This study investigates the effects of continuous venovenous hemofiltration (CVVH) on vancomycin trough concentrations in critically ill children with a vancomycin dosage of 40-60 mg/kg/day.
Methods:
Children with steady-state vancomycin trough concentrations admitted to the pediatric intensive care unit (PICU) between January 2016 and December 2019 were retrospectively enrolled. Patients were divided into CVVH and non-CVVH groups according to treatment differences and renal function. Vancomycin trough concentrations were then compared between the groups, and risk factors for supratherapeutic trough concentrations (>20 mg/L) were analyzed with logistic regression.
Results:
Of the 119 patients included, 35 were enrolled in the CVVH group and 84 in the non-CVVH group. Median vancomycin trough concentrations were significantly higher in the CVVH group than those in the non-CVVH group [14.9 (IQR =9.6-19.6) vs. 9.3 (IQR =7.0-13.4), P<0.001] and the proportion of therapeutic trough concentrations (10-20 mg/L) was similar between CVVH and non-CVVH groups (54.3% vs. 39.3%, P=0.133). However, CVVH therapy patients had a significantly higher proportion of supratherapeutic trough concentrations (20.0% vs. 1.2%, P=0.001) compared to the non-CVVH group. Multivariate analysis demonstrated that the Pediatric Risk of Mortality (PRISM) III score ≥28 (OR =13.7; 95% CI, 1.4-137.0; P=0.026] was an independent risk factor for supratherapeutic trough concentrations in critically ill patients.
Conclusions:
CVVH therapy affects vancomycin trough concentrations and is associated with supratherapeutic concentrations with a 40-60 mg/kg/day vancomycin dosage. PRISM III scores ≥28 may serve as an independent risk factor for supratherapeutic trough concentrations in children receiving CVVH therapy.
Related Concept Videos
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:20
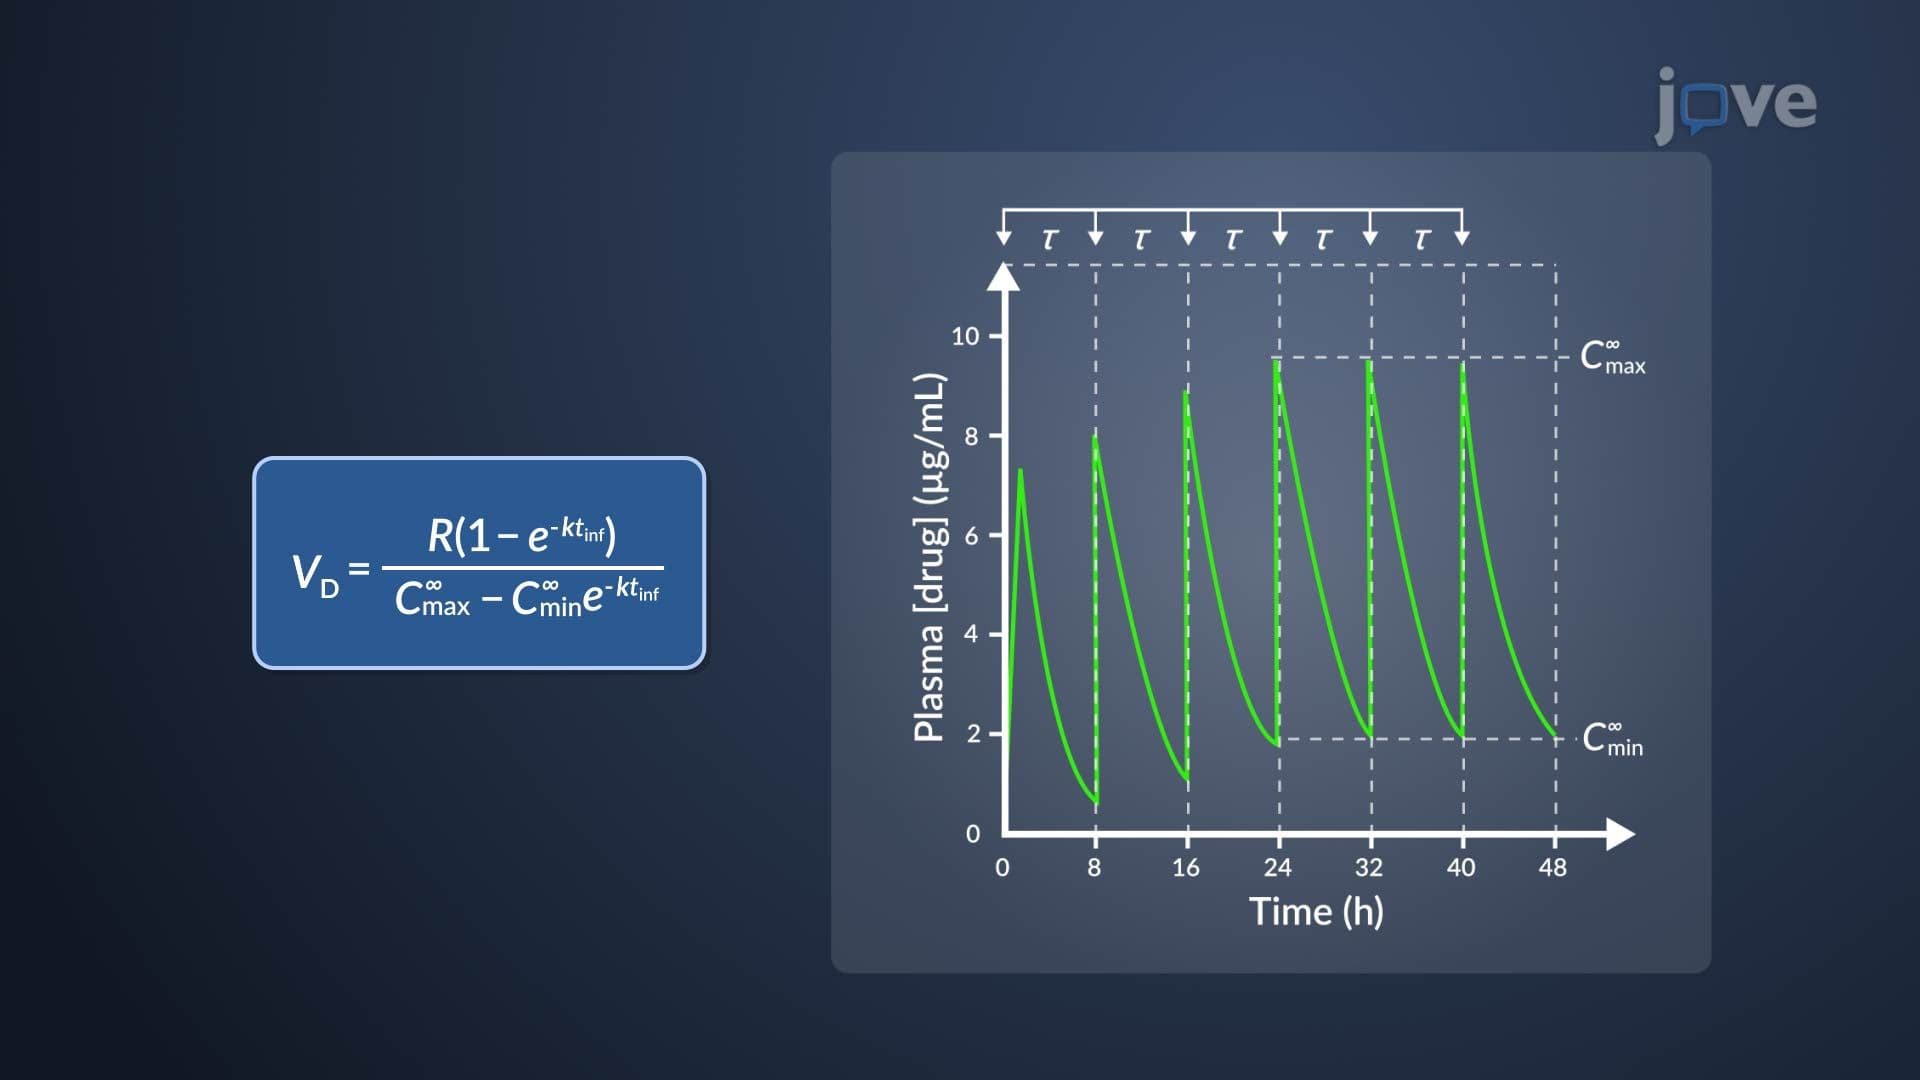
Estimation of k and VD of Aminoglycosides