Related Experiment Video
Updated: Nov 12, 2025

ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
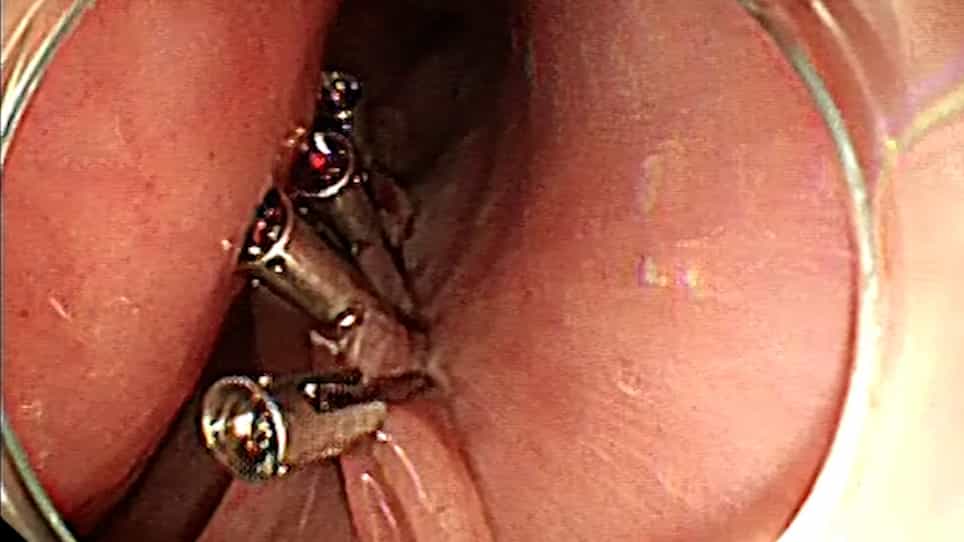
Modified endoscopic radial incision and cutting method (M-RIC) for the treatment of refractory esophageal stricture
Ye Zhu1,2, Sachin Mulmi Shrestha2, Ting Yu2
1College of Joint Training with Southeast University, Nanjing Medical University, Nanjing, China.

Background:
Refractory esophageal stricture is difficult to deal with. Some refractory stricture shows little response to now-existing endoscopic techniques. We assessed the efficacy of modified endoscopic radial incision and cutting method (M-RIC) for the treatment of refractory esophageal stricture.
Methods:
This was a retrospective study. Patients with refractory esophageal stricture who underwent M-RIC or dilation from June 2016 to June 2020 were included. Outcomes measured included technical and clinical success, restenosis rate, time to restenosis and complications. Risk factors for restenosis after M-RIC were assessed.
Results:
67 patients were enrolled (M-RIC group, n = 29; dilation group, n = 38). After propensity score matching, each group include 28 patients. There were no significant differences in technical success (96.4% vs 100%, p = 1.00) or clinical success (89.3% vs 100%, p = 0.23) between groups. Patients in M-RIC group had lower rates of restenosis (75% vs. 100%, p = 0.02) and longer time to restenosis (110 days vs 31.5 days, p = 0.00) compared with dilation group. 4 patients did not require any additional treatment after M-RIC and maintained food intake until the end of follow-up. Complications of M-RIC include perforation, fever and retrosternal pain, and no difference was found in total complication rate when compared with dilation group (25% vs 7.1%, p = 0.07). Although 3 out of 28 patients (10.7%) in M-RIC group had perforation, the perforation rate was not significantly different between groups (p = 0.11). Multivariate analyze suggested stricture length ≥ 5 cm (HR 7.25, p = 0.00) was a risk factor to restenosis while oral prednisone (HR 0.29, p = 0.02) was associated with preventing restenosis after M-RIC.
Conclusion:
M-RIC is a feasible and effective technique for refractory esophageal stricture with lower rate and longer time to restenosis. Stricture length ≥ 5 cm is a risk factor to restenosis while oral prednisone is helpful in remitting restenosis after M-RIC.
More Related Videos

Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Endoscopic Procedures V: ERCP
Patient...