Related Experiment Video
Updated: Nov 12, 2025
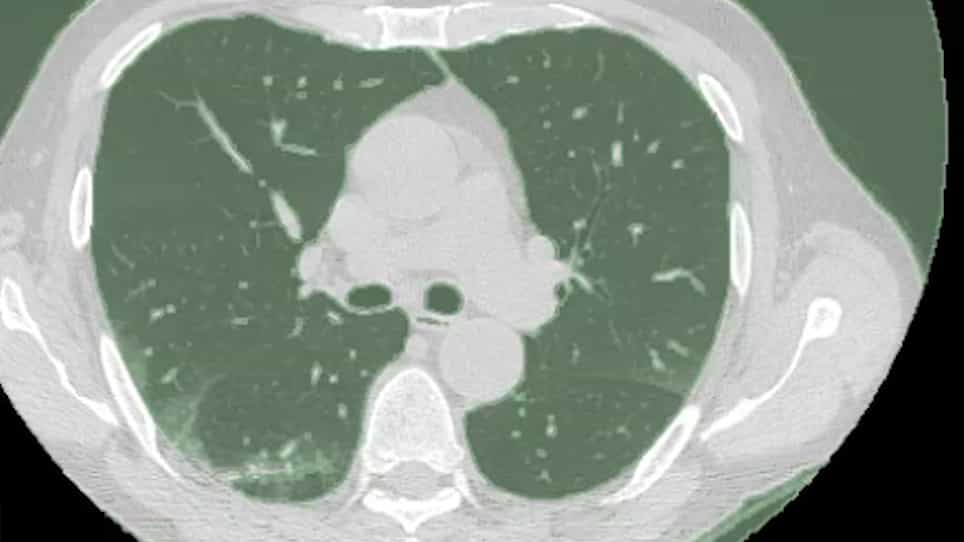

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
High Incidence of Barotrauma in Patients With Severe Coronavirus Disease 2019
Michael R Kahn1, Richard L Watson2, Jay T Thetford1
1Department of Medicine, 12222UCLA-Olive View Medical Center, David Geffen School of Medicine at UCLA, Los Angeles, CA, USA.

Insights
Critically ill COVID-19 patients experienced a high incidence of barotrauma, particularly those on invasive mechanical ventilation. This lung injury was linked to longer hospital stays and increased tracheostomy rates.
Area of Science:
- Critical Care Medicine
- Pulmonology
- Infectious Diseases
Background:
- Barotrauma is a known complication of mechanical ventilation in Acute Respiratory Distress Syndrome (ARDS).
- The incidence of barotrauma in patients with coronavirus disease 2019 (COVID-19) is not well-established.
- Understanding barotrauma incidence in COVID-19 is crucial for optimizing patient management.
Purpose of the Study:
- To determine the incidence of barotrauma in critically ill COVID-19 patients.
- To explore the implications and associated factors of barotrauma in this population.
Main Methods:
- Retrospective cohort study design.
- Inclusion of 75 critically ill COVID-19 patients admitted to an intensive care unit (ICU).
- Analysis of barotrauma incidence based on ventilation type (invasive mechanical ventilation [IMV] vs. non-invasive ventilation [NIV]).
Main Results:
- 21% of severe COVID-19 patients developed barotrauma, with higher rates in those on IMV (33%) versus NIV (8%).
- Barotrauma was associated with increased tracheostomy rates, longer ICU stays (17 vs. 7 days), and longer hospitalization (26 vs. 14 days).
- Patients with barotrauma showed a trend towards higher mortality (56% vs. 37%) and longer IMV duration.
Conclusions:
- Critically ill COVID-19 patients exhibit a high incidence of barotrauma, exceeding rates typically seen in ARDS.
- The pathophysiology of COVID-19 may contribute to this increased susceptibility to lung injury.
- Lung-protective ventilation strategies remain essential for managing these patients.
Objective.:
To report the high incidence of barotrauma in critically ill patients admitted to the intensive care unit (ICU) with coronavirus disease 2019 (COVID-19) and to discuss its implications.
Design.:
Retrospective cohort study.
Setting.:
ICU of an academic county hospital in Los Angeles, CA admitted from March 15-June 20, 2020.
Patients.:
77 patients with COVID-19 pneumonia. 75 patients met inclusion criteria.
Results.:
21% of patients with severe COVID-19 sustained barotrauma (33% of patients receiving IMV, 8% of patients receiving (NIV). There were no differences between the barotrauma and non-barotrauma groups regarding demographics, illness severity, or medications received, nor tidal volume or average/peak airway pressures in those receiving IMV. In the barotrauma group there was a greater proportion of patients receiving therapeutic anticoagulation (81% vs. 47%, p = 0.023) and ventilated using airway pressure release ventilation mode (13% vs. 0%, p = 0.043). Barotrauma was associated with increased likelihood of receiving a tracheostomy (OR 2.58 [0.23-4.9], p = 0.018]), longer median ICU length of stay (17 days vs. 7 days, p = 0.03), and longer median length of hospitalization (26 days vs. 14 days, p < 0.001). There was also a trend toward prolonged median duration of IMV (12.5 days vs 7 days, p = 0.13) and higher average mortality (56% vs 37%, p = 0.25).
Conclusions.:
Barotrauma is seen in 5-12% of patients with ARDS receiving IMV and is exceedingly rare in patients receiving NIV. We report a high incidence of barotrauma observed in critically ill patients with COVID-19 requiring either NIV or IMV. While there was a trend toward increased mortality in patients with barotrauma, this did not reach statistical significance. The increased incidence of barotrauma with COVID-19 may be a product of the pathophysiology of this disease state and a heightened inflammatory response causing rampant acute lung injury. Evidence-based medicine and lung-protective ventilation should remain the mainstay of treatment.
More Related Videos


Related Concept Videos
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:27
Pneumothorax-II
Clinical Manifestations: