Related Experiment Video
Updated: Nov 12, 2025
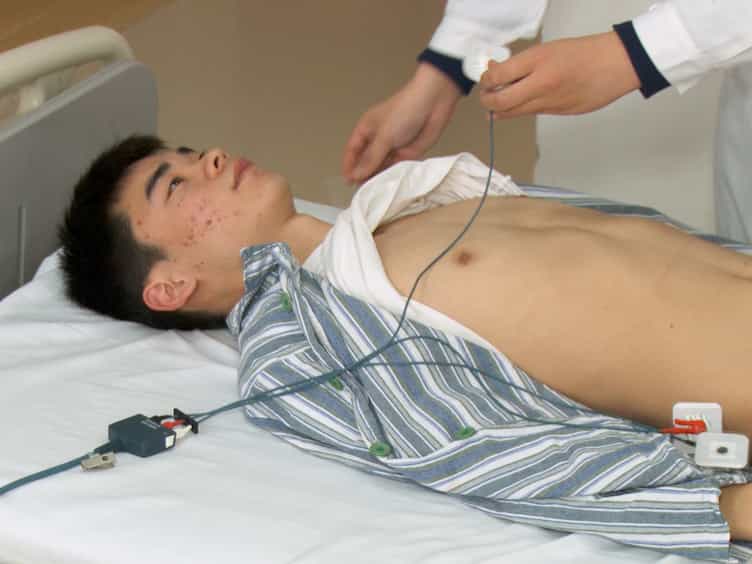

Measuring the Carotid to Femoral Pulse Wave Velocity Cf-PWV to Evaluate Arterial Stiffness
Published on: May 3, 2018
The relationship between ambulatory arterial stiffness, inflammation, blood pressure dipping and cardiovascular
Christopher J Boos1,2,3, Lin-Thiri Toon4, Halah Almahdi4
1Department of Cardiology, University Hospital Dorset NHS Foundation Trust, Longfleet Rd., Poole, BH15 2JB, UK. christopherboos@hotmail.com.

Background:
The ambulatory arterial stiffness index (AASI) is an indirect measure of arterial stiffness obtained during ambulatory blood pressuring monitoring (ABPM). Its relationship to nocturnal blood pressure dipping status and major adverse cardiovascular events (MACE) are controversial and its association with vascular inflammation has not been examined. We aimed to investigate the relationship between the AASI, inflammation and nocturnal blood pressure dipping status and its association with MACE.
Methods:
Adults (aged 18-80 years) who underwent 24-h ABPM for the diagnosis of hypertension or its control were included. The inflammatory markers measured were the neutrophil-lymphocyte (NLR), platelet-lymphocyte (PLR) and monocyte-lymphocyte ratios (MLR). The primary MACE was a composite of cardiovascular death, acute limb ischaemia, stroke or transient ischaemic attack (TIA) or acute coronary syndrome.
Results:
A total of 508 patients (51.2% female) aged 58.8 ± 14.0 years were included; 237 (46.7%) were normal-dippers (≥ 10% nocturnal systolic dip), 214 (42.1%) were non-dippers (0-10% dip) and 57 (11.2%) were reverse-dippers (< 0% dip). The AASI was significantly higher among reverse (0.56 ± 0.16) and non-dippers (0.48 ± 0.17) compared with normal dippers (0.39 ± 0.16; p < 0.0001) and correlated with the NLR (r = 0.20; 95% CI 0.11 to 0.29: < 0.0001) and systolic blood pressure dipping % (r = - 0.34; - 0.42 to - 0.26: p < 0.0001). Overall 39 (7.7%) patients had ≥ 1 MACE which included a total of seven cardiovascular deaths and 14 non-fatal strokes/TIAs. The mean follow up was 113.7 ± 64.0 weeks. Increasing NLR, but not AASI or systolic dipping, was independently linked to MACE (overall model Chi-square 60.67; p < 0.0001) and MLR to cardiovascular death or non-fatal stroke/TIA (overall model Chi-square 37.08; p < 0.0001).
Conclusions:
In conclusion AASI was associated with blood pressure dipping and chronic inflammation but not independently to MACE. The MLR and NLR were independent predictors of MACE.

Related Concept Videos
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:17
Measurement of Blood Pressure
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:23
Assessment of blood pressure in brachial artery(two-step method)