Related Experiment Video
Updated: Nov 12, 2025

In vitro Assessment of Myocardial Protection following Hypothermia-Preconditioning in a Human Cardiac Myocytes Model
Published on: October 27, 2020
Maintaining intravenous volume mitigates hypothermia-induced myocardial dysfunction and accumulation of intracellular
Jan Harald Nilsen1,2,3, Torstein Schanche1,4, Timofei V Kondratiev1
1Anesthesia and Critical Care research group, Department of Clinical Medicine, UiT, Arctic University of Norway, Tromsø, Norway.

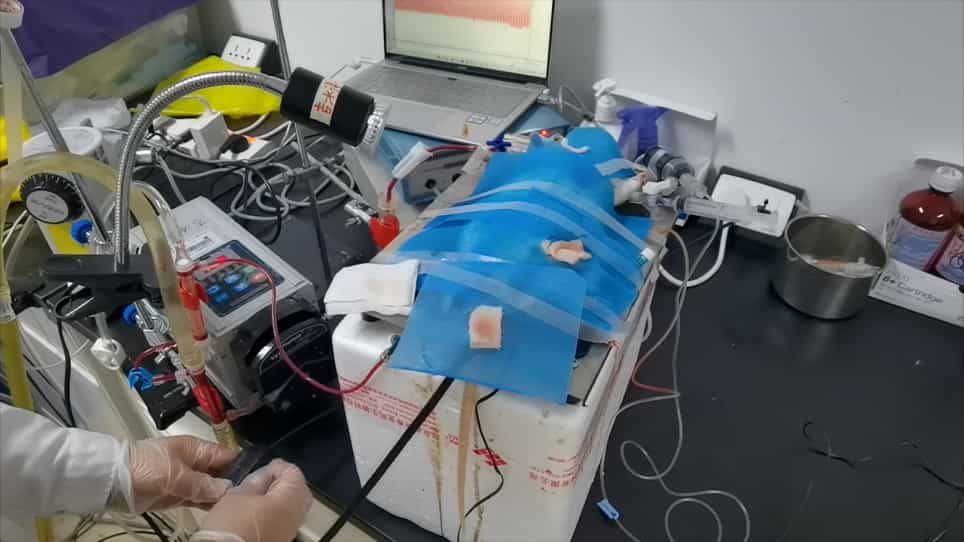
Previous research exploring pathophysiological mechanisms underlying circulatory collapse after rewarming victims of severe accidental hypothermia has documented post-hypothermic cardiac dysfunction and hypothermia-induced elevation of intracellular Ca2+ concentration ([Ca2+ ]i ) in myocardial cells. The aim of the present study was to examine if maintaining euvolaemia during rewarming mitigates cardiac dysfunction and/or normalizes elevated myocardial [Ca2+ ]i . A total of 21 male Wistar rats (300 g) were surface cooled to 15°C, then maintained at 15°C for 4 h, and subsequently rewarmed to 37°C. The rats were randomly assigned to one of three groups: (1) non-intervention control (n = 7), (2) dextran treated (i.v. 12 ml/kg dextran 70; n = 7), or (3) crystalloid treated (24 ml/kg 0.9% i.v. saline; n = 7). Infusions occurred during the first 30 min of rewarming. Arterial blood pressure, stroke volume (SV), cardiac output (CO), contractility (dP/dtmax ) and blood gas changes were measured. Post-hypothermic changes in [Ca2+ ]i were measured using the method of radiolabelled Ca2+ (45 Ca2+ ). Untreated controls displayed post-hypothermic cardiac dysfunction with significantly reduced CO, SV and dP/dtmax . In contrast, rats receiving crystalloid or dextran treatment showed a return to pre-hypothermic control levels of CO and SV after rewarming, with the dextran group displaying significantly better amelioration of post-hypothermic cardiac dysfunction than the crystalloid group. Compared to the post-hypothermic increase in myocardial [Ca2+ ]i in non-treated controls, [Ca2+ ]i values with crystalloid and dextran did not increase to the same extent after rewarming. Volume replacement with crystalloid or dextran during rewarming abolishes post-hypothermic cardiac dysfunction, and partially mitigates the hypothermia-induced elevation of [Ca2+ ]i .
New Findings:
What is the central question of this study? Detailed guidelines for volume replacement to counteract hypothermia-induced intravascular fluid loss are lacking. Evidence suggests colloids might have beneficial effects compared to crystalloids. Are central haemodynamic function and level of hypothermia-induced calcium overload, as a marker of cardiac injury, restored by fluid substitution during rewarming, and are colloids favourable to crystalloids? What is the main finding and its importance? Infusion with crystalloid or dextran during rewarming abolished post-hypothermic cardiac dysfunction, and partially mitigated myocardial calcium overload. The effects of volume replacement to support haemodynamic function are comparable to those using potent cardio-active drugs. These findings underline the importance of applying intravascular volume replacement to maintain euvolaemia during rewarming.
Previous research exploring pathophysiological mechanisms underlying circulatory collapse after rewarming victims of severe accidental hypothermia has documented post-hypothermic cardiac dysfunction and hypothermia-induced elevation of intracellular Ca2+ concentration ([Ca2+ ]i ) in myocardial cells. The aim of the present study was to examine if maintaining euvolaemia during rewarming mitigates cardiac dysfunction and/or normalizes elevated myocardial [Ca2+ ]i . A total of 21 male Wistar rats (300 g) were surface cooled to 15°C, then maintained at 15°C for 4 h, and subsequently rewarmed to 37°C. The rats were randomly assigned to one of three groups: (1) non-intervention control (n = 7), (2) dextran treated (i.v. 12 ml/kg dextran 70; n = 7), or (3) crystalloid treated (24 ml/kg 0.9% i.v. saline; n = 7). Infusions occurred during the first 30 min of rewarming. Arterial blood pressure, stroke volume (SV), cardiac output (CO), contractility (dP/dtmax ) and blood gas changes were measured. Post-hypothermic changes in [Ca2+ ]i were measured using the method of radiolabelled Ca2+ (45 Ca2+ ). Untreated controls displayed post-hypothermic cardiac dysfunction with significantly reduced CO, SV and dP/dtmax . In contrast, rats receiving crystalloid or dextran treatment showed a return to pre-hypothermic control levels of CO and SV after rewarming, with the dextran group displaying significantly better amelioration of post-hypothermic cardiac dysfunction than the crystalloid group. Compared to the post-hypothermic increase in myocardial [Ca2+ ]i in non-treated controls, [Ca2+ ]i values with crystalloid and dextran did not increase to the same extent after rewarming. Volume replacement with crystalloid or dextran during rewarming abolishes post-hypothermic cardiac dysfunction, and partially mitigates the hypothermia-induced elevation of [Ca2+ ]i .

Related Concept Videos
 01:22
Heart Failure VI: Adjunct Therapies
 01:29
Cardiomyopathy V: Interprofessional Care
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:29
Decreased Body Temperature
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...