Transfer of triptans into human breast milk and estimation of infant drug exposure through breastfeeding
Related Experiment Video
Updated: Nov 12, 2025
Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Siri Amundsen1,2, Hedvig Nordeng3, Ole-Martin Fuskevåg1,2
1Department of Laboratory Medicine, University Hospital of North Norway, Tromsø, Norway.

Clinical data on the transfer of triptans into human breast milk remain scarce. In a lactation study including 19 breastfeeding women with migraine, we examined the excretion of six different triptans into milk. Following intake of a single dose, each participant collected seven breast milk samples at predefined intervals up to 24 hours after dose. Triptan concentrations in milk were measured using liquid chromatography-tandem mass spectrometry (LC-MS/MS). Infant drug exposure was estimated by calculating the relative infant dose (RID). Twenty-two breast milk sample sets were obtained for sumatriptan (n = 8), rizatriptan (n = 5), zolmitriptan (n = 4), eletriptan (n = 3), almotriptan (n = 1) and naratriptan (n = 1). Based on the average concentration in milk throughout the day, estimated mean RIDs (with range in parenthesis) were as follows: eletriptan 0.6% (0.3%-0.8%), sumatriptan 0.7% (0.2%-1.8%), rizatriptan 0.9% (0.3%-1.4%), almotriptan 1.8% (-), zolmitriptan 2.1% (0.7%-5.3%) and naratriptan 5.0% (-). Infant drug exposure through breastfeeding appears to be low and indicates that use of the triptans in this study is compatible with breastfeeding. Naratriptan may not be first choice in breastfeeding mothers initiating triptans during the neonatal period.
Clinical data on the transfer of triptans into human breast milk remain scarce. In a lactation study including 19 breastfeeding women with migraine, we examined the excretion of six different triptans into milk. Following intake of a single dose, each participant collected seven breast milk samples at predefined intervals up to 24 hours after dose. Triptan concentrations in milk were measured using liquid chromatography-tandem mass spectrometry (LC-MS/MS). Infant drug exposure was estimated by calculating the relative infant dose (RID). Twenty-two breast milk sample sets were obtained for sumatriptan (n = 8), rizatriptan (n = 5), zolmitriptan (n = 4), eletriptan (n = 3), almotriptan (n = 1) and naratriptan (n = 1). Based on the average concentration in milk throughout the day, estimated mean RIDs (with range in parenthesis) were as follows: eletriptan 0.6% (0.3%-0.8%), sumatriptan 0.7% (0.2%-1.8%), rizatriptan 0.9% (0.3%-1.4%), almotriptan 1.8% (-), zolmitriptan 2.1% (0.7%-5.3%) and naratriptan 5.0% (-). Infant drug exposure through breastfeeding appears to be low and indicates that use of the triptans in this study is compatible with breastfeeding. Naratriptan may not be first choice in breastfeeding mothers initiating triptans during the neonatal period.
More Related Videos
 13:00
Intranasal Immunization and Milk Collection in Studies of Maternal Immunization in New Zealand White Rabbits Oryctolagus cuniculus
Published on: July 31, 2021
 09:04
Comprehensive Evaluation of the Effectiveness and Safety of Placenta-Targeted Drug Delivery Using Three Complementary Methods
Published on: September 10, 2018
Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:10
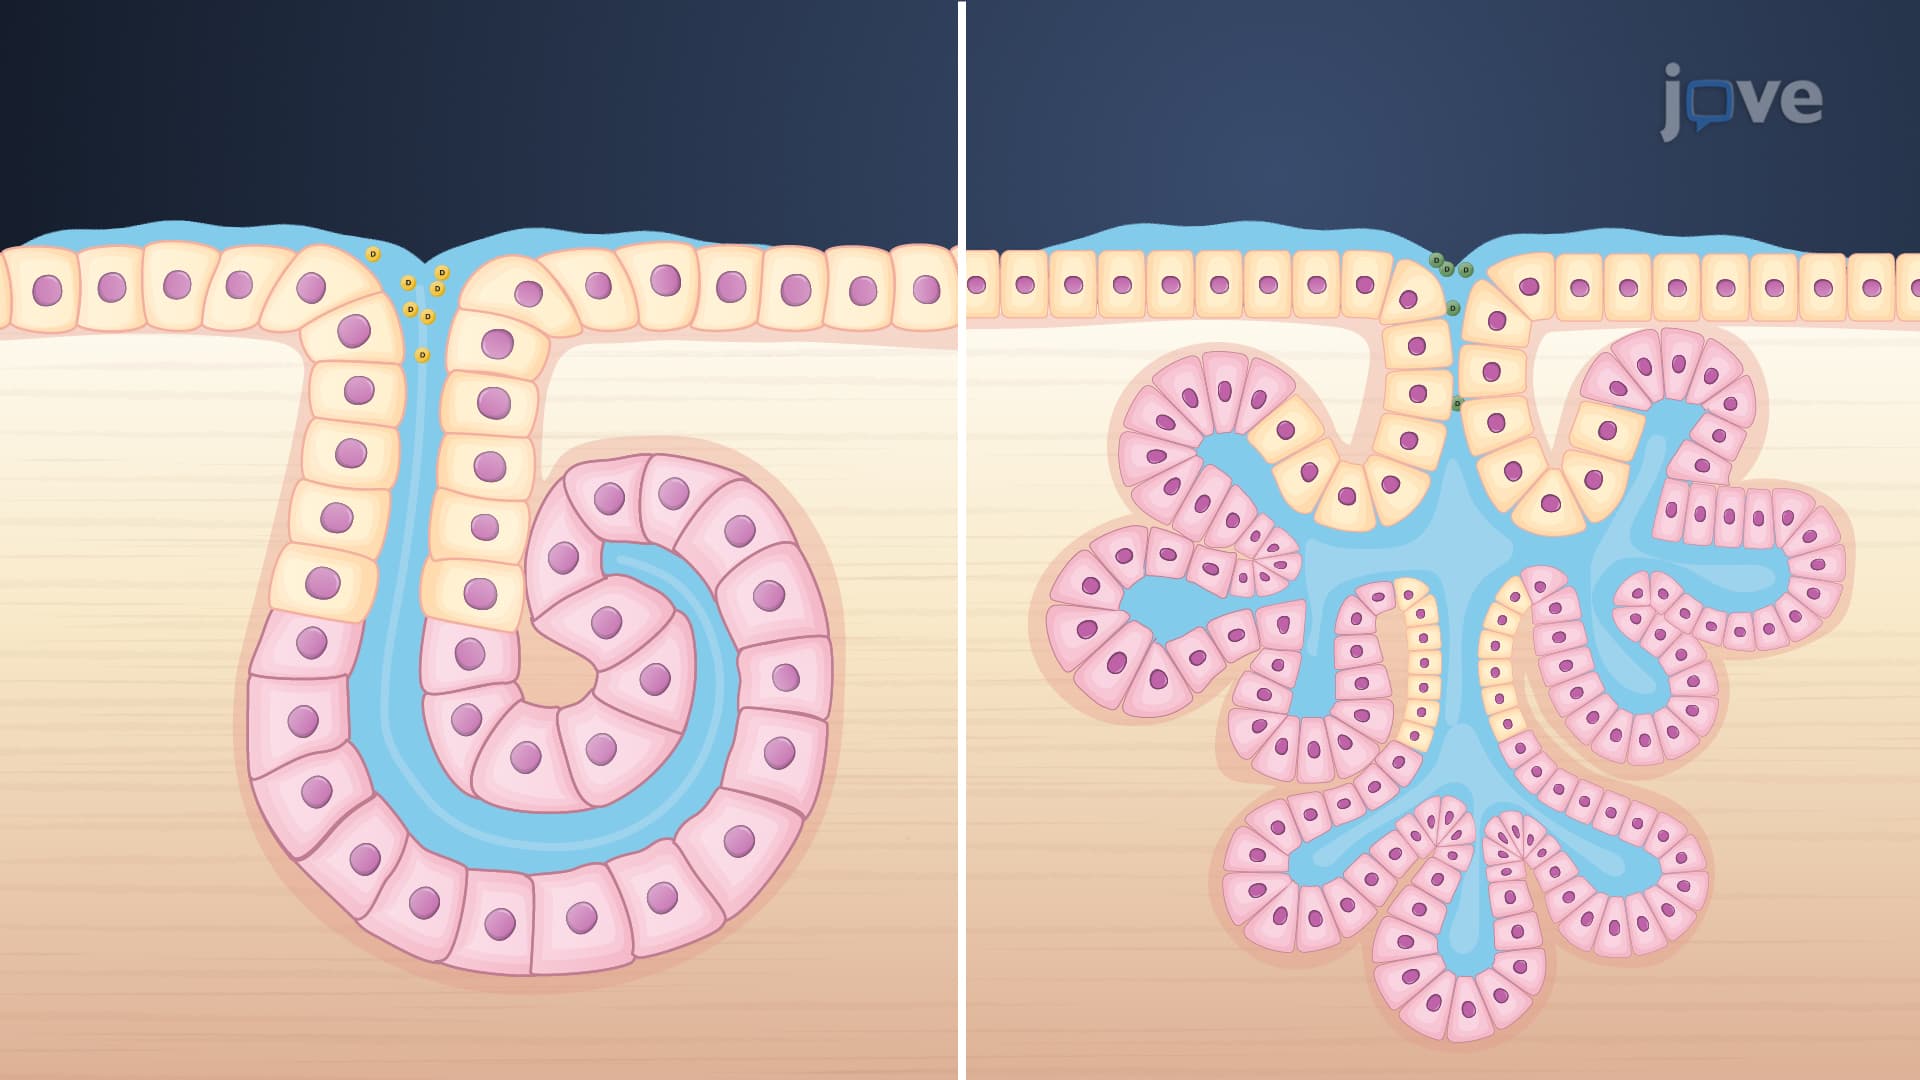
Drug Excretion: Miscellaneous Routes
 01:22
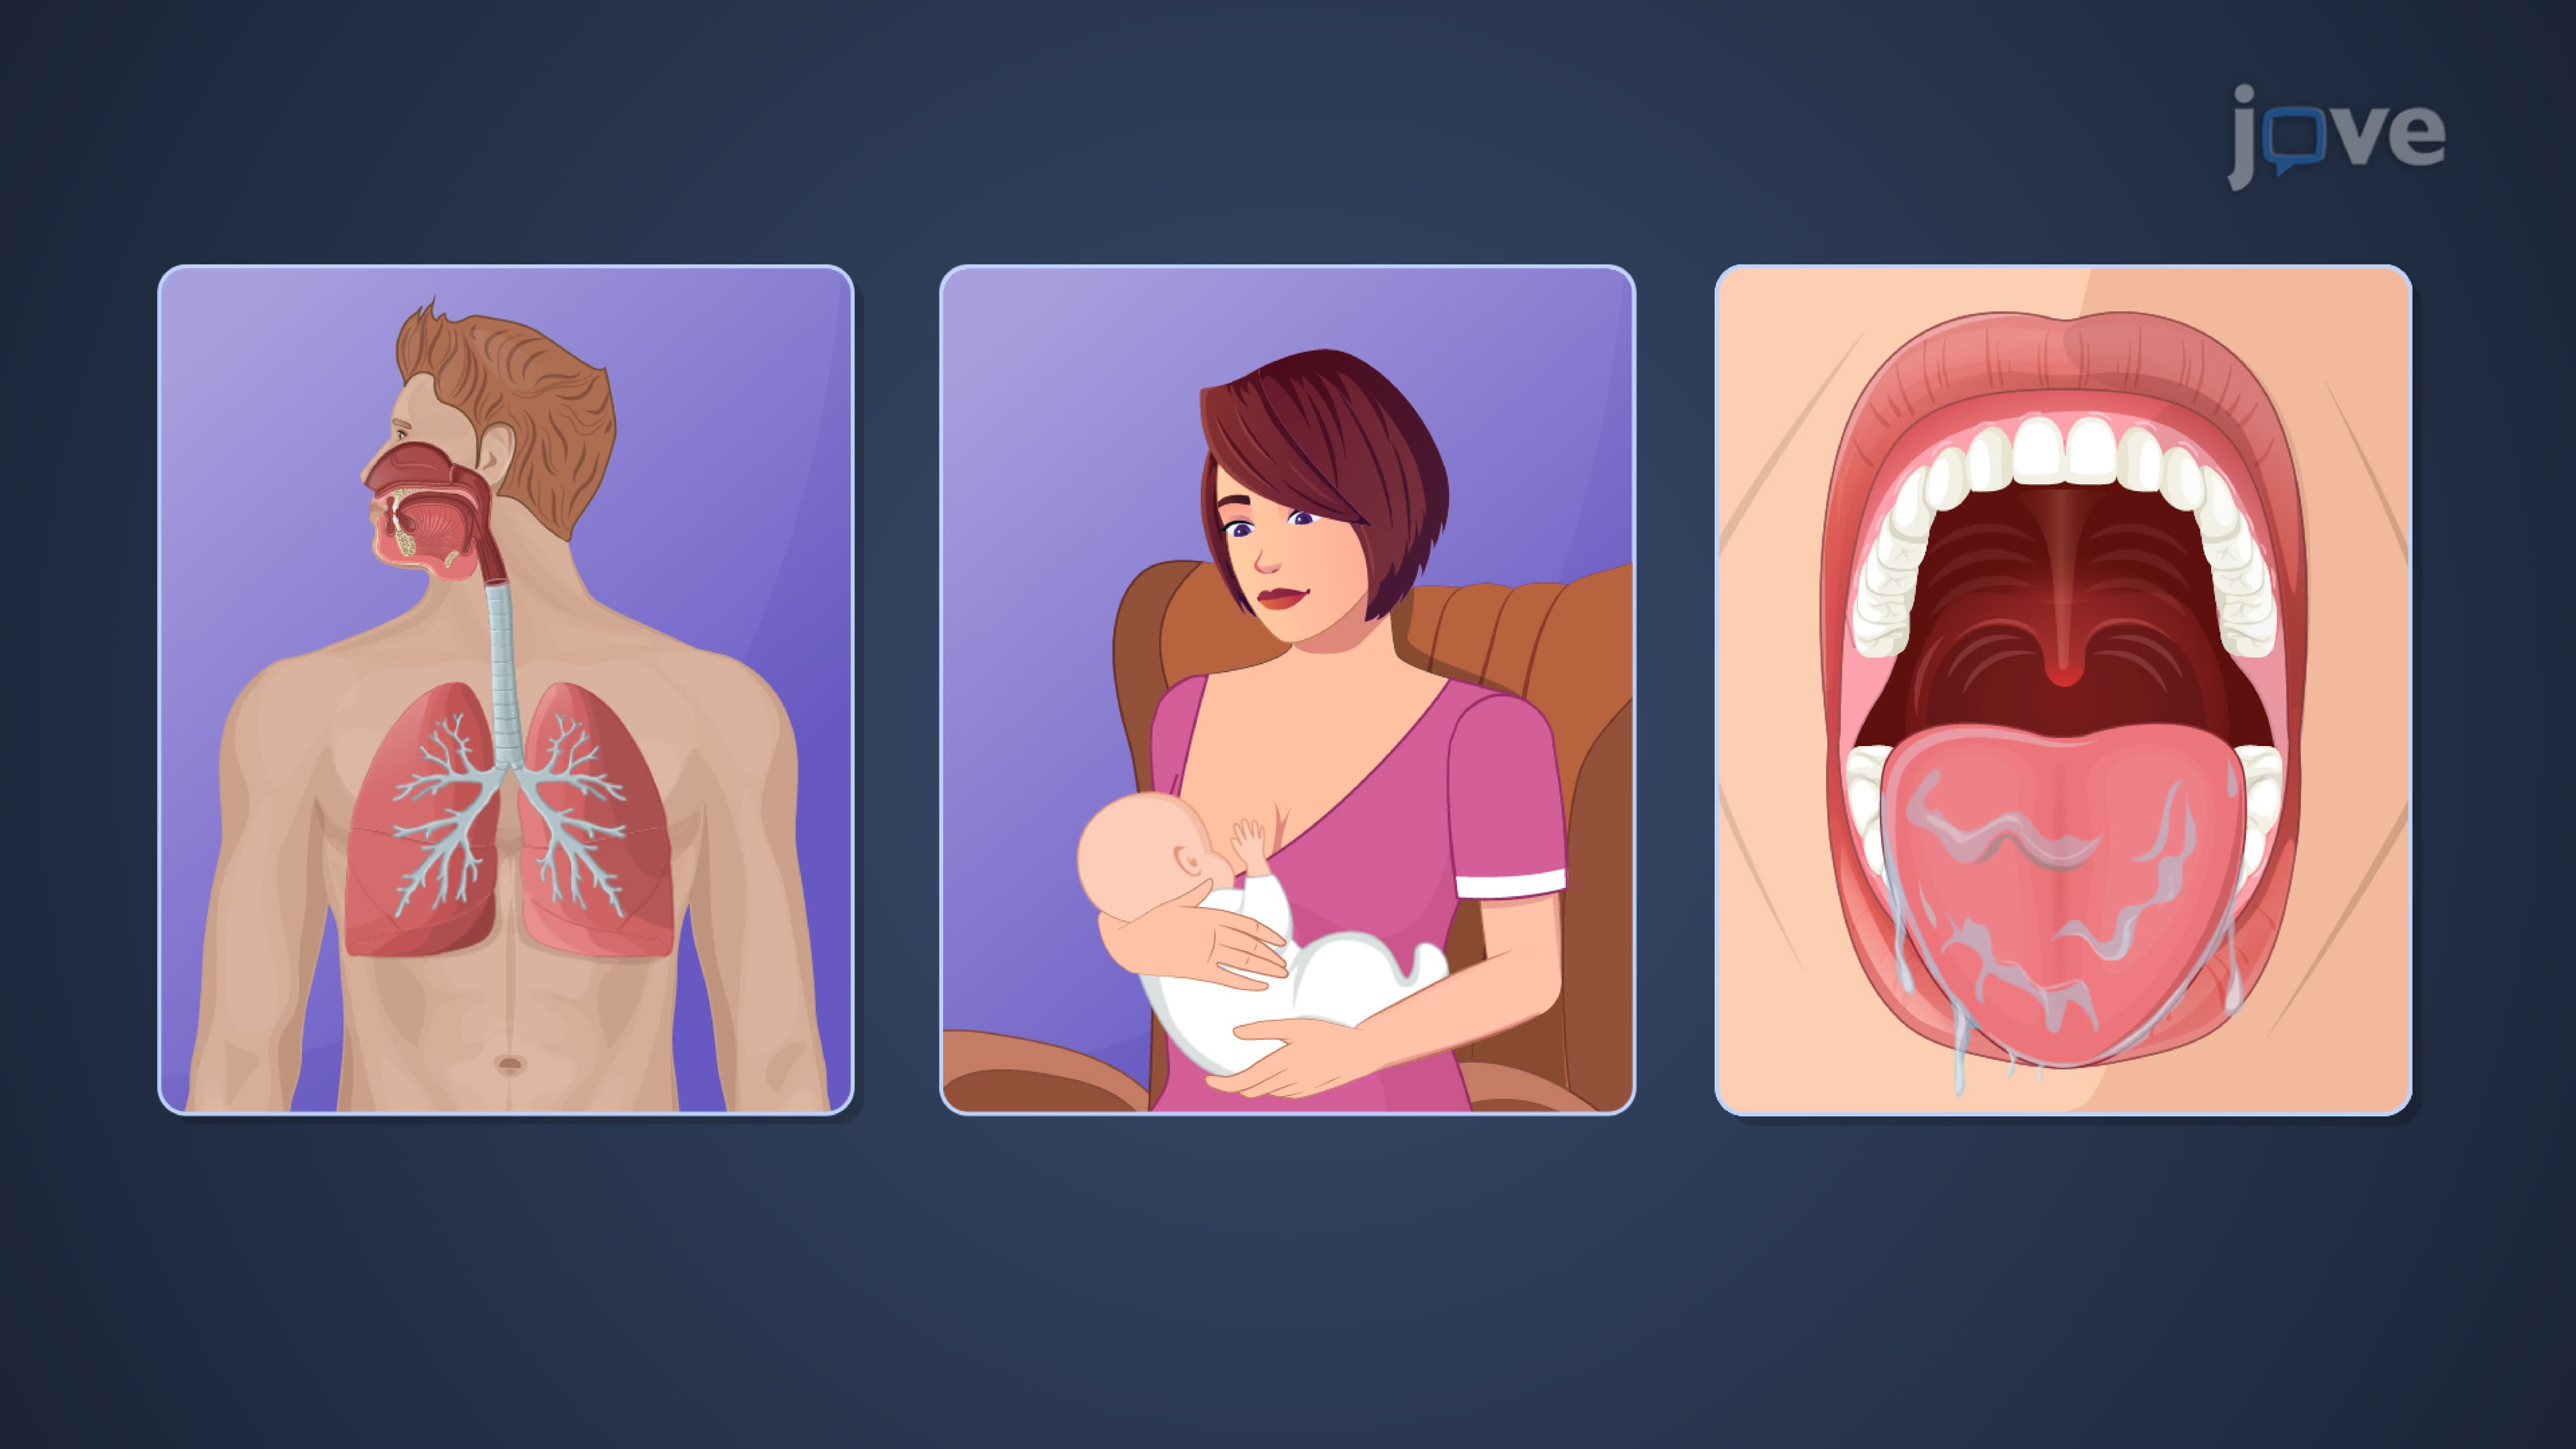
Drug Excretion: Pulmonary and Glandular Routes
Drugs can also be excreted in breast milk, which is crucial for breastfeeding infants. The...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism