Related Experiment Video
Updated: Nov 12, 2025
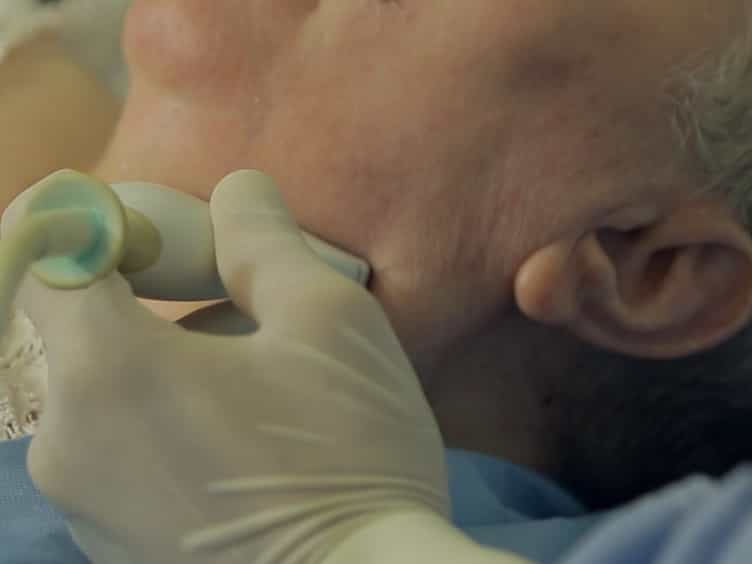

Ultrasound-guided Botulinum Toxin-A Injections: A Method of Treating Sialorrhea
Published on: November 9, 2016
Nabiximols and botulinum toxin injections for patients with multiple sclerosis: efficacy on spasticity and spasms in
Arianna Sartori1, Alessandro Dinoto2, Lara Stragapede2
1Clinical Unit of Neurology, Department of Medicine, Surgery and Health Sciences, Cattinara University Hospital ASUGI, University of Trieste, Strada di Fiume 447, 34149, Trieste, Italy. sartoriarianna23@gmail.com.

Background:
Spasticity is a common and disabling symptom in patients with multiple sclerosis (PwMS): as highlighted by many epidemiological studies, it is often a severe and not well treated. Despite the availability of evidence-based spasticity management guidelines, there is still great variability in everyday therapeutic approach, especially for the most complex cases.
Methods:
In our single-centre study, we retrospectively evaluated PwMS-treated nabiximols and botulinum toxin injections (BTI) from July 2015 to April 2019. Clinical and demographic data were collected. The severity of spasticity and spasms was recorded by modified Ashworth Scale (mAS) and Penn Spasm Frequency Scale (PSFS) at baseline and after 1 month of treatment.
Results:
We evaluated 64 treatments for MS-related spasticity: 28 patients were treated with BTI and 36 patients with nabiximols. We found that both BTI and nabiximols are effective in reducing mAS (nabiximols, BTI: p < 0.001), PSFS frequency (nabiximols: p = 0.001, BTI: p = 0.008) and intensity (nabiximols: p = 0.001, BTI p = 0.016). No differences were found when directly comparing the efficacy of the two treatments, except for a statistical trend favouring BTI on spasms intensity (p = 0.091). Eleven patients were treated with both BTI and nabiximols, and only four patients continued both treatments. All dropouts were due to inefficacy of at least one of the two therapies.
Conclusions:
Our single-centre experience highlights that both BTI and nabiximols are effective in treating multiple sclerosis-related spasticity; however, BTI treatment may be more effective on spasms intensity. Combined nabiximols and BTI treatment could represent a therapeutic option for severe spasticity.
More Related Videos
 07:20
Author Spotlight: Repetitive Transcranial Magnetic Stimulation Combined with Movement Observation in Cerebral Palsy
Published on: August 9, 2024
 08:20
Author Spotlight: Unveiling the Therapeutic Effects of FSN Treatment – Bridging Research and Clinical Applications in Neuropathic Pain
Published on: June 30, 2023
Related Concept Videos
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:24
Centrally Acting Muscle Relaxants: Therapeutic Uses
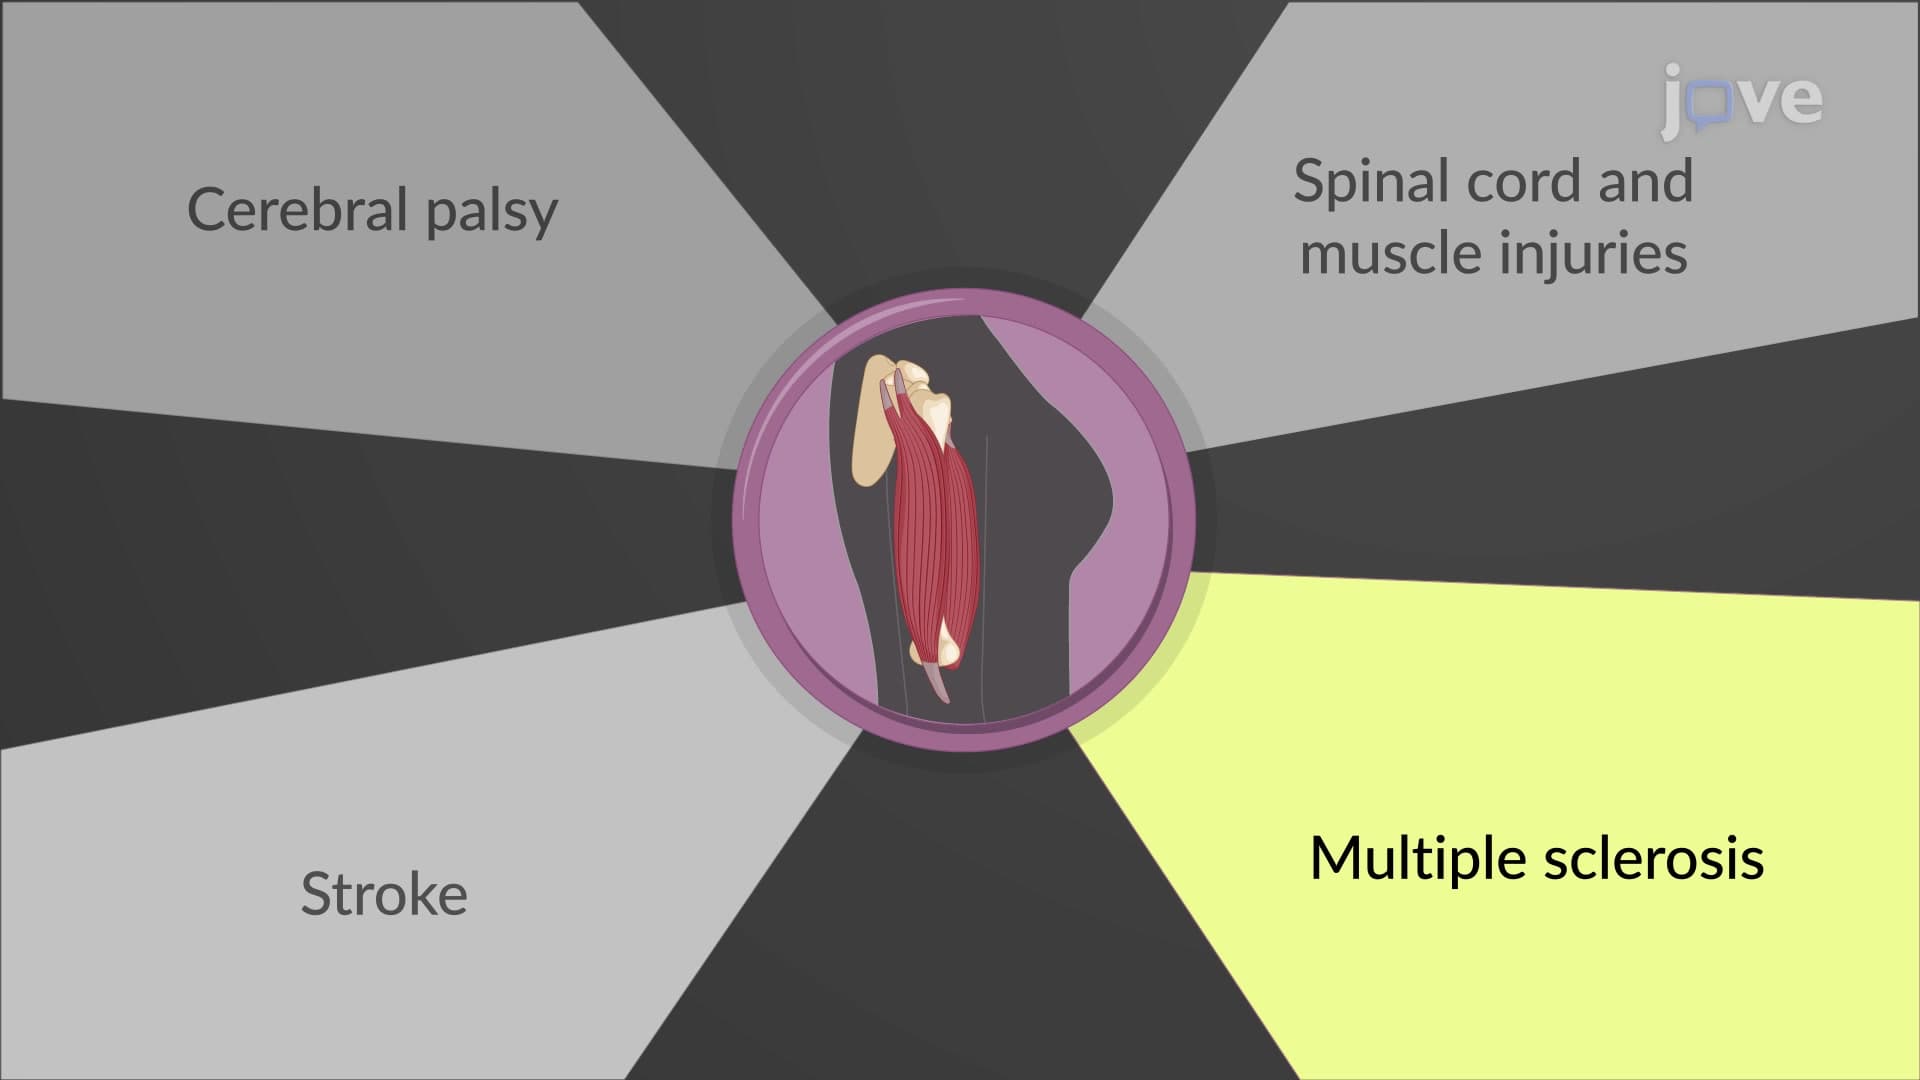
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:29
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also...