Related Experiment Video
Updated: Nov 11, 2025
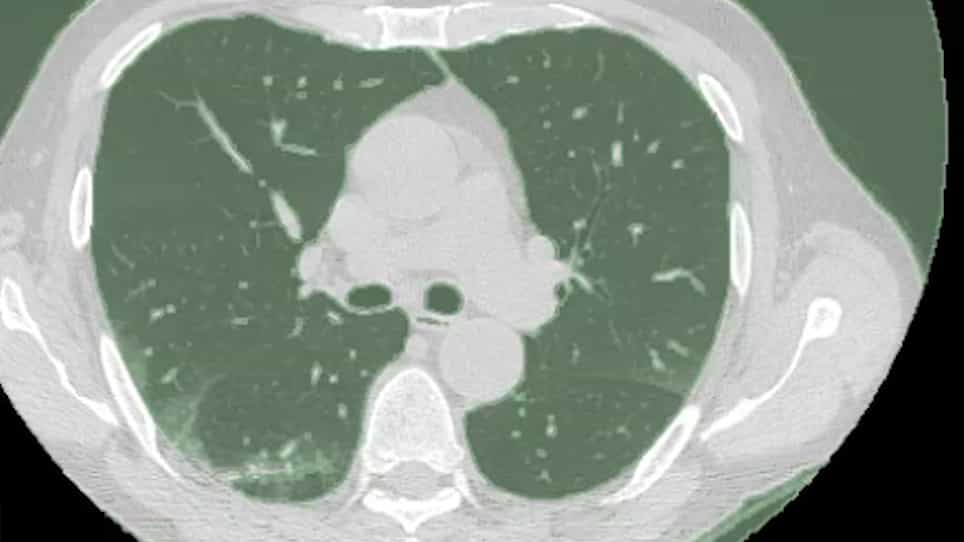

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Progression and Resolution of COVID-19 Pneumonia on Chest Radiograph
Laiba Masood1, Suraya Bano Zafar1, Madiha Saeed Wahla1
1Department of Radiology, Shifa International Hospital, Islamabad, Pakistan.

Objective:
To evaluate the temporal changes on serial chest radiographs (CXRs)of hospitalised COVID-19 positive patients till their outcome(discharge/death); to determine the severity of CXR score and its correlation with clinical outcome (hospital stay, chest intubation and mortality).
Study Design:
Descriptive study.
Place And Duration Of Study:
Shifa International Hospital (SIH), Islamabad from March to June 2020.
Methodology:
After IRB approval, 112 patients were consecutively enrolled, having laboratory-confirmed SARS-CoV-2 and hospitalised in SIH. Patients' demographics and clinical data were retrieved from Radiology Information System (RIS). Chest radiographs (CXR) were retrieved from picture archive and communication system (PACS). CXR severity scoring was determined by three radiologists, and results were analysed.
Results:
Lung opacities (98.2%), involvement of both lungs (96.4%), both peripheral and central region involvement (62.5%) and upper/mid/lower zone distribution (61.6%) were the most frequent findings. Males affected more than females with a mean age of 58.9 ± 13.1 years. Zonal involvement, density and extent of opacities peaked on 10-13th day of illness. In the last CXR, opacities showed decrease in extent as well as density, reduction in zonal involvement, and few having mixed interstitial thickening/fibrosis. One hundred and five out of 112 (93.8%) patients had residual radiographic abnormalities on discharge.
Conclusion:
Serial chest radiography can be used to monitor disease progression and temporal changes after initial HRCT. Patients who have CXR severity score of 4 or more at the time of admission, is a red flag for prolonged hospital stay and possible intubation. Severity of CXR findings peaked at 10-13 days. It is recommended to repeat CXRs every 3-4th day during hospital stay. Majority of the patients has residual radiographic abnormality on discharge. Key Words: COVID-19, Radiography, Thoracic, Pandemic, Chest X-ray.
More Related Videos


Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia III: Complications and Assessment
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:17
Pulmonary Cycle: Exhalation