Related Experiment Video
Updated: Nov 11, 2025


A Porcine Model of Acute Autologous Pulmonary Embolism
Published on: September 6, 2024
Pulmonary Thromboembolism in COVID-19: Venous Thromboembolism or Arterial Thrombosis?
Enrico Cavagna1, Francesco Muratore1, Fabio Ferrari1
1Department of Radiology, Ospedale Infermi, viale Settembrini 2/A, 47900 Rimini, Italy.

Purpose:
To investigate CT pulmonary angiography findings of pulmonary thromboembolism (PTE) in coronavirus disease 2019 (COVID-19) and its association with clinical and radiologic conditions.
Materials And Methods:
This retrospective study includes 109 hospitalized patients with COVID-19 who underwent CT pulmonary angiography for suspected PTE from March 20 to May 3, 2020. Data were collected from our PACS. CT pulmonary angiography findings of PTE were evaluated. On the basis of the presence or absence of PTE, patients were divided into two groups, and their clinical and radiologic conditions were compared using the Mann-Whitney U test and χ2 test.
Results:
The study population comprised 82 men and 19 women, with a mean age of 64.1 years ± 15.0 (95% confidence interval [CI]: 60.4, 67.6) years. CT pulmonary angiography was performed 19.8 days ± 6.1 (95% CI: 18.1, 20.2) after symptom onset and 10.5 days ± 3.8 (95% CI: 10.2, 12.9) after admission. Of 101 patients, 41 had PTE (40.6%). PTE was mostly bilateral or only right (37/41 [90.2%]), mainly involved segmental (37/41 [90.2%]) or subsegmental (25/41 [61.0%]) arteries and affected mainly the branches of the lower lobe (30/41 [73.2%]). Parenchymal segments supplied by segmental arteries with PTE showed a prevalent consolidation pattern (25/37 [67.6%]). Deep vein thrombosis was present only in five of 41 (12.2%) patients. Comparing groups with and without PTE, no significant difference was observed in age, sex, symptom onset, comorbidities, tumor history, use of respiratory supports, activated partial thromboplastin time, prothrombin time, and deep vein thrombosis. Conversely, differences were evaluated in CT lesion score (15.7 ± 1.4 [95% CI: 15.3, 16.1] vs 14.1 ± 1.1 [95% CI: 13.8, 14.4]; P = .035), d-dimer level (P < .001), lactate dehydrogenase level (P < .001), and C-reactive protein level (P = .042).
Conclusion:
PTE in COVID-19 involves mainly the segmental and subsegmental arteries of segments affected by consolidations in patients with more severe lung disease. The authors hypothesize that the development of PTE in COVID-19 might be a pulmonary artery thrombosis because of severe lung inflammation and hypercoagulability rather than thromboembolism.© RSNA, 2020.
More Related Videos
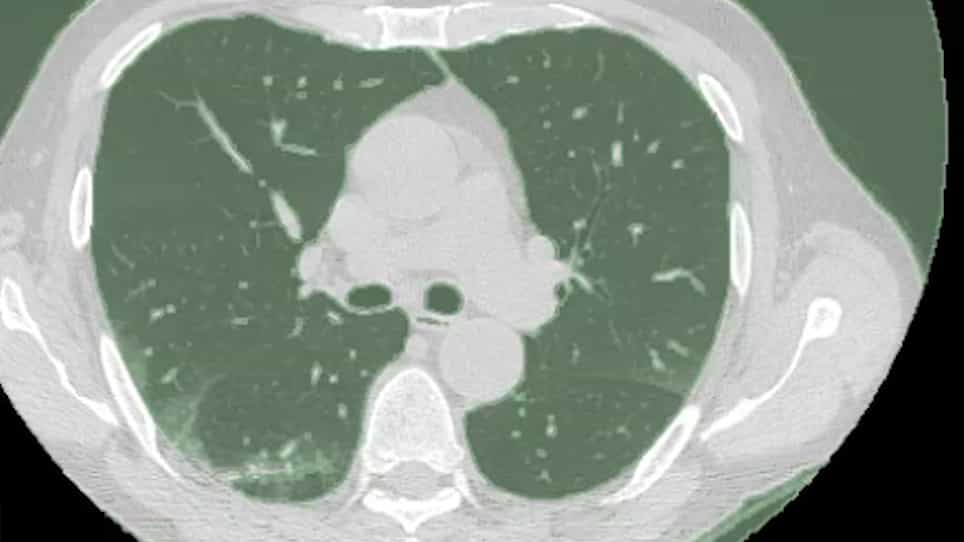 08:05
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
 09:19
In Vitro Microfluidic Disease Model to Study Whole Blood-Endothelial Interactions and Blood Clot Dynamics in Real-Time
Published on: May 24, 2020
Related Concept Videos
 01:29
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:30
Venous Thrombosis I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...