Related Experiment Video
Updated: Nov 11, 2025
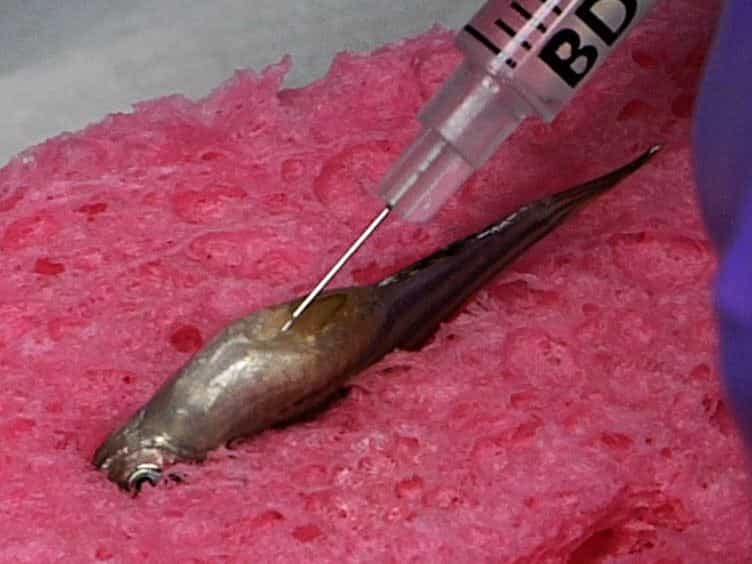
Analysis of Nephron Composition and Function in the Adult Zebrafish Kidney
Published on: August 9, 2014
Hepatorenal syndrome: a historical appraisal of its origins and conceptual evolution
Garabed Eknoyan1, Murray Epstein2
1The Selzman Institute of Kidney Health, Section of Nephrology, Department of Medicine, Baylor College of Medicine, Houston, Texas, USA.

Abstract:
The hepatorenal syndrome (HRS), a progressive but potentially reversible deterioration of kidney function, constitutes a serious complication of hepatic decompensation. Coexistence of liver/kidney damage, mentioned in the dropsy literature, was highlighted by Richard Bright in 1827 and confirmed in 1840 by his contemporary nephrology pioneer Pierre Rayer. Cholemic nephrosis was described in 1861 by Friedrich Frerichs, and the renal tubular lesions of HRS by Austin Flint in 1863. The term "acute hepato-nephritis" was introduced in 1916 by Paul Merklen, and its chronic form was designated HRS by Marcel Dérot in 1930s. HRS then was applied to renal failure in biliary tract surgery and to cases of coexistent renal and hepatic failure of diverse etiology. The pathogenesis of HRS was elucidated during the 1950 studies of renal physiology. Notably, studies of salt retention in edema and its relation to regulating the circulating plasma volume by John Peters and subsequently Otto Gauer defined the concept of "effective blood volume" and the consequent elucidation of ascites formation in liver failure. Parallel studies of intrarenal hemodynamics demonstrated severe renal vasoconstriction and preferential cortical ischemia to account for the functional renal dysfunction of HRS. Dialysis and liver or combined liver-kidney transplantation transformed the fatal HRS of old into a treatable disorder by the 1970s. Elucidation of the pathogenetic mechanisms of renal injury and refinements in definition, classification, and diagnosis of HRS since then have allowed for earlier therapeutic intervention with combined i.v. albumin and vasoconstrictor therapy, enabling the continued improvement of patient outcomes.

Related Concept Videos
 01:29
Acute Kidney Injury II: Pathophysiology
 01:22
Acute Kidney Injury I: Introduction
 01:24
Nephrotic Syndrome I : Introduction
 01:29
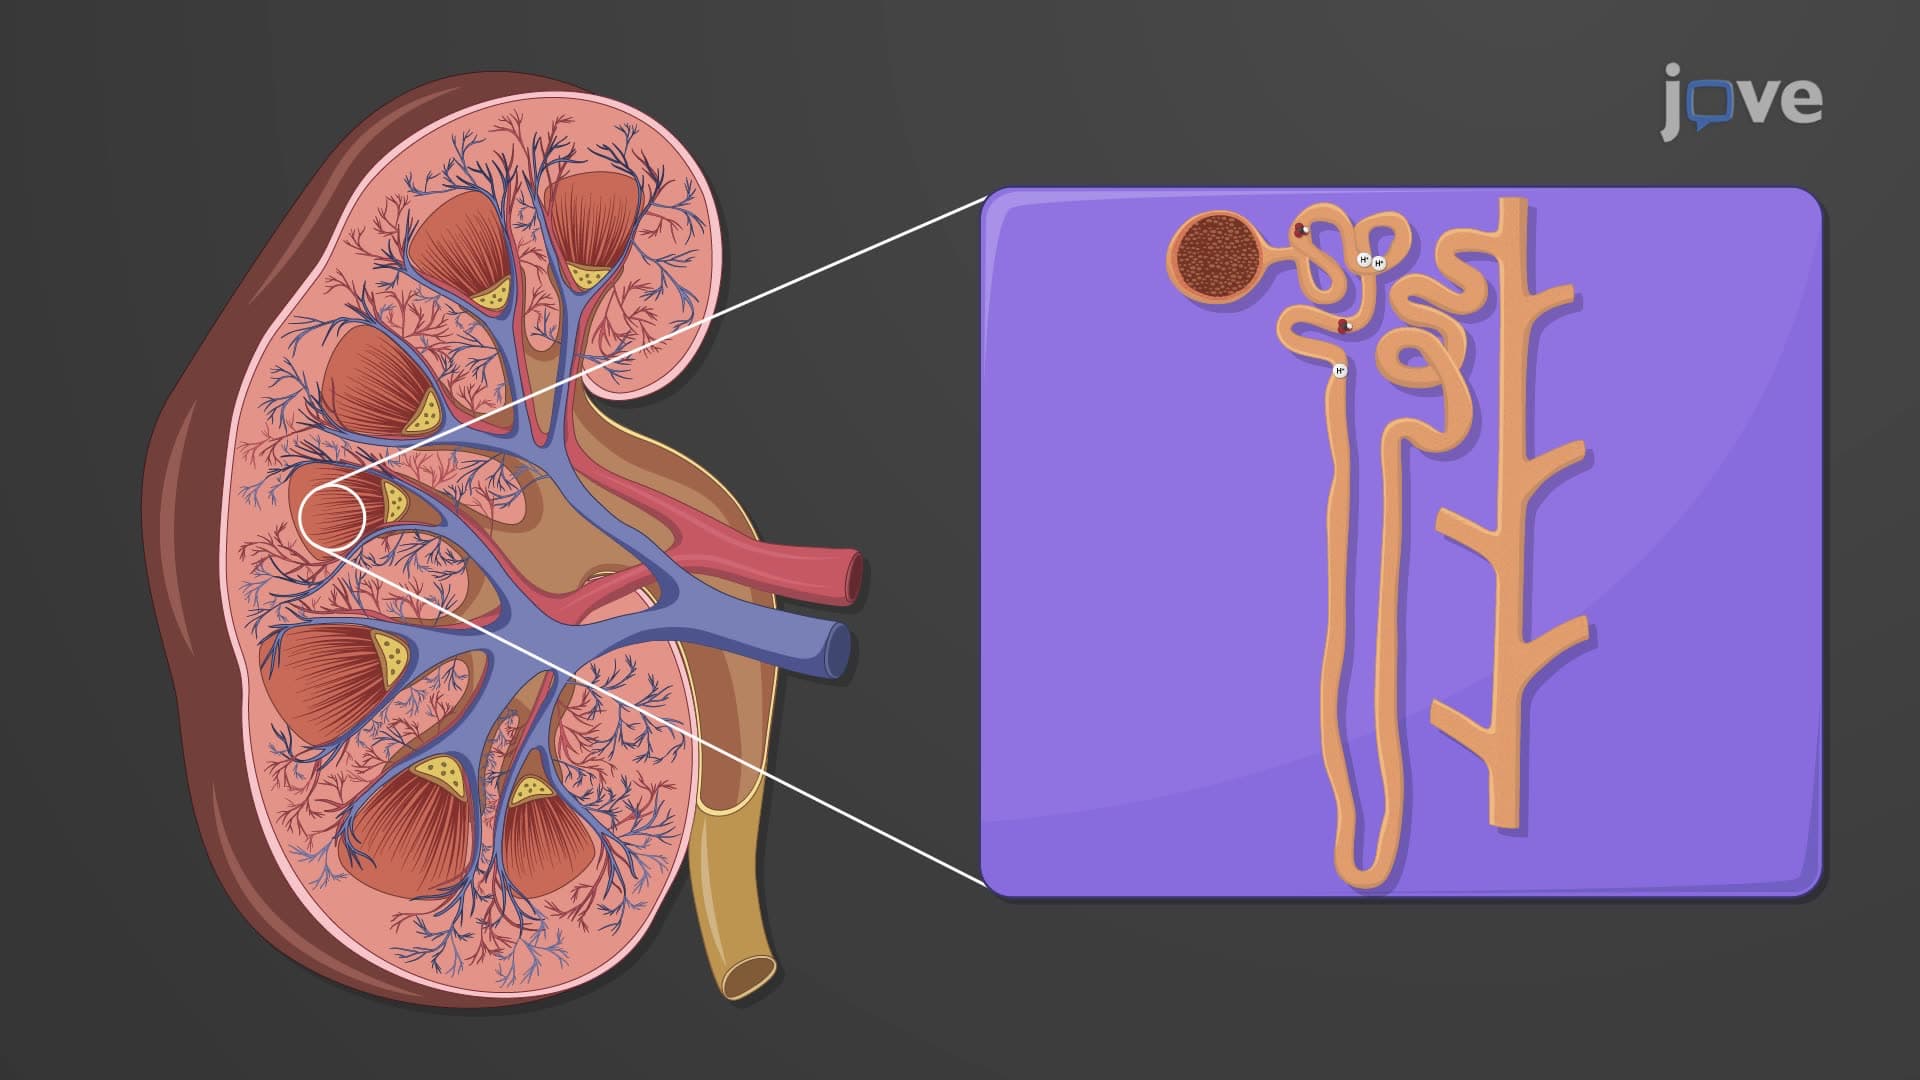
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention