Related Experiment Video
Updated: Nov 10, 2025
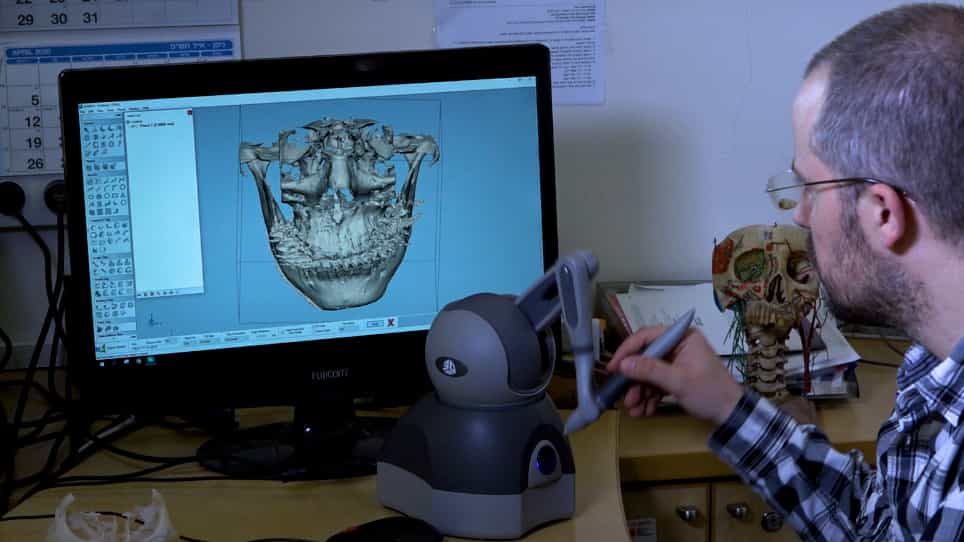
Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Ultra-early synostectomy and cranial remodeling orthoses in the management of craniosynostoses
Aaron Mohanty1, Thomas S Frank1, Sharif Mohamed2
1Departments of1Neurosurgery and.

Insights
Ultra-early endoscopic synostectomy (surgery at 8 weeks or younger) is safe for infants with craniosynostosis. This approach offers a safe alternative to traditional timing, with comparable complication rates.
Area of Science:
- Neurosurgery
- Pediatric Surgery
- Craniofacial Surgery
Background:
- Craniosynostosis diagnosis often occurs at birth.
- Endoscopic synostectomy is typically delayed until 3 months of age.
- Limited data exists on early neonatal endoscopic synostectomy.
Purpose of the Study:
- To evaluate the safety and efficacy of ultra-early endoscopic synostectomy.
- To define ultra-early endoscopic synostectomy as surgery for infants 8 weeks or younger.
- To compare outcomes with traditional surgical timing.
Main Methods:
- Retrospective analysis of 25 infants undergoing surgery at or before 8 weeks of age (2011-2020).
- Data collected on infant age, weight, synostosis type, operative time, blood loss, complications, and reoperations.
- Follow-up ranged from 6 months to 8 years.
Main Results:
- Twenty-five infants underwent ultra-early synostectomy (11 ≤2 weeks, 8 aged 3-4 weeks, 6 aged 5-8 weeks).
- Average operative time was 35 minutes; blood loss was ≤25 ml in 19 cases.
- Complications included durotomy, skin infection, and kernicterus; 3 infants required reoperation, primarily for syndromic craniosynostosis.
Conclusions:
- Ultra-early endoscopic synostectomy is safe and does not increase complications compared to surgery at 3-6 months.
- Multisuture synostosis is associated with longer operative times, higher transfusion rates, and increased likelihood of reoperation.
- Infants with syndromic craniosynostosis may require repeat surgery for cranial volume and cosmesis.
Objective:
The advent of endoscopic synostectomy has enabled early surgery for infants with craniosynostosis. Even though diagnosis is often made at birth, endoscopic synostectomy has traditionally been delayed until the infant is 3 months of age. There have been very few published reports of this procedure being performed in the early neonatal period. The authors discuss their experience with ultra-early endoscopic synostectomy, defined as an operation for infants aged 8 weeks or younger.
Methods:
A retrospective analysis of infants who underwent operations at or before 8 weeks of age between 2011 and 2020 was done.
Results:
Twenty-five infants underwent operations: 11 were 2 weeks of age or younger, 8 were between 3 and 4 weeks of age, and 6 were between 5 and 8 weeks of age. The infants weighed between 2.25 and 4.8 kg. Eighteen had single-suture synostosis, and 7 had multiple sutures involved. Of these 7, 4 had syndromic craniosynostosis. The average operative time was 35 minutes, and it was less than 40 minutes in 19 cases. The estimated operative blood loss was 25 ml or less in 19 cases; 5 infants required an intraoperative blood transfusion. In 1 child with syndromic multisuture craniosynostosis, the surgery was staged due to blood loss. Two children experienced complications related to the procedure: one had an incidental durotomy with skin infection, and the other had postoperative kernicterus. All infants were fitted for cranial remodeling orthoses following surgery. Three of the 25 infants required reoperations, with 2 patients with syndromic craniosynostosis needing repeat surgery for cranial volume expansion and cosmetic appearance. Another child with syndromic craniosynostosis is awaiting cranial expansion surgery. Follow-up varied between 6 months and 8 years.
Conclusions:
The data show that ultra-early synostectomy is safe and not associated with increased complications compared with surgery performed between 3 and 6 months of age. Infants with multisuture synostosis had increased operative time, required blood transfusion, and were more likely to require a second operation.

Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...