Related Experiment Video
Updated: Nov 10, 2025
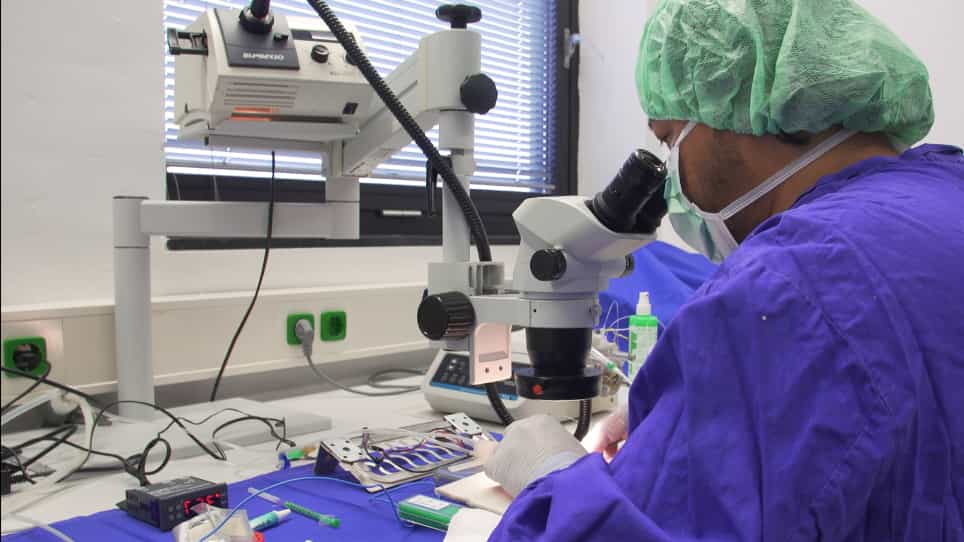

Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
Factor XIII Activity Might Already Be Impaired before Veno-Venous ECMO in ARDS Patients: A Prospective, Observational
Onnen Moerer1, Jan Felix Huber-Petersen1, Joern Schaeper1
1Department of Anesthesiology, University Medical Center Goettingen, 37075 Goettingen, Germany.

Direct complications in patients receiving extracorporeal (veno-venous) membrane oxygenation (vvECMO) are mainly either due to bleeding or thromboembolism. We aimed to evaluate the course of routine coagulation parameters and the activity of different coagulation factors-with special focus on factor XIII (F XIII)-before, during and after vvECMO in acute respiratory distress syndrome (ARDS) patients. The activity of coagulation factors and rotational thrombelastometry were analyzed in 20 ECMO patients before (T-1) and 6 h (T0), one (T1), three (T3) and seven days (T7) after the implantation, as well as one and three days after the termination of ECMO. F XIII activity was already severely decreased to 37% (30/49) before ECMO. F XIII activity was the only coagulation factor continuously declining during vvECMO, being significantly decreased at T3 (31% (26/45) vs. 24% (18/42), p = 0.0079) and T7 (31% (26/45) vs. 23% (17/37), p = 0.0037) compared to T0. Three days after termination of vvECMO, platelet count and fibrinogen nearly doubled and factors II, V, XI and XIII showed spontaneous significant increases. Severe ARDS patients showed a considerably diminished factor XIII activity before vvECMO initiation and its activity continuously declined later on. Thus, incorporation of F XIII monitoring into the regular hemostaseologic routine during vvECMO therapy seems advisable. Due to the potential development of a hypercoagulatory state after the termination of vvECMO, tight hemostasiologic monitoring should persist in the initial phase after ECMO termination.
Direct complications in patients receiving extracorporeal (veno-venous) membrane oxygenation (vvECMO) are mainly either due to bleeding or thromboembolism. We aimed to evaluate the course of routine coagulation parameters and the activity of different coagulation factors-with special focus on factor XIII (F XIII)-before, during and after vvECMO in acute respiratory distress syndrome (ARDS) patients. The activity of coagulation factors and rotational thrombelastometry were analyzed in 20 ECMO patients before (T-1) and 6 h (T0), one (T1), three (T3) and seven days (T7) after the implantation, as well as one and three days after the termination of ECMO. F XIII activity was already severely decreased to 37% (30/49) before ECMO. F XIII activity was the only coagulation factor continuously declining during vvECMO, being significantly decreased at T3 (31% (26/45) vs. 24% (18/42), p = 0.0079) and T7 (31% (26/45) vs. 23% (17/37), p = 0.0037) compared to T0. Three days after termination of vvECMO, platelet count and fibrinogen nearly doubled and factors II, V, XI and XIII showed spontaneous significant increases. Severe ARDS patients showed a considerably diminished factor XIII activity before vvECMO initiation and its activity continuously declined later on. Thus, incorporation of F XIII monitoring into the regular hemostaseologic routine during vvECMO therapy seems advisable. Due to the potential development of a hypercoagulatory state after the termination of vvECMO, tight hemostasiologic monitoring should persist in the initial phase after ECMO termination.
More Related Videos


Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:29
Pulmonary Embolism I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:30
Acute Respiratory Failure-III