Related Experiment Video
Updated: Nov 9, 2025
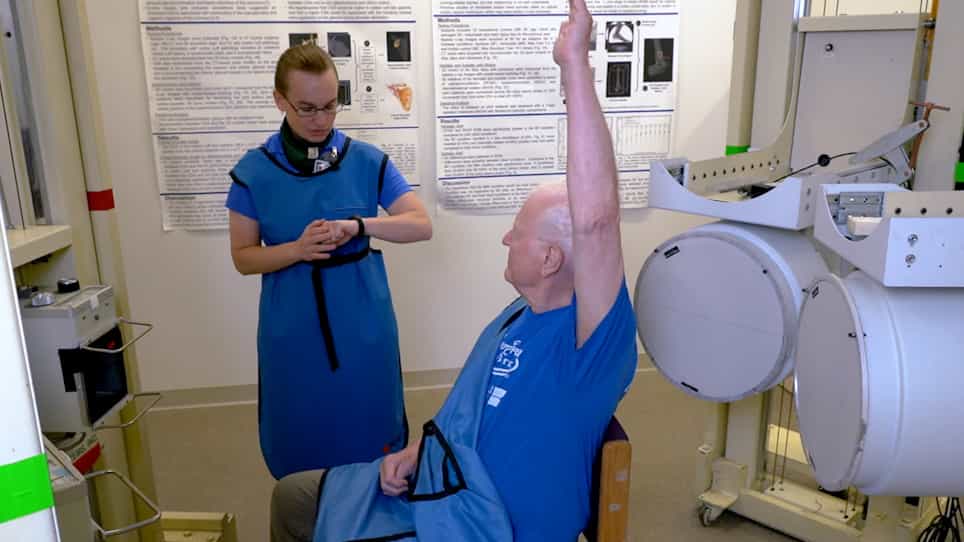

Measuring 3D In-vivo Shoulder Kinematics using Biplanar Videoradiography
Published on: March 12, 2021
Relationship Between Glenoid Component Shift and Osteolysis After Anatomic Total Shoulder Arthroplasty:
Eric T Ricchetti1, Bong-Jae Jun, Yuxuan Jin
1Department of Orthopaedic Surgery, Orthopedic and Rheumatologic Institute (E.T.R., J.C.H., T.E.P., and J.P.I.), Department of Biomedical Engineering, Lerner Research Institute (B.-J.J. and K.A.D.), and Department of Quantitative Health Sciences (Y.J. and J.E.D.), Cleveland Clinic, Cleveland, Ohio.

Background:
The purpose of this study was to evaluate glenoid component position and radiolucency following anatomic total shoulder arthroplasty (TSA) using sequential 3-dimensional computed tomography (3D CT) analysis.
Methods:
In a series of 152 patients (42 Walch A1, 16 A2, 7 B1, 49 B2, 29 B3, 3 C1, 3 C2, and 3 D glenoids) undergoing anatomic TSA with a polyethylene glenoid component, sequential 3D CT analysis was performed preoperatively (CT1), early postoperatively (CT2), and at a minimum 2-year follow-up (CT3). Glenoid component shift was defined as a change in component version or inclination of ≥3° from CT2 to CT3. Glenoid component central anchor peg osteolysis (CPO) was assessed at CT3. Factors associated with glenoid component shift and CPO were evaluated.
Results:
Glenoid component shift occurred from CT2 to CT3 in 78 (51%) of the 152 patients. CPO was seen at CT3 in 19 (13%) of the 152 patients, including 15 (19%) of the 78 with component shift. Walch B2 glenoids with a standard component and glenoids with higher preoperative retroversion were associated with a higher rate of shift, but not of CPO. B3 glenoids with an augmented component and glenoids with greater preoperative joint-line medialization were associated with CPO, but not with shift. More glenoid component joint-line medialization from CT2 to CT3 was associated with higher rates of shift and CPO. A greater absolute change in glenoid component inclination from CT2 to CT3 and a combined absolute glenoid component version and inclination change from CT2 to CT3 were associated with CPO. Neither glenoid component shift nor CPO was associated with worse clinical outcomes.
Conclusions:
Postoperative 3D CT analysis demonstrated that glenoid component shift commonly occurs following anatomic TSA, with increased inclination the most common direction. Most (81%) of the patients with glenoid component shift did not develop CPO. Longer follow-up is needed to determine the relationships of glenoid component shift and CPO with loosening over time.
Level Of Evidence:
Therapeutic Level IV. See Instructions for Authors for a complete description of levels of evidence.

