Related Experiment Video
Updated: Nov 9, 2025
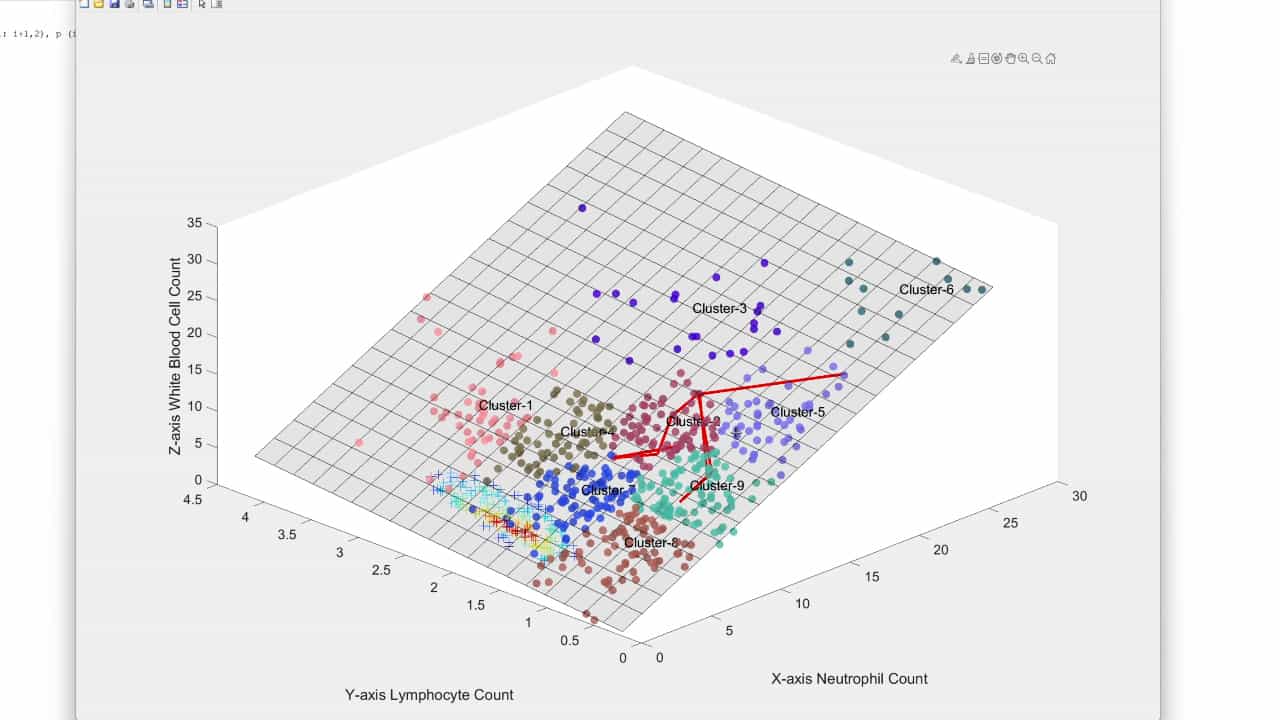
A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Clinical implications of procalcitonin in Kawasaki disease: a useful candidate for differentiating from sepsis and
Man Man Niu1, Qi Jiang1, Jin Wei Ruan1
1Department of Pediatrics, The First Affiliated Hospital of Anhui Medical University, Hefei, Anhui, 230022, People's Republic of China.

Objective:
Kawasaki disease (KD) is an acute systemic vasculitis and suspected to be triggered by several potential infections in which procalcitonin (PCT) experiences an increase to some extent. However, whether PCT can serve as a useful candidate for differentiating KD from sepsis, and even for predicting incomplete KD, intravenous immunoglobulin (IVIG) nonresponsiveness and coronary artery abnormalities (CAAs) remains unclear.
Methods:
A total of 254 Chinese KD children were enrolled and divided into 6 subgroups, including complete KD, incomplete KD, IVIG-responsive KD, IVIG-nonresponsive KD, KD with CAAs and KD without CAAs. Blood samples were collected from all subjects within 24-h pre- and 48-h post-IVIG infusion, respectively. PCT, C-reactive protein, erythrocyte sedimentation rate and blood cell counts were detected. In addition, both 261 children with sepsis and 251 healthy children sex- and age-matched with KD children were enrolled in the same period.
Results:
(1) PCT experienced the highest increase in sepsis patients before antibiotic therapy, followed by acute KD patients and the healthy controls. (2) The proportion of KD patients with a PCT concentration below 0.25 ng/ml was 11 folds higher than that of sepsis patients. (3) PCT had a sensitivity of 91.7% and a specificity of 30.3% at a cutoff value of > 0.15 ng/ml to predict IVIG nonresponsiveness, and the proportion of IVIG-nonresponders with a PCT concentration of 0.25-0.50 ng/ml was 2 folds higher than that of IVIG-responders.
Conclusions:
The PCT concentrations below 0.25 ng/ml may be useful for discriminating KD from sepsis, and moreover, the PCT concentrations of 0.25-0.50 ng/ml may be helpful in predicting IVIG nonresponsiveness.

Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:19
Pericarditis II: Clinical Features and Diagnostic Tests
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:30
Pneumonia III: Complications and Assessment
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:22
Acute Kidney Injury I: Introduction