Related Experiment Video
Updated: Nov 9, 2025


Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Impact of hospital volume on resource use after elective cardiac surgery: A contemporary analysis
Joseph Hadaya1, Yas Sanaiha1, Roland Hernandez2
1Cardiovascular Outcomes Research Laboratories, Division of Cardiac Surgery, Department of Surgery, University of California, Los Angeles, Los Angeles, CA.

Insights
High-volume hospitals reduce costs and mortality for cardiac surgery. Greater surgical volume leads to better outcomes, including fewer readmissions and non-home discharges, guiding value-based care.
Area of Science:
- Cardiovascular Surgery
- Health Services Research
- Healthcare Economics
Background:
- Institutional experience is linked to better outcomes in major cardiac surgeries.
- Previous studies suggest hospital volume impacts patient results.
Purpose of the Study:
- To evaluate the effect of hospital volume on hospitalization costs and post-discharge resource use in elective cardiac operations.
- To compare outcomes between low-volume and high-volume cardiac surgery centers.
Main Methods:
- Analysis of a national cohort (2016-2017 Nationwide Readmissions Database) of adult patients undergoing elective coronary artery bypass grafting or valve operations.
- Institutions categorized into volume quartiles; comparisons focused on the lowest and highest quartiles using generalized linear models.
Main Results:
- High-volume hospitals (25.2% of cases) had patients who were younger and had more comorbidities than low-volume hospitals (24.8% of cases).
- Operations at high-volume hospitals were associated with $7,600 lower costs and reduced odds of mortality, non-home discharge, and 30-day readmission.
Conclusions:
- Increased operative volume at hospitals is independently associated with lower hospitalization costs and mortality for elective cardiac surgery.
- The benefits extend beyond acute care, with reduced non-home discharge and readmissions, supporting value-based care models.
Background:
Institutional experience has been associated with reduced mortality after coronary artery bypass grafting and valve operations. Using a contemporary, national cohort, we examined the impact of hospital volume on hospitalization costs and postdischarge resource utilization after these operations.
Methods:
Adults undergoing elective coronary artery bypass grafting or valve operations were identified in the 2016 to 2017 Nationwide Readmissions Database. Institutions were grouped into volume quartiles based on annual elective cardiac surgery caseload, and comparisons were made between the lowest and highest quartiles, using generalized linear models.
Results:
Of an estimated 296,510 patients, 24.8% were treated at low-volume hospitals and 25.2% at high-volume hospitals. Compared with patients treated at low-volume hospitals, patients managed at high-volume hospitals were younger, had more comorbidities, and more frequently underwent combined coronary artery bypass grafting valve (13.0% vs 12.3%, P < .001) and multivalve operations (6.2% vs 3.1%, P < .001). After adjustment, operations at high-volume hospitals were associated with a $7,600 reduction (95% confidence interval $4,700-$10,500) in costs. High-volume hospitals were also associated with reduced odds of mortality, non-home discharge, and 30-day non-elective readmission compared to low-volume hospitals.
Conclusion:
Despite increased complexity at high-volume centers, greater operative volume was independently associated with reduced hospitalization costs and mortality after elective cardiac operations. Reduction in non-home discharge and readmissions suggests this effect to extend beyond acute hospitalization, which may guide value-based care paradigms.
More Related Videos


Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:19
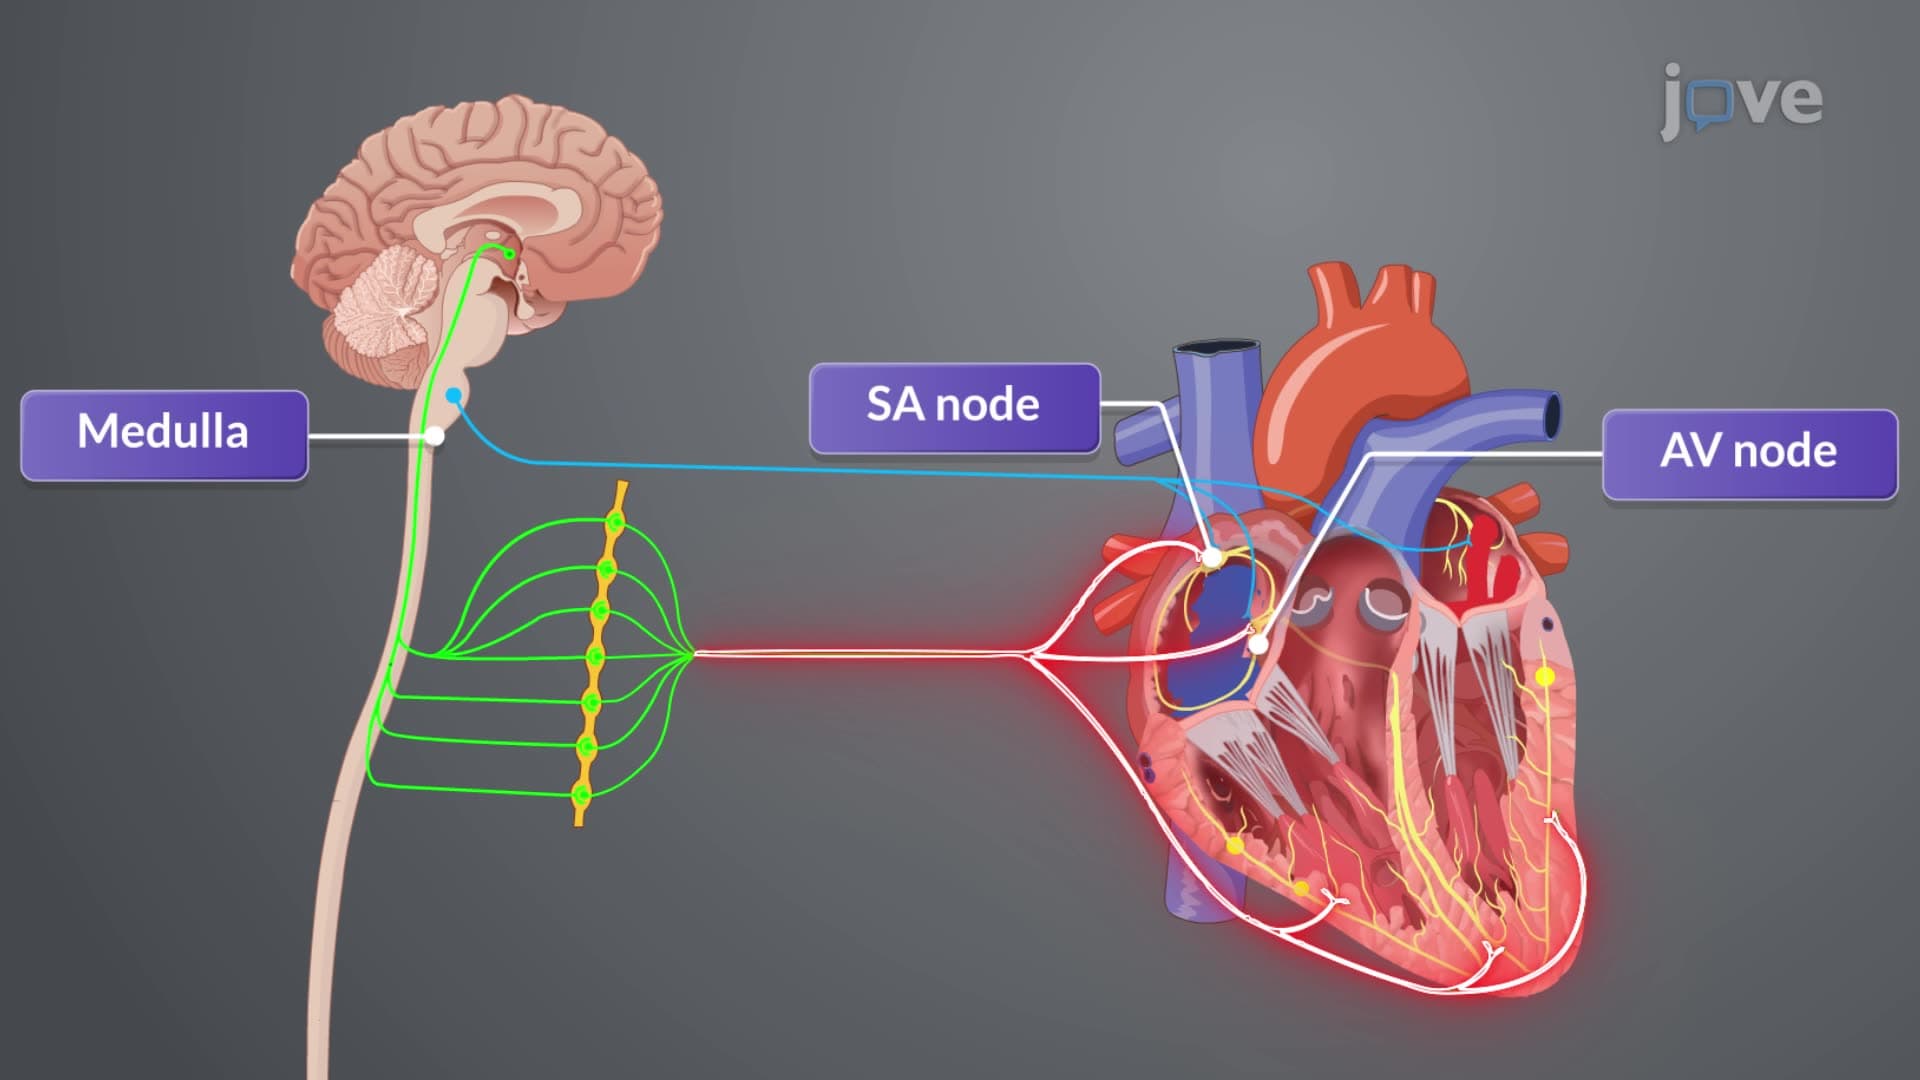
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...