Related Experiment Video
Updated: Nov 9, 2025
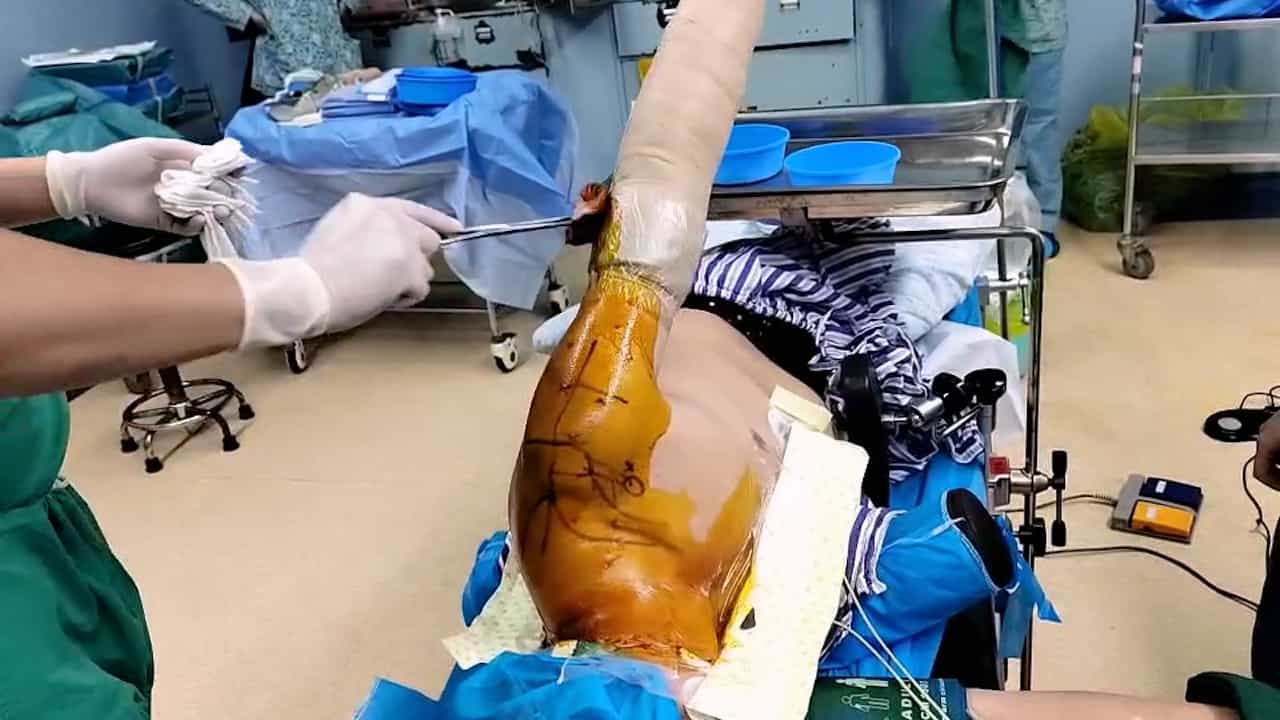

Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025
Modified Superior Capsule Reconstruction Using the Long Head of the Biceps Tendon as Reinforcement to Rotator Cuff
Chen-Hao Chiang1, Leo Shaw2, Wei-Hsing Chih3
1Department of Biomedical Engineering, National Cheng Kung University, Tainan, Taiwan; Department of Orthopaedics, Ditmanson Medical Foundation Chia-Yi Christian Hospital, Chiayi, Taiwan.

Purpose:
To retrospectively assess the clinical outcomes of the patients with large to massive reparable RCTs treated by arthroscopic rotator cuff repair (ARCR) combined with modified superior capsule reconstruction (mSCR) using the long head of biceps tendon (LHBT) as reinforcement with a minimum of 2 years of follow-up.
Methods:
We retrospectively evaluated 40 patients with large to massive reparable RCTs who underwent ARCR and mSCR (group I) between February 2017 and June 2018 (18 patients) or underwent ARCR and tenotomy of LHBT performed at the insertion site (group II) between January 2015 and January 2017 (22 patients). The pain visual analog score (VAS) was assessed preoperatively and 1, 3, 6, 12, 24 months postoperatively. American Shoulder and Elbow Surgeons (ASES) scores, the University of California, Los Angeles (UCLA) shoulder rating scale, and active range of motion (AROM) were assessed before surgery and 6, 12, and 24 months after surgery. The integrity of the rotator cuff and mSCR was evaluated using magnetic resonance images at 12 months postoperatively.
Results:
After surgery, both groups had significantly improved in VAS, ASES, UCLA and AROM scores in the final follow-up. There were no significant between-group differences in the characteristics of the patients before surgery. Group I had improved pain relief at 1 month (P < .001) and at 3 months (P < .01) after surgery. For the AROM, group I (flexion, external rotation, internal rotation) demonstrated better improvement than group II 6 months after surgery (all P < .05) and better internal rotation 12 and 24 months after surgery (all P < .05). The mSCR survival rate was 94.4% (17/18). The retear rate of repaired rotator cuffs for groups I and II was 16.7% (3/18) and 40.9% (9/22), respectively, and the differences were significant (P < .046).
Conclusions:
ARCR combined with mSCR using LHBT as reinforcement may lead to a lower retear rate and earlier functional recovery than conventional ARCR with tenotomy of LHBT for large to massive reparable RCTs.
Level Of Evidence:
Level III, retrospective therapeutic comparative trial.

Related Concept Videos
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...