Related Experiment Video
Updated: Nov 8, 2025
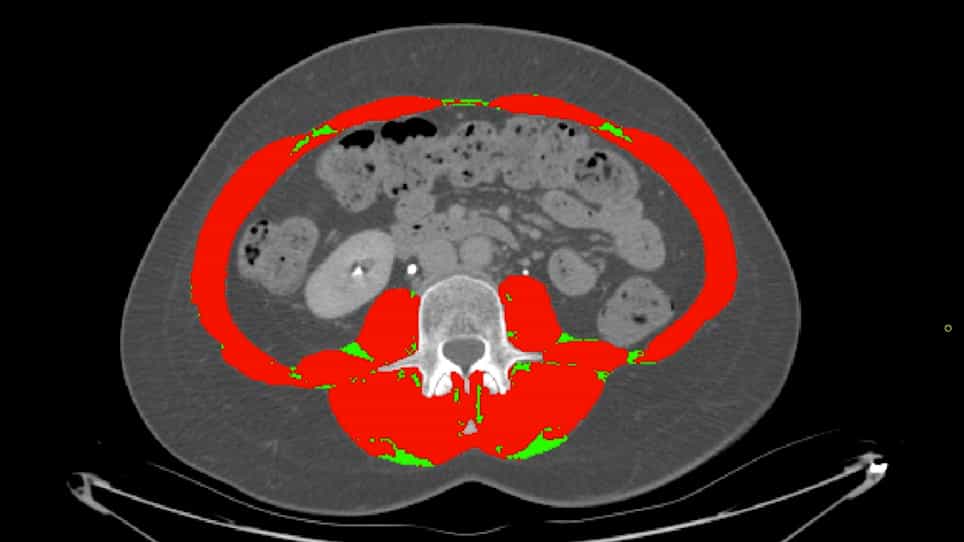

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Sarcopenia is associated with blood transfusions in head and neck cancer free flap surgery
Alexander Joseph Jones1, Vincent J Campiti1, Mohamedkazim Alwani1
1Department of Otolaryngology-Head and Neck Surgery Indiana University School of Medicine Indianapolis Indiana USA.

Insights
Sarcopenia, a loss of muscle mass, is linked to higher blood transfusion needs in head and neck cancer free flap reconstruction. Patients with sarcopenia require more blood products during and after surgery.
Area of Science:
- Oncology
- Surgical Reconstruction
- Hematology
Background:
- Head and neck cancer free flap reconstruction (HNCFFR) is a complex procedure.
- Blood transfusions are common but carry risks and resource implications.
- Sarcopenia, characterized by skeletal muscle loss, is increasingly recognized as a comorbidity impacting surgical outcomes.
Purpose of the Study:
- To investigate the association between sarcopenia and blood transfusion requirements in patients undergoing HNCFFR.
- To identify predictors of intraoperative, postoperative, and perioperative blood transfusions in this patient population.
Main Methods:
- Retrospective review of 239 HNCFFR patients (2014-2019) with preoperative imaging.
- Data collected included demographics, comorbidities (mCCI), sarcopenia status, oncologic history, and perioperative transfusion data.
- Binary logistic regression analyzed predictors of blood transfusion, including intraoperative, postoperative, and perioperative requirements.
Main Results:
- Sarcopenia was present in 25.9% of patients and was an independent predictor of intraoperative (P=.023) and perioperative (P=.021) transfusions.
- Other predictors included modified Charlson Comorbidity Index (mCCI), preoperative hemoglobin, operative time, estimated blood loss (EBL), and Clavien-Dindo (CD) score.
- Intraoperative transfusions were associated with older age, alcoholism, higher mCCI, lower hemoglobin, non-forearm flaps, longer operative times, and greater EBL.
Conclusions:
- Sarcopenia is a significant predictor of increased blood transfusion requirements in HNCFFR.
- Preoperative counseling regarding transfusion risks for sarcopenic patients is recommended.
- Resource allocation should consider the higher blood product needs in sarcopenic patients undergoing HNCFFR.
Objective:
To determine if sarcopenia is a predictor of blood transfusion requirements in head and neck cancer free flap reconstruction (HNCFFR).
Methods:
A single-institution, retrospective review was performed of HNCFFR patients with preoperative abdominal imaging from 2014 to 2019. Demographics, comorbidities (modified Charlson Comorbidity Index [mCCI]), skeletal muscle index (cm2/m2), oncologic history, intraoperative data, and 30-day postoperative complications (Clavien-Dindo score [CD]) were collected. Binary logistic regression was performed to determine predictors of transfusion.
Results:
Eighty (33.5%), 66 (27.6%), and 110 (46.0%) of n = 239 total patients received an intraoperative, postoperative, or any perioperative blood transfusion, respectively. Sixty-two (25.9%) patients had sarcopenia. Patients receiving intraoperative transfusions had older age (P = .035), more frequent alcoholism (P = .028) and sarcopenia (P < .001), greater mCCI (P < .001), lower preoperative hemoglobin (P < .001), reconstruction with flaps other than forearm (P = .003), and greater operative times (P = .001), intravenous fluids (P < .001), and estimated blood loss (EBL, P < .001). Postoperative transfusions were associated with major complications (CD ≥ 3; P < .001). Multivariate regression determined sarcopenia (P = .023), mCCI (P = .013), preoperative hemoglobin (P = .002), operative time (P = .036), and EBL (P < .001) as independent predictors of intraoperative transfusion requirements. Postoperative transfusions were predicted by preoperative hemoglobin (P = .007), osseous flap (P = .036), and CD ≥ 3 (P < .001). A perioperative transfusion was predicted by sarcopenia (P = .021), preoperative hemoglobin (P < .001), operative time (P = .008), and CD ≥ 3 (P = .018).
Conclusion:
Sarcopenia is associated with increased blood transfusions in HNCFFR. Patients should be counseled preoperatively on the associated risks, and the increased blood product requirement should be accounted in resource-limited scenarios.
Level Of Evidence:
4.