Related Experiment Video
Updated: Nov 8, 2025
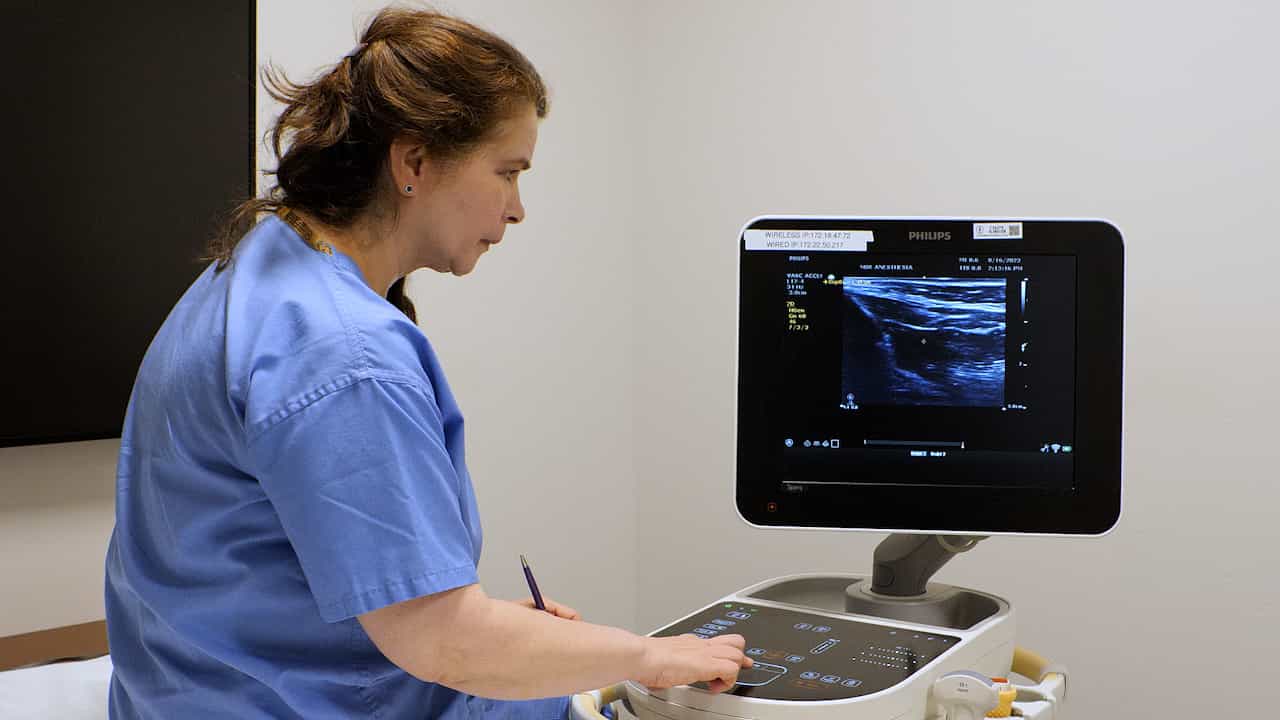

Point-of-Care Ultrasound: A Review of Ultrasound Parameters for Predicting Difficult Airways
Published on: April 7, 2023
Dyspnoea and respiratory muscle ultrasound to predict extubation failure
Martin Dres1,2,3,4, Thomas Similowski5,2, Ewan C Goligher4,6
1AP-HP, Groupe Hospitalier Universitaire, AP-HP, Sorbonne Université, Site Pitié-Salpêtrière, Service de Pneumologie, Médecine Intensive Réanimation (Département R3S), Paris, France martin.dres@aphp.fr.

Background:
This study investigated dyspnoea intensity and respiratory muscle ultrasound early after extubation to predict extubation failure.
Methods:
The study was conducted prospectively in two intensive care units in France and Canada. Patients intubated for at least 48 h were studied within 2 h after an extubation following a successful spontaneous breathing trial. Dyspnoea was evaluated by a dyspnoea visual analogue scale (Dyspnoea-VAS) ranging from 0 to 10 and the Intensive Care Respiratory Distress Observational Scale (IC-RDOS). The ultrasound thickening fraction of the parasternal intercostal and the diaphragm was measured; limb muscle strength was evaluated using the Medical Research Council (MRC) score (range 0-60).
Results:
Extubation failure occurred in 21 out of 122 enrolled patients (17%). The median (interquartile range (IQR)) Dyspnoea-VAS and IC-RDOS were higher in patients with extubation failure versus success: 7 (4-9) versus 3 (1-5) (p<0.001) and 3.7 (1.8-5.8) versus 1.7 (1.5-2.1) (p<0.001), respectively. The median (IQR) ratio of parasternal intercostal muscle to diaphragm thickening fraction was significantly higher and MRC was lower in patients with extubation failure compared with extubation success: 0.9 (0.4-2.1) versus 0.3 (0.2-0.5) (p<0.001) and 45 (36-50) versus 52 (44-60) (p=0.012), respectively. The thickening fraction of the parasternal intercostal and its ratio to diaphragm thickening showed the highest area under the receiver operating characteristic curve (AUC) for an early prediction of extubation failure (0.81). AUCs of Dyspnoea-VAS and IC-RDOS reached 0.78 and 0.74, respectively.
Conclusions:
Respiratory muscle ultrasound and dyspnoea measured within 2 h after extubation predict subsequent extubation failure.

Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: