Related Experiment Video
Updated: Nov 8, 2025
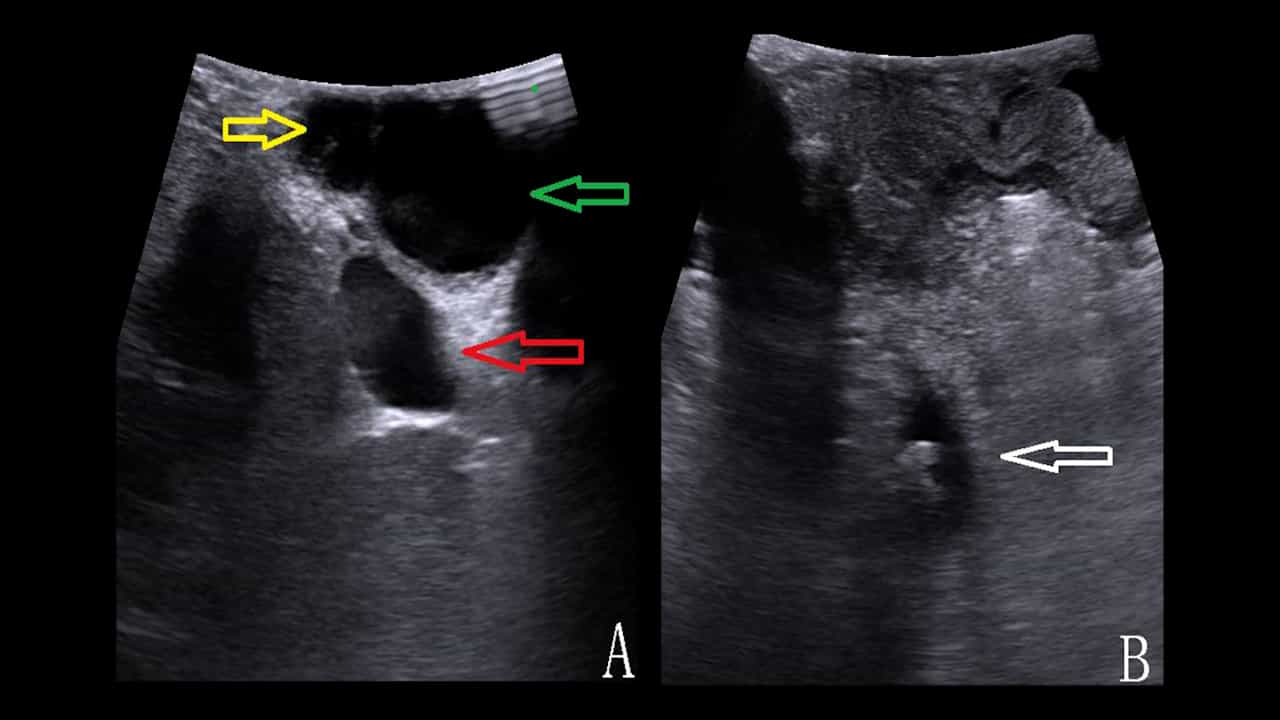
Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
Laparoscopic cholecystectomy for acute cholecystitis: onset of symptoms and severity grade as a tool for choosing the
Giuseppe Palomba1, Vincenza P Dinuzzi2, Alfonso Amendola2
1Department of Clinical Medicine and Surgery, Federico II University, Naples, Italy - giuseppepalomba3@virgilio.it.

Background:
Acute cholecystitis is an acute inflammation of the gallbladder. It represents one-third of all surgical emergency hospital admissions and has significant socioeconomic impact. Laparoscopic cholecystectomy, regardless of age, is the gold standard for this disease, but the optimal timing of surgical intervention is an open issue since the 2007 Tokyo guidelines.
Methods:
We recruited from March 2015 to June 2018, in a retrospective study, 144 patients with acute cholecystitis and treated with laparoscopic cholecystectomy. The patients were divided into two groups: group A (N.=66), operated within 72 hours and group B (N.=78), between 72 hours and 1 week after the onset of symptoms. After, the two groups were further stratified by the grade of severity of acute cholecystitis in according to the Tokyo guidelines: in group A, 39 patients were grade I and 27 grade II; in group B, 48 patients were grade I and 30 grade II.
Results:
The operative time was longer in group B patients versus group A. In group B, there was a greater difficulty in dissecting and detecting the Calot's triangle, more conversions to open, a greater mean length of hospital stay and more post-operative days. In patients with grade II, especially in the group B, were greater inflammation stage, conversions to open, difficulty in the dissection of the Calot's triangle, mean length of hospital stay and post-operative days. The operative timing within 72 hours in patients with grade I, have only advantage in the mean length of hospital stay, while in grade II, the advantages are also in the lesser difficulty in dissecting the Calot's triangle, fewer conversions and fewer post-operative days.
Conclusions:
Early laparoscopic cholecystectomy for acute cholecystitis should be performed considering not only the onset of symptoms, but above all the grade of severity of AC in according with TG. Grade II, particularly, must be treated within 72 hours and by experienced surgeon.
Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...