Related Experiment Video
Updated: Nov 8, 2025


Comparison of Agreement and Accuracy using Binocular Wavefront Optometer with Autorefractor and Phoropter
Published on: September 16, 2025
Falsely high rebound tonometry
Brooke Saffren1, Jade M Price2, Qiang Ed Zhang3
1Pediatric Ophthalmology and Ocular Genetics, Wills Eye Hospital, Philadelphia, Pennsylvania; Philadelphia College of Osteopathic Medicine, Philadelphia, Pennsylvania.

Insights
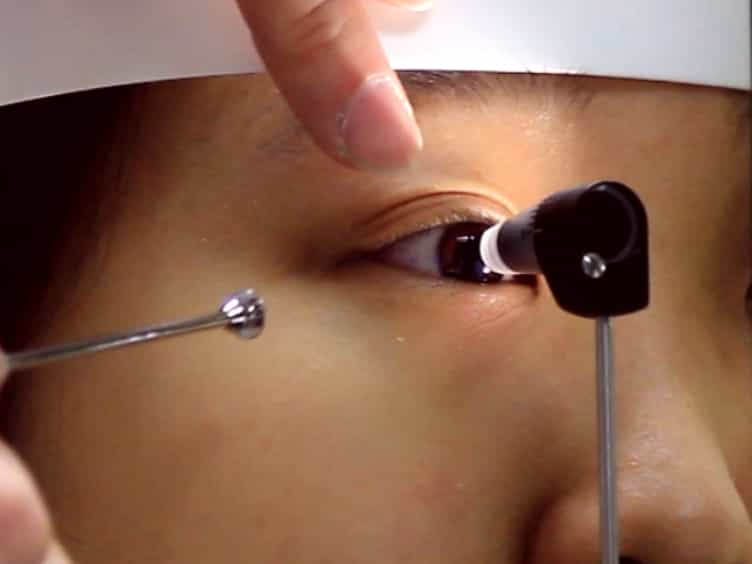
Rebound tonometry (RBT) may overestimate intraocular pressure (IOP) in children, showing a difference of 6 mm Hg or more compared to applanation tonometry (AT). Factors like persistent fetal vasculature and larger corneal diameter increase this discrepancy.
Area of Science:
- Ophthalmology
- Pediatric Medicine
- Medical Device Technology
Background:
- Rebound tonometry (RBT) is an alternative for measuring intraocular pressure (IOP) in pediatric patients who cannot tolerate applanation tonometry (AT).
- RBT measurements typically exceed AT readings by 2-3 mm Hg.
- A significant discrepancy (≥6 mm Hg) between RBT and AT readings has been observed in some children.
Purpose of the Study:
- To identify demographic and ocular characteristics associated with a significant artifactuous discrepancy between RBT and AT intraocular pressure measurements in pediatric patients.
Main Methods:
- Retrospective review of medical records for pediatric patients with IOP measured by RBT followed by AT within a 6-month period.
- Exclusion criteria included intervening surgery or changes in medical management between measurements.
- Analysis focused on identifying predictors of a greater than or equal to 6 mm Hg difference between RBT and AT readings.
Main Results:
- 18.5% of eyes with normal IOP (≤24 mm Hg) showed a ≥6 mm Hg RBT-AT difference, with risk factors including persistent fetal vasculature (PFV), increased corneal diameter, and higher initial RBT (>20).
- 77% of eyes with elevated IOP (>24 mm Hg) exhibited a ≥6 mm Hg RBT-AT difference, with larger corneal diameter being the sole predictor.
- Corneal opacity or iris abnormalities were associated with a lower likelihood of significant RBT-AT difference in eyes with elevated IOP.
Conclusions:
- A significant discrepancy (≥6 mm Hg) between RBT and AT IOP measurements can occur in pediatric patients.
- Caution is advised when interpreting RBT values in children with PFV, increased corneal diameter, and high initial RBT readings.
Background:
Rebound tonometry (RBT) can be used to measure intraocular pressure (IOP) in children unable to tolerate measurement with applanation tonometry (AT) while awake. RBT readings are often 2-3 mm Hg higher than AT. We have experienced children with a repeatedly higher difference between RBT and AT measurements (≥6 mm Hg). The purpose of this study was to identify demographic and ocular characteristics that contribute to this artifactuous discrepancy.
Methods:
The medical records of pediatric patients with IOP measured by RBT followed by AT within 6 months without intervening surgery or change in medical management were retrospectively reviewed to identify potential predictors of greater difference between RBT and AT readings.
Results:
A total of 123 eyes of 65 patients were included. In patients with normal IOP (≤24 mm Hg), 18.5% had a ≥6 mm Hg difference between RBT and AT, with RBT being higher. Risk factors for this included presence of persistent fetal vasculature (PFV), increased corneal diameter, and higher initial RBT value (>20). In patients with elevated IOP (>24 mm Hg), 77% had ≥6 mm Hg difference, with larger corneal diameter being the sole predictor. Eyes were less likely to have significant RBT-AT difference if there was corneal opacity or iris abnormalities in eyes with elevated IOP (>24 mm Hg).
Conclusions:
In some children, RBT readings are ≥ 6 mm Hg higher than AT readings. Caution should be taken when interpreting RBT values in patients with PFV, increased corneal diameter, and higher initial RBT values.

Related Concept Videos
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:17
Measurement of Blood Pressure
 01:18
Errors in Taping
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:17
Common Leveling Mistakes and Errors
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.