Nemonoxacin dosage adjustment in patients with severe renal impairment based on population pharmacokinetic and pharmacodynamic analysis
Related Experiment Video
Updated: Nov 7, 2025

Estimation of Nephron Number in Whole Kidney using the Acid Maceration Method
Published on: May 22, 2019
Yi Li1,2,3, Jianda Lu4, Yue Kang1,2,3
1Institute of Antibiotics, Huashan Hospital, Fudan University, Shanghai, China.

Aims:
To optimize the dosing regimen in patients with severe renal impairment based on population pharmacokinetic (PPK)/pharmacodynamic analysis.
Methods:
The pharmacokinetics and safety of nemonoxacin was evaluated in a single-dose, open-label, nonrandomized, parallel-group study after single oral dose of a 0.5-g nemonoxacin capsule in 10 patients with severe renal impairment and 10 healthy controls. Both blood and urine samples were collected within 72 hours after admission and determined the concentrations. A PPK model was built using nonlinear mixed effects modelling. The probability of target attainment and the cumulative fraction of response against Streptococcus pneumoniae and Staphylococcus aureus was calculated by Monte Carlo simulation.
Results:
The data best fitted a 2-compartment model, from which the PPK parameters were estimated, including clearance (8.55 L/h), central compartment volume (80.8 L) and peripheral compartment volume (50.6 L). The accumulative urinary excretion was 23.4 ± 6.5% in severe renal impairment patients and 66.1 ± 16.8% in healthy controls. PPK/pharmacodynamic modelling and simulation of 4 dosage regimens found that nemonoxacin 0.5 g every 48 hours (q48h) was the optimal dosing regimen in severe renal impairment patients, evidenced by higher probability of target attainment (92.7%) and cumulative fraction of response (>99%) at nemonoxacin minimum inhibitory concentration ≤ 1 mg/L against S. pneumoniae and S. aureus. The alternative regimens (0.25 g q24h; loading dose 0.5 g on Day 1 followed by 0.25 g q24h) were insufficient to cover the pathogens even if minimum inhibitory concentration = 1 mg/L.
Conclusion:
An extended dosing interval (0.5 g q48h) may be appropriate for optimal efficacy of nemonoxacin in case of severe renal impairment.
More Related Videos
 08:50
5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
 07:45
Estimation of Urinary Nanocrystals in Humans using Calcium Fluorophore Labeling and Nanoparticle Tracking Analysis
Published on: February 9, 2021
Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:23
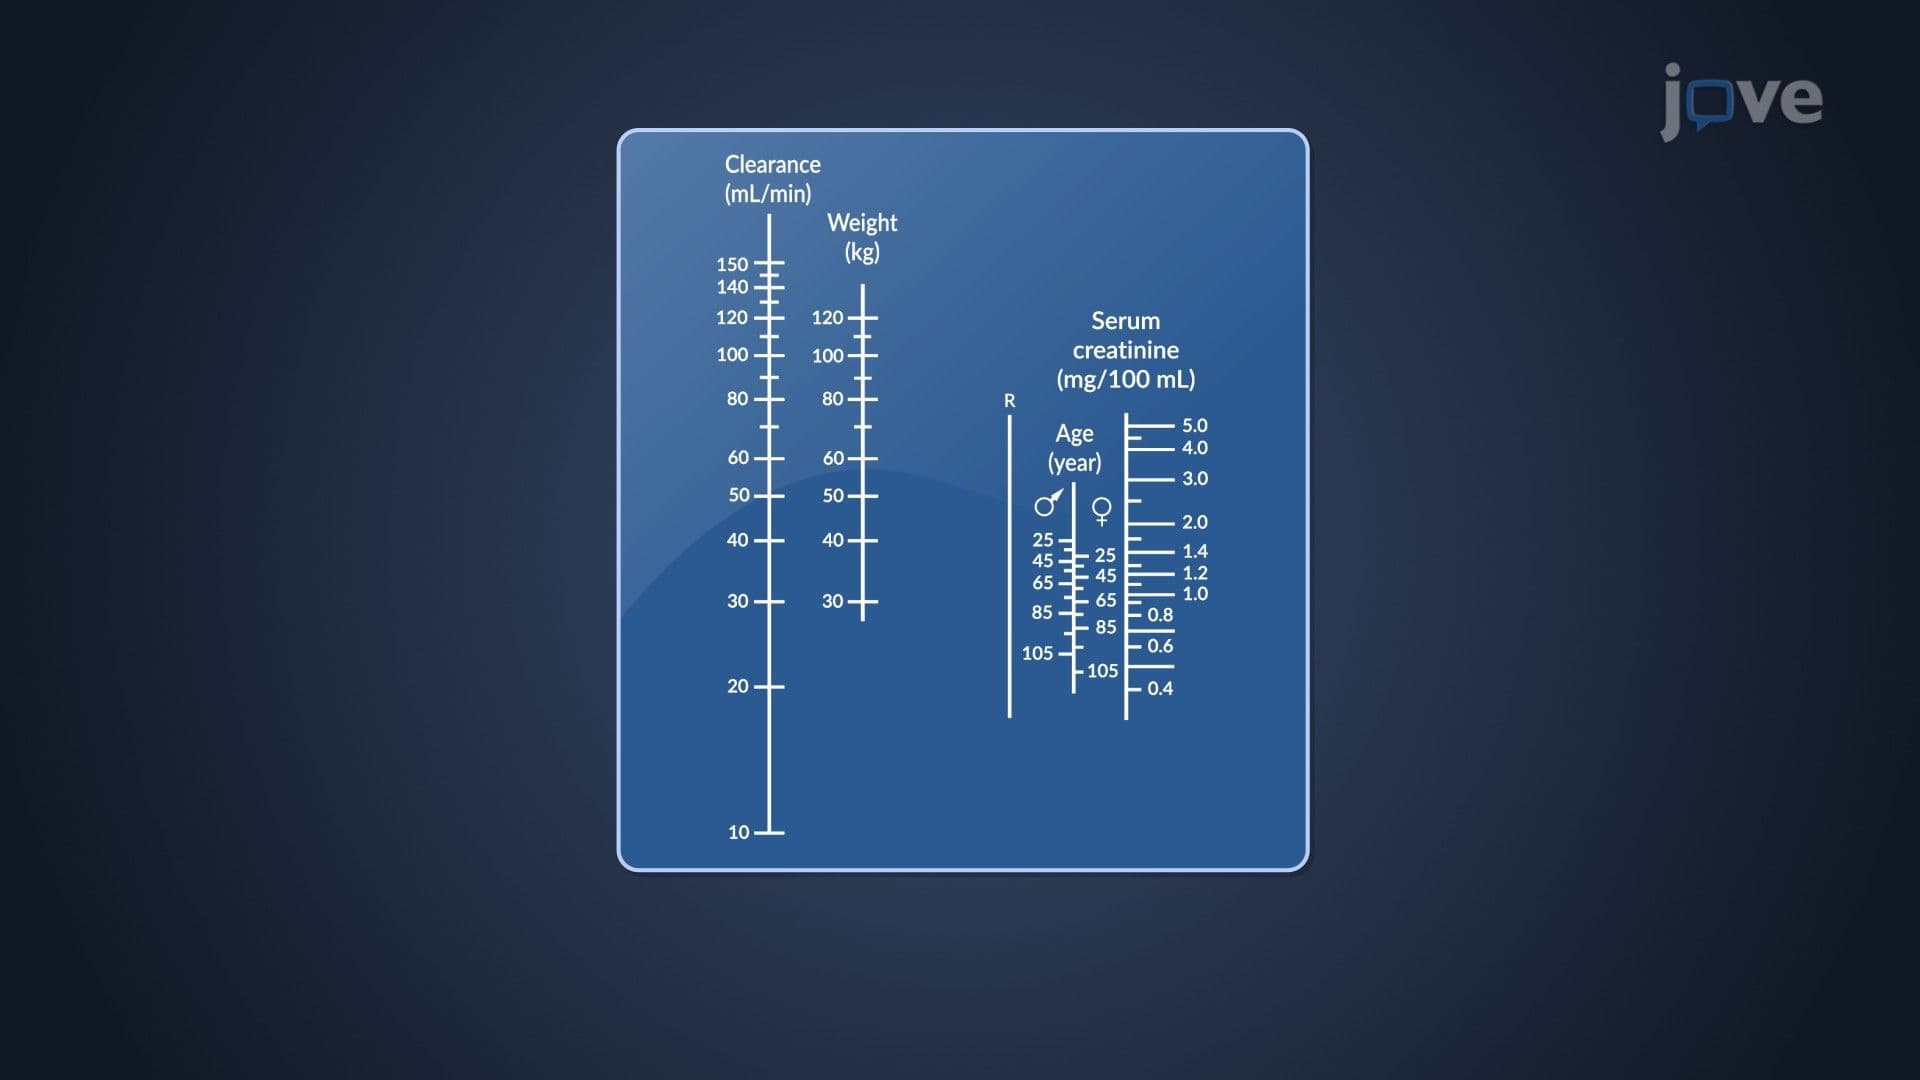
Dosage Regimen Designs: Nomograms and Tabulations
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:25
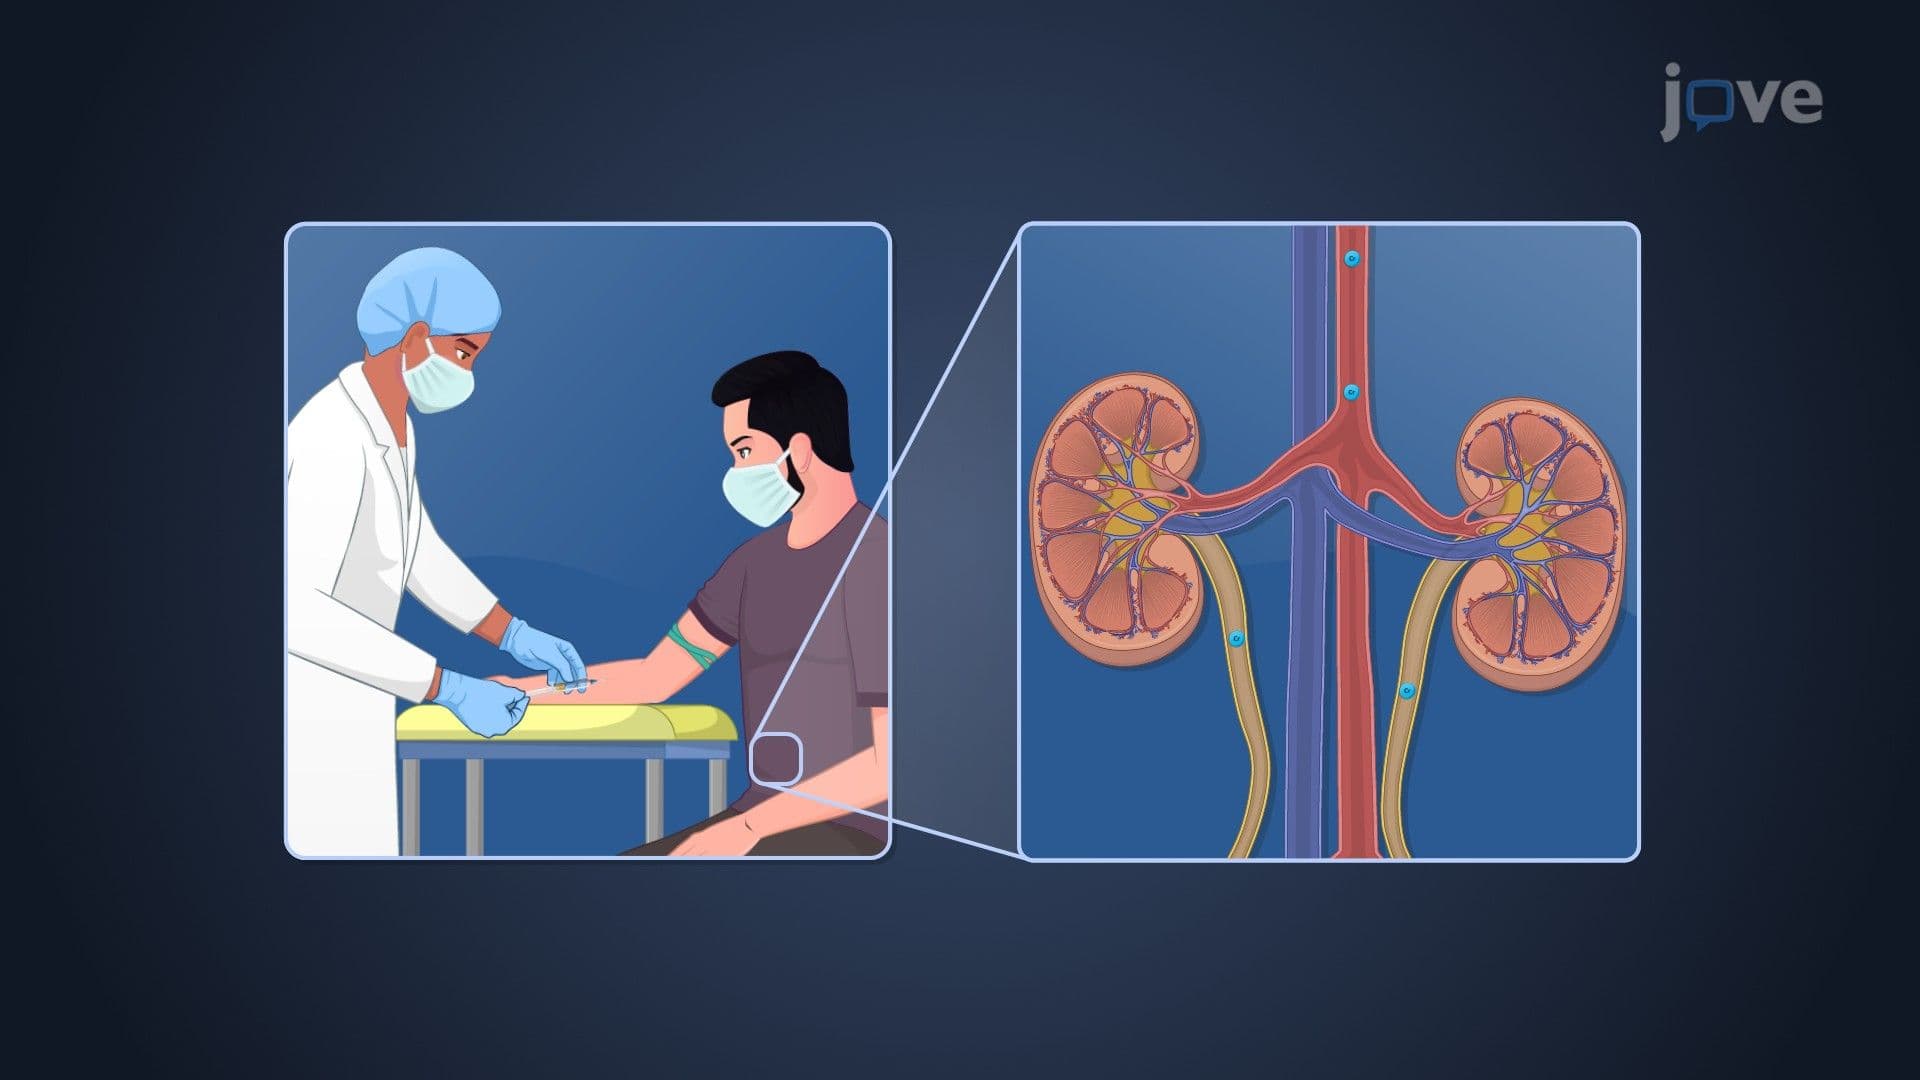
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance