Related Experiment Video
Updated: Nov 7, 2025
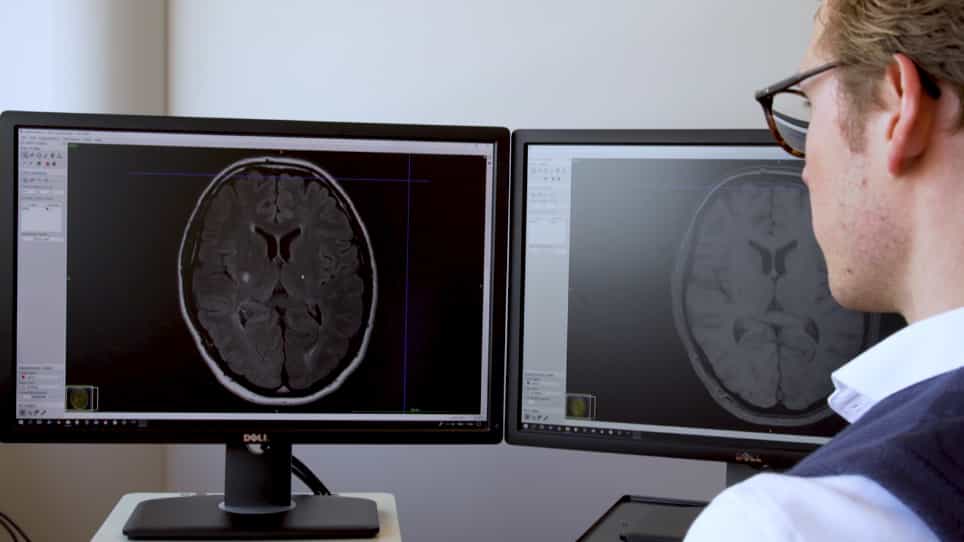
Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Neural Network-derived Perfusion Maps for the Assessment of Lesions in Patients with Acute Ischemic Stroke
Raphael Meier1, Paula Lux1, B Med1
1Support Center for Advanced Neuroimaging-University Institute of Diagnostic and Interventional Neuroradiology (R. Meier, P.L., J.G., R.W., R. McKinley, J.K.), Department of Neurology (S.J., U.F., J.K.), Institute for Surgical Technology and Biomechanics (M.R.), and Institute for Diagnostic, Interventional and Pediatric Radiology (J.K.), University Hospital Inselspital and University of Bern, Freiburgstrasse 4, 3010 Bern, Switzerland.

Purpose:
To perform a proof-of-concept study to investigate the clinical utility of perfusion maps derived from convolutional neural networks (CNNs) for the workup of patients with acute ischemic stroke presenting with a large vessel occlusion.
Materials And Methods:
Data on endovascularly treated patients with acute ischemic stroke (n = 151; median age, 68 years [interquartile range, 59-75 years]; 82 of 151 [54.3%] women) were retrospectively extracted from a single-center institutional prospective registry (between January 2011 and December 2015). Dynamic susceptibility perfusion imaging data were processed by applying a commercially available reference method and in parallel by a recently proposed CNN method to automatically infer time to maximum of the tissue residue function (Tmax) perfusion maps. The outputs were compared by using quantitative markers of tissue at risk derived from manual segmentations of perfusion lesions from two expert raters.
Results:
Strong correlations of lesion volumes (Tmax > 4 seconds, > 6 seconds, and > 8 seconds; R = 0.865-0.914; P < .001) and good spatial overlap of respective lesion segmentations (Dice coefficients, 0.70-0.85) between the CNN method and reference output were observed. Eligibility for late-window reperfusion treatment was feasible with use of the CNN method, with complete interrater agreement for the CNN method (Cohen κ = 1; P < .001), although slight discrepancies compared with the reference-based output were observed (Cohen κ = 0.609-0.64; P < .001). The CNN method tended to underestimate smaller lesion volumes, leading to a disagreement between the CNN and reference method in five of 45 patients (9%).
Conclusion:
Compared with standard deconvolution-based processing of raw perfusion data, automatic CNN-derived Tmax perfusion maps can be applied to patients who have acute ischemic large vessel occlusion stroke, with similar clinical utility.© RSNA, 2019Supplemental material is available for this article.
More Related Videos
 12:15
Optimized System for Cerebral Perfusion Monitoring in the Rat Stroke Model of Intraluminal Middle Cerebral Artery Occlusion
Published on: February 17, 2013
 06:45
Author Spotlight: Integrated Photoacoustic, Ultrasound, and Angiographic Tomography (PAUSAT) for NonInvasive Whole-Brain Imaging of Ischemic Stroke
Published on: June 2, 2023
