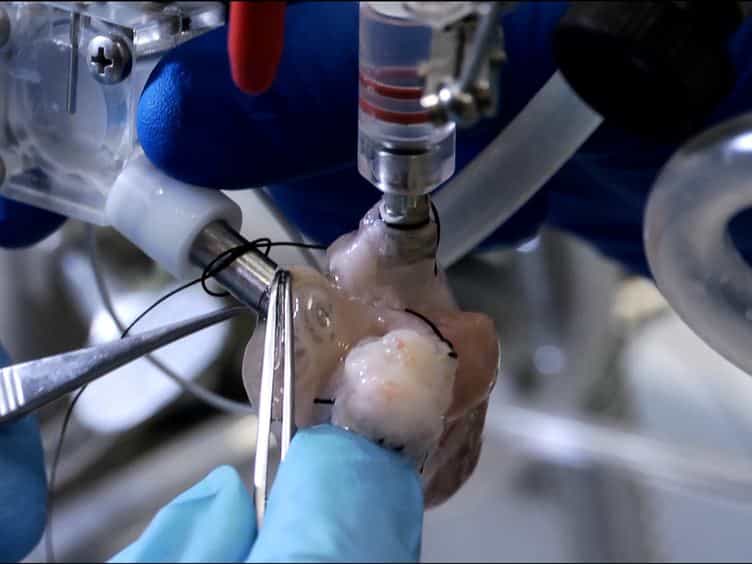
Related Experiment Video
Updated: Sep 11, 2026
Multiparametric Optical Mapping of the Langendorff-perfused Rabbit Heart
Published on: September 13, 2011
Effects of ouabain and isoproterenol on left ventricular diastolic function during low-flow ischemia in isolated,
B H Lorell1, S Isoyama, W N Grice
1Cardiac Muscle Research Laboratory, Boston University School of Medicine, Massachusetts.

Abstract:
Myocardial ischemia causes both systolic and diastolic dysfunction. A variety of positive inotropic agents with different subcellular mechanisms may be used clinically in an attempt to reverse ischemic contractile failure. We tested the hypothesis that two inotropic agents, isoproterenol (a beta-adrenergic agonist) and ouabain (a sodium pump inhibitor), might have different effects on left ventricular (LV) diastolic function during ischemic failure despite an equivalent inotropic effect. Isolated isovolumic (balloon-in-LV) blood perfused rabbit hearts were paced at constant physiological heart rate (4 Hz), given either no drug (controls, n = 7), isoproterenol (n = 7), or ouabain (n = 7), and then subjected to 6 minutes of low flow ischemia (75% reduction of baseline coronary flow). The doses of isoproterenol and ouabain were selected to produce equivalent modest inotropic effects (15% increase in LV + dP/dt) in each heart during baseline perfusion conditions. During the ischemic period, there was a marked decrease in contractility, and neither isoproterenol nor ouabain demonstrated a positive inotropic effect relative to the control group. However, these agents had markedly different effects on diastolic chamber distensibility (assessed by end-diastolic pressure at constant LV volume) during ischemia. In the control and isoproterenol groups, diastolic chamber distensibility did not change during the ischemic period. In contrast, ouabain treatment resulted in a marked decrease in diastolic chamber distensibility during ischemia; this change was not completely reversible during the 10-minute reperfusion period. The mechanism by which ouabain decreased diastolic chamber distensibility relative to isoproterenol was assessed indirectly. The ouabain and isoproterenol groups were subjected to equivalent degrees of ischemia as assessed by oxygen supply/demand imbalance; during ischemia, each drug group did not differ with regard to myocardial perfusion rates, determinants of myocardial oxygen demand (heart rate, LV developed pressure, LV + dP/dt), myocardial oxygen consumption, lactate production, and ATP and creatine phosphate content. We therefore inferred that the greater decrease in diastolic distensibility in the ouabain group was not due to a greater metabolic severity of ischemia. These observations are consistent with a mechanism of cytosolic calcium overload induced by ouabain, resulting in persistent active myofilament tension development throughout diastole, to cause the observed decrease in diastolic chamber distensibility during ischemia in the ouabain group.(ABSTRACT TRUNCATED AT 400 WORDS)
Insights
Ouabain, unlike isoproterenol, impairs diastolic function during myocardial ischemia by causing cytosolic calcium overload. This leads to reduced chamber distensibility, persisting even after reperfusion.
Area of Science:
- Cardiology
- Pharmacology
- Physiology
Background:
- Myocardial ischemia induces systolic and diastolic dysfunction.
- Positive inotropic agents are used to treat ischemic contractile failure.
- Different agents may have varied effects on diastolic function.
Purpose of the Study:
- To test if isoproterenol and ouabain have different effects on left ventricular diastolic function during ischemia.
- To compare the effects of a beta-adrenergic agonist versus a sodium pump inhibitor on diastolic function.
Main Methods:
- Isolated rabbit hearts were perfused and subjected to low-flow ischemia.
- Hearts received either no drug, isoproterenol, or ouabain at equivalent inotropic doses.
- Diastolic chamber distensibility was assessed by end-diastolic pressure.
Main Results:
- Neither drug improved contractility during ischemia.
- Isoproterenol did not alter diastolic chamber distensibility.
- Ouabain significantly decreased diastolic chamber distensibility during ischemia, with incomplete recovery.
Conclusions:
- Ouabain, but not isoproterenol, impairs diastolic function during ischemia.
- The mechanism involves ouabain-induced cytosolic calcium overload.
- This leads to increased diastolic tension and reduced distensibility.