Related Experiment Video
Updated: Nov 6, 2025
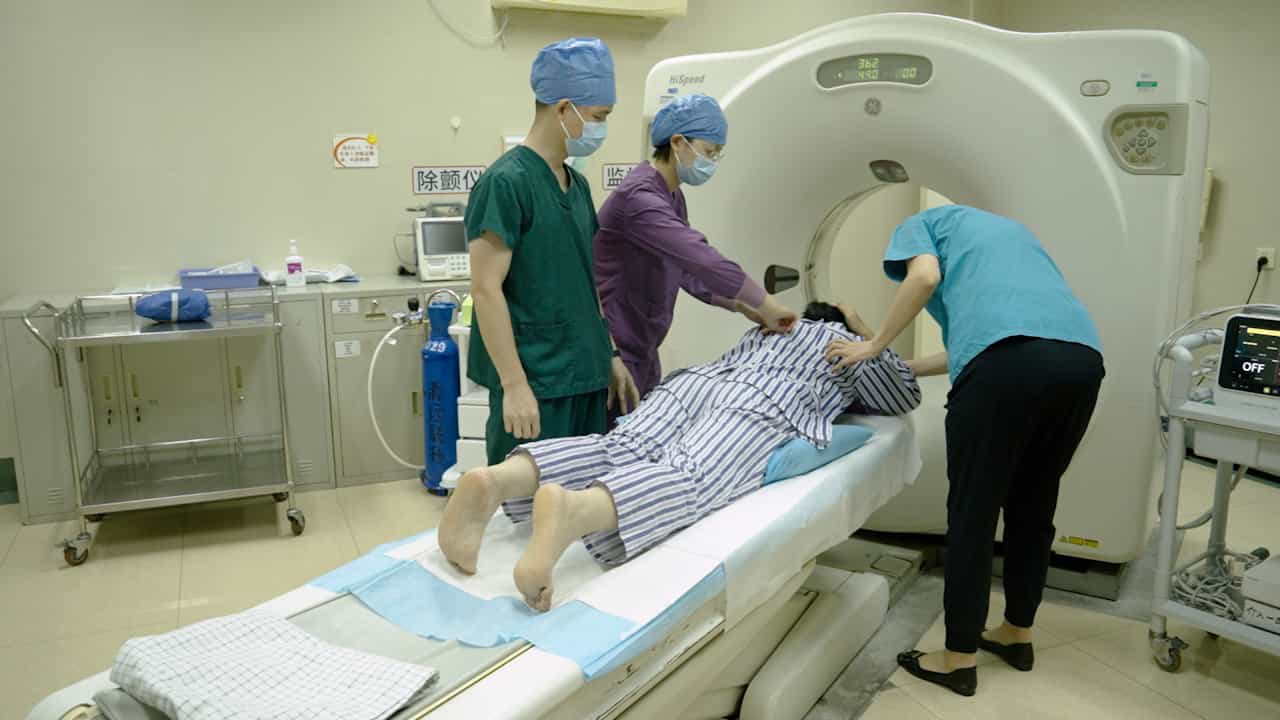
Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Persistence of uncontrolled hypertension post-cardiac rehabilitation in stable coronary patients
Thierry Denolle1, Claude Pellen2, Anne Laure Serandour2
1Rivarance Network, Arthur Gardiner Hospital Dinard, Dinard, France. denolle.thierry@wanadoo.fr.

Insights
Hypertension management in stable coronary heart disease patients often fails long-term post-cardiac rehabilitation. Key factors include reduced beta-blockade, physician inertia, and guideline non-adherence, leading to uncontrolled blood pressure.
Area of Science:
- Cardiology
- Preventive Medicine
- Clinical Pharmacy
Background:
- Uncontrolled cardiovascular risk factors, particularly hypertension, are linked to myocardial infarction in stable coronary heart disease.
- Effective management of hypertension is crucial for secondary prevention in these patients.
Purpose of the Study:
- To analyze the long-term management and control of hypertension in stable coronary heart disease patients following cardiac rehabilitation.
- To identify factors contributing to the lack of sustained blood pressure control one year after cardiac rehabilitation.
Main Methods:
- Prospective study of 746 stable coronary patients (2005-2015).
- Documentation of risk factors and pharmacological treatments pre-, immediately post-, and 1-year post-cardiac rehabilitation.
- Analysis of blood pressure control rates and contributing factors to hypertension recurrence.
Main Results:
- While other risk factors improved, hypertension control remained poor one year post-cardiac rehabilitation (49% controlled vs. 20% or 10% by guidelines).
- 42% of patients achieving normotension post-rehabilitation had uncontrolled hypertension at 1 year, with increased weight and decreased physical activity/antihypertensive use.
- Factors associated with elevated blood pressure included beta-blockade discontinuation (+7.9 mmHg), age >65 (+6.2 mmHg), and diabetes mellitus (+7.6 mmHg).
- Only 48% received guideline-recommended antihypertensive polytherapy, and 61% of prescriptions were not adjusted post-rehabilitation.
Conclusions:
- Hypertension is the only cardiovascular risk factor that does not improve one year post-cardiac rehabilitation.
- Reasons for persistent uncontrolled hypertension include reduced beta-blockade, physician inertia, and poor adherence to international guidelines.
- Optimizing hypertension management requires sustained pharmacological treatment adjustments and adherence to evidence-based guidelines.
Abstract:
In stable coronary heart disease, uncontrolled risk factors are strongly associated with incident myocardial infarction. We analysed the management of hypertension in 746 stable coronary patients recruited between 2005 and 2015 in a single-centre prospective study. Risk factors and pharmacological treatments were documented prior to and immediately after cardiac rehabilitation, and 1 year later. One year post-cardiac rehabilitation, all cardiovascular risk factors were significantly better controlled with the notable exception of hypertension: blood pressure (BP) <140/90 mmHg in 60% of the total population vs 49% (N = 450) of hypertensive patients (20% or 10%, according to the ACC/AHA 2017 or ESH/ESC guidelines, respectively). Of those who had achieved normotension by the end of cardiac rehabilitation, 42% had uncontrolled hypertension again 1 year later; in addition, body weight had increased, while physical activity and antihypertensive drug use had dropped (differences between controlled or uncontrolled hypertension at 1 year post-cardiac rehabilitation, NS). Three factors were correlated with BP elevations: discontinuation of betablockade: +7.9 mmHg; age >65 years: +6.2 mmHg; diabetes mellitus: +7.6 mmHg. Only 48% hypertensive patients were on guideline-recommended antihypertensive polytherapy. Although 28% were still hypertensive post-cardiac rehabilitation, and hypertension remained uncontrolled in 70% 1 year later, 61% antihypertensive prescriptions were not adjusted post-cardiac rehabilitation. One year post-cardiac rehabilitation, hypertension was the only cardiovascular risk factor that had not improved. This can be attributed to three main reasons, all associated with BP elevations: precipitous reduction in betablockade, physicians' inertia when faced with uncontrolled hypertension and lack of adherence to international guidelines.
More Related Videos
 08:35
Improved Renal Denervation Mitigated Hypertension Induced by Angiotensin II Infusion
Published on: May 26, 2022
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Related Concept Videos
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:18
Hypertension and Regulation of Blood Pressure
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:23
Hypertension V: Nursing Management