Related Experiment Video
Updated: Nov 6, 2025
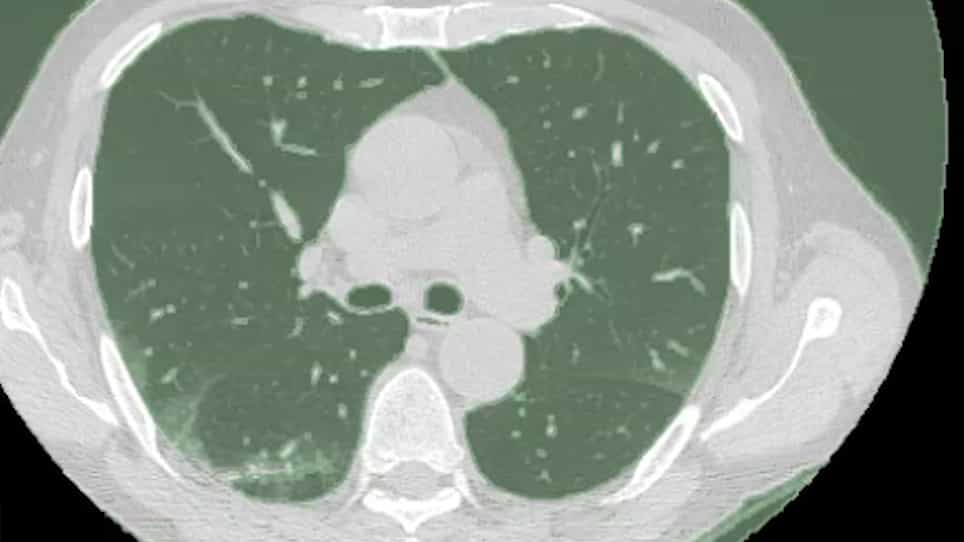

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Identification of Distinct Clinical Subphenotypes in Critically Ill Patients With COVID-19
Charles R Vasquez1, Shruti Gupta2, Todd A Miano3
1Department of Surgery, Perelman School of Medicine, University of Pennsylvania, Philadelphia, PA.

Background:
Subphenotypes have been identified in patients with sepsis and ARDS and are associated with different outcomes and responses to therapies.
Research Question:
Can unique subphenotypes be identified among critically ill patients with COVID-19?
Study Design And Methods:
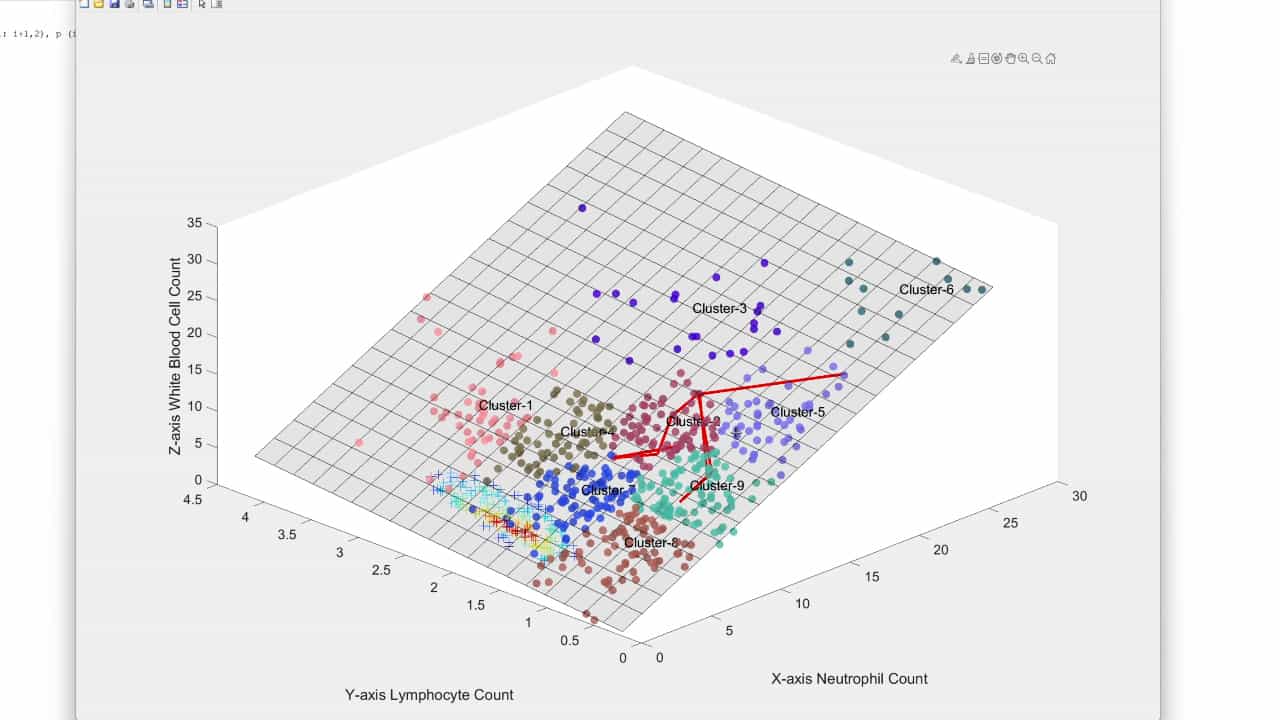
Using data from a multicenter cohort study that enrolled critically ill patients with COVID-19 from 67 hospitals across the United States, we randomly divided centers into discovery and replication cohorts. We used latent class analysis independently in each cohort to identify subphenotypes based on clinical and laboratory variables. We then analyzed the associations of subphenotypes with 28-day mortality.
Results:
Latent class analysis identified four subphenotypes (SP) with consistent characteristics across the discovery (45 centers; n = 2,188) and replication (22 centers; n = 1,112) cohorts. SP1 was characterized by shock, acidemia, and multiorgan dysfunction, including acute kidney injury treated with renal replacement therapy. SP2 was characterized by high C-reactive protein, early need for mechanical ventilation, and the highest rate of ARDS. SP3 showed the highest burden of chronic diseases, whereas SP4 demonstrated limited chronic disease burden and mild physiologic abnormalities. Twenty-eight-day mortality in the discovery cohort ranged from 20.6% (SP4) to 52.9% (SP1). Mortality across subphenotypes remained different after adjustment for demographics, comorbidities, organ dysfunction and illness severity, regional and hospital factors. Compared with SP4, the relative risks were as follows: SP1, 1.67 (95% CI, 1.36-2.03); SP2, 1.39 (95% CI, 1.17-1.65); and SP3, 1.39 (95% CI, 1.15-1.67). Findings were similar in the replication cohort.
Interpretation:
We identified four subphenotypes of COVID-19 critical illness with distinct patterns of clinical and laboratory characteristics, comorbidity burden, and mortality.

Related Concept Videos
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...