
Modified "Blumgart-Type" Suture for Wirsung-Pancreaticogastrostomy: Technique and Results of a Pilot Study
Francesco Paolo Prete1, Giovanna Di Meo1,2, Patrizia Liguori2
1Academic General Surgery Unit, Department of Biomedical Sciences and Human Oncology, Policlinico di Bari, Bari, Italy.

Introduction:
Postoperative pancreatic fistula (POPF) represents the principal determinant of morbidity and mortality after pancreaticoduodenectomy. Since 1994 we have been performing pancreaticogastrostomy with duct-to-mucosa anastomosis (Wirsung-pancreaticogastric anastomosis [WPGA]), but postoperative morbidity, although limited, was still a concern. An original pancreas-transfixing suture technique, named "Blumgart's anastomosis" (BA), has shown efficacy at reducing fistula rates from pancreaticojejunostomy. Few cohort studies have shown that WPGA with pancreas-transfixing stitches may help reduce the rate of POPF. We designed a novel "Blumgart-type" modification of WPGA (B-WPGA) aiming at harnessing the full potential of the Blumgart design.
Methods:
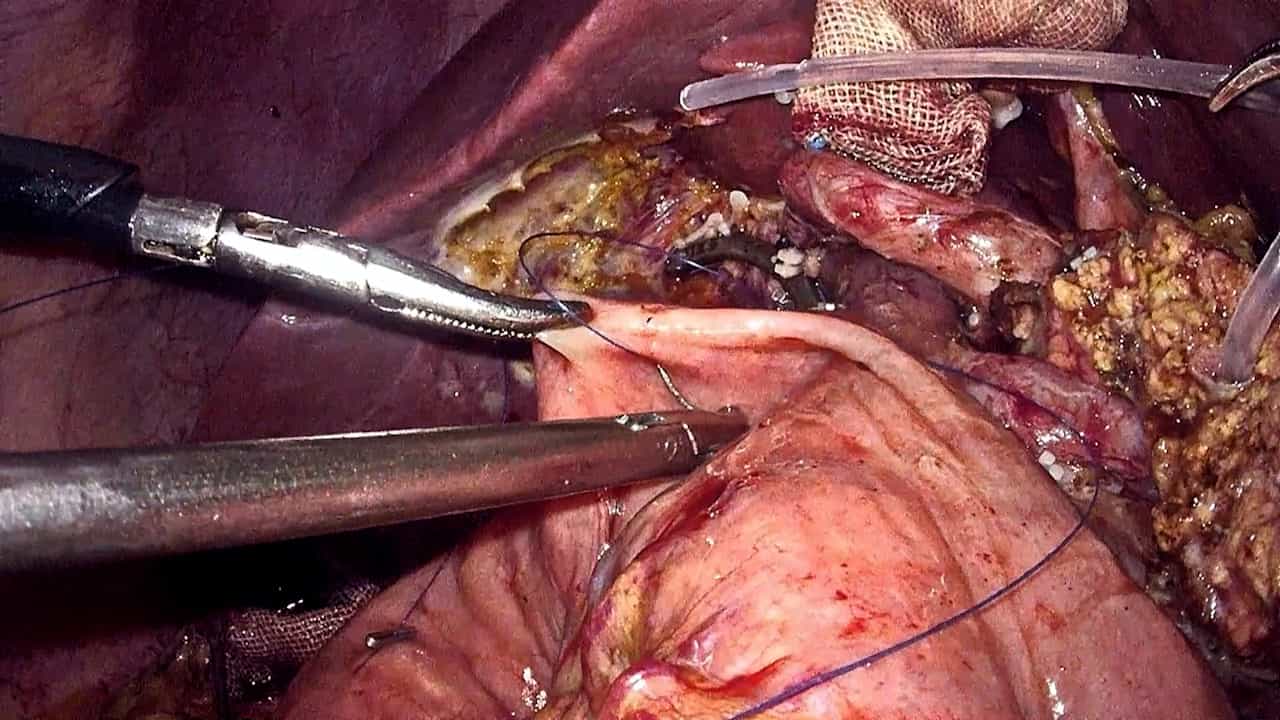
A prospective development study was designed around the application of B-WPGA after pancreaticoduodenectomy for primary periampullary tumors. It focused on describing the early iterations of this technique and on assessing the rate of POPF and delayed post-pancreatectomy hemorrhage (DPH) (primary outcomes), along with other perioperative outcomes. Technically, after mobilizing the pancreatic remnant for a few centimeters, the Wirsung duct is cannulated. A lozenge of seromuscular layer is excised from the posterior gastric wall, matching the shape and size of the pancreas's cut surface. Two to four transparenchymal pancreatic-to-gastric submucosa U stitches with 4/0 Gore-Tex are positioned cranially and caudally to the Wirsung duct, respectively, mounted on soft clamps, and tied onto the gastric serosa only after duct-to-mucosa anastomosis. Postoperative follow-up was standardized by protocol and included a pancreatic enzyme check on the drain output.
Results:
From February 2018 to June 2019, in 15 continuous cases, B-WPGA was performed after pancreaticoduodenectomy. Indications for pancreaticoduodenectomy were mainly ampulla of Vater and pancreatic head adenocarcinomas. There was no operative mortality and no pancreatic anastomosis-related morbidity. Two events (13%) of transiently elevated amylase in the drain fluid, not matching the definition of POPF, were identified in patients with a soft pancreas on postoperative day 2. No DPHs were recorded after a minimum follow-up of 18.6 months.
Discussion/Conclusion:
The principles of BA may be safely applied to the WPGA model. B-WPGA allows (1) gentle compression and closure of the small secondary ducts in the pancreatic remnant; (2) partial invagination of the pancreatic body in the gastric wall, with the pancreatic cut surface protected by the gastric submucosa; and (3) prevention of parenchymal fractures, as the pancreaticogastric stitches are tied onto the gastric serosa. Despite the limited number of cases in this study, the absence of mortality and anastomosis-related complications supports further reproduction of this technical variant. Larger studies are necessary to determine its efficacy.
Insights
This study introduces a modified pancreaticogastric anastomosis (B-WPGA) technique to reduce postoperative pancreatic fistula (POPF) after pancreaticoduodenectomy. The novel approach demonstrated no mortality or fistula-related complications in 15 patients, suggesting improved safety.
Area of Science:
- Surgical Innovation
- Gastrointestinal Surgery
- Oncology
Background:
- Postoperative pancreatic fistula (POPF) is a major complication after pancreaticoduodenectomy.
- Existing pancreaticogastrostomy with duct-to-mucosa anastomosis (WPGA) techniques have limitations.
- The Blumgart's anastomosis (BA) technique shows promise in reducing fistula rates.
Purpose of the Study:
- To introduce and evaluate a novel Blumgart-type modification of WPGA (B-WPGA).
- To assess the safety and efficacy of B-WPGA in reducing POPF and delayed post-pancreatectomy hemorrhage (DPH).
Main Methods:
- A prospective development study involving 15 patients undergoing pancreaticoduodenectomy.
- Application of the B-WPGA technique, involving specific U-stitch placement and gastric submucosa protection.
- Standardized postoperative follow-up including pancreatic enzyme checks.
Main Results:
- No operative mortality or pancreatic anastomosis-related morbidity observed.
- Two cases (13%) of transiently elevated drain amylase, not meeting POPF criteria.
- Zero DPH events recorded with a minimum follow-up of 18.6 months.
Conclusions:
- The principles of BA can be safely applied to the WPGA model.
- B-WPGA facilitates gentle duct closure, protects the pancreatic remnant, and prevents parenchymal fractures.
- The technique shows promise, supporting further investigation in larger studies.