Related Experiment Video
Updated: Nov 6, 2025


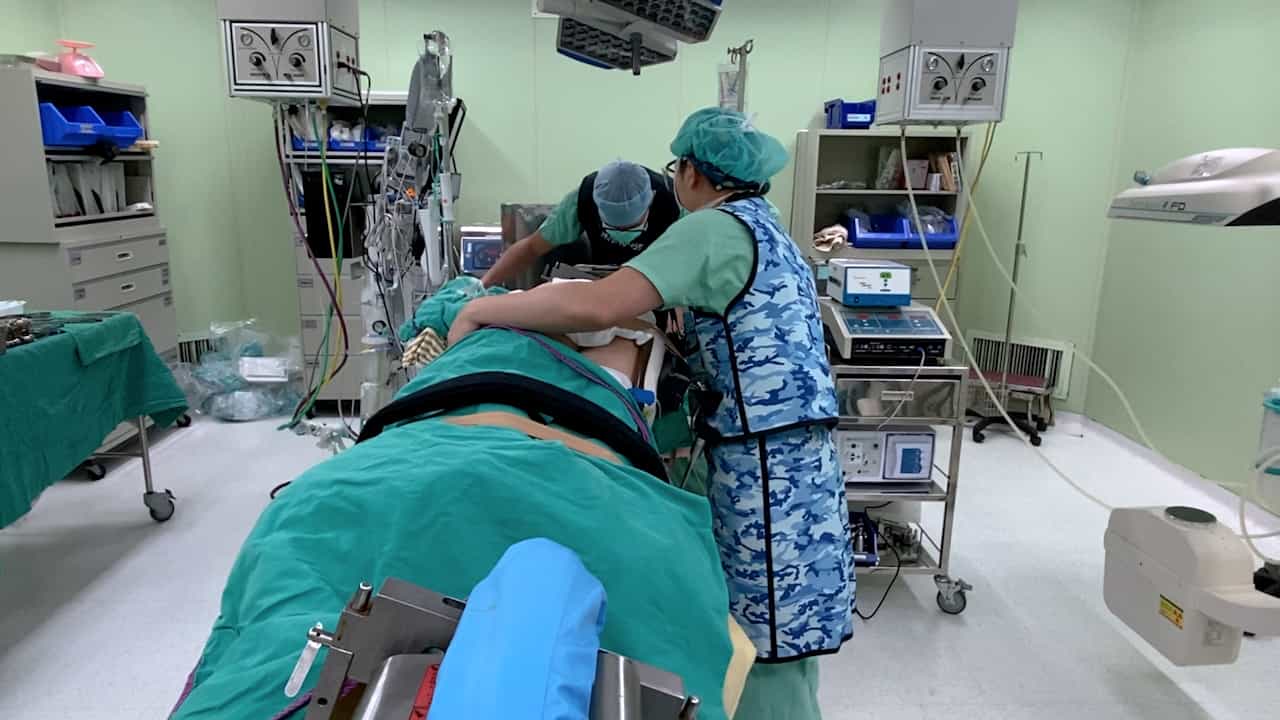
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Conservative versus invasive management of secondary spontaneous pneumothorax: a retrospective cohort study
Benjamin Carl Gerhardy1, Graham Simpson1
1Department of Respiratory Medicine Cairns Hospital Cairns QLD Australia.

Aim:
Hospitalization, often with intervention, is the recommended management algorithm by multiple international respiratory societies for management of a secondary spontaneous pneumothorax (SSP). Over recent years we adopted a conservative approach to SSPs. We undertook a retrospective cohort study of SSP to establish the safety profile of a conservative approach for these previously unstudied patients.
Methods:
We reviewed all cases of SSP presenting to our institution from 2012 to 2019 using the 2010 British Thoracic Society definition of an SSP. Age, gender, smoking status, underlying lung disease, pneumothorax size estimate (using the Collins method), nature of intervention, inpatient duration, and any additional complications were recorded. The χ2-test and Mann-Whitney U-test were used for comparison of categorical variables and categorical/continuous variables, respectively.
Results:
Eighty-two cases were included in the final analysis. Of them, 64 had an interpleural distance at the hilum of 1cm or greater, meeting British Thoracic Society criteria for a pleural intervention. Of these 64 patients, 25 (39%) were managed conservatively. No patient managed conservatively required a subsequent intervention. When stratified for conservative or invasive management, there was no significant difference in age, gender, smoking status, or presence of underlying lung disease between the groups. There was a significant difference in size of the pneumothorax with conservative management having smaller pneumothoraces (37% versus 54%, P < 0.001) and a shorter inpatient stay (conservative, 7.9 days; intercostal catheter, 9 days; P = 0.004).
Conclusion:
We have demonstrated success with conservative management of SSPs where a significant proportion of them met accepted criteria for a pleural intervention.
More Related Videos

Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations: