Adherence to cardiovascular pharmacotherapy by patients in Iraq: A mixed methods assessment using quantitative dried blood spot analysis and the 8-item Morisky Medication Adherence Scale
Related Experiment Video
Updated: Nov 5, 2025

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Ahmed Alalaqi1, Graham Lawson1, Yaseen Obaid2
1Leicester School of Pharmacy, Faculty of Health and Life Sciences, De Montfort University, Leicester, United Kingdom.

Abstract:
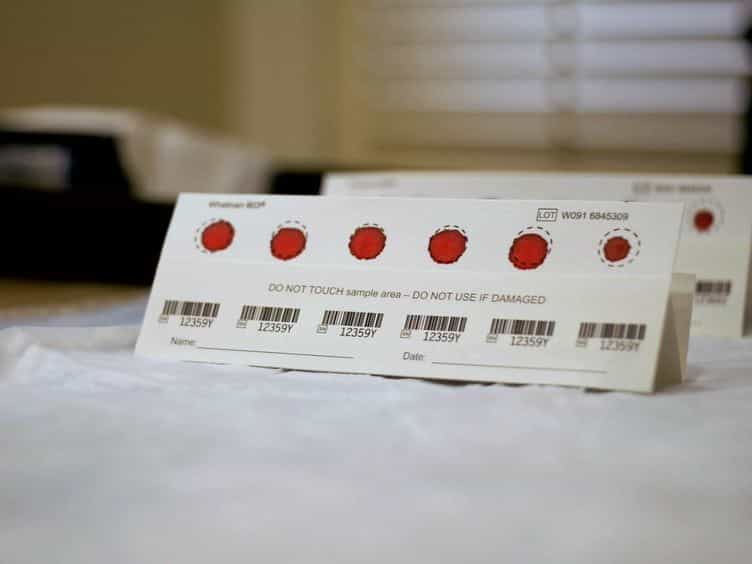
This study evaluated the adherence to prescribed cardiovascular therapy medications among cardiovascular disease patients attending clinics in Misan, Amara, Iraq. Mixed methods were used to assess medication adherence comprising the Arabic version of the eight-item Morisky Medication Adherence Scale (MMAS-8) and determination of drug concentrations in patient dried blood spot (DBS) samples by liquid chromatography-high resolution mass spectrometry. Three hundred and three Iraqi patients (median age 53 years, 50.5% female) who had been taking one or more of the nine commonly prescribed cardiovascular medications (amlodipine, atenolol, atorvastatin, bisoprolol, diltiazem, lisinopril, losartan, simvastatin and valsartan) for at least six months were enrolled. For each patient MMAS-8 scores were determined alongside drug concentrations in their dried blood spot samples. Results from the standardized questionnaire showed that adherence was 81.8% in comparison with 50.8% obtained using the laboratory-based microsample analysis. The agreement between the indirect (MMAS-8) and direct (DBS analysis) assessment approaches to assessing medication adherence showed significantly poor agreement (kappa = 0.28, P = 0.001). The indirect and direct assessment approaches showed no significant correlation between nonadherence to prescribed cardiovascular pharmacotherapy and age and gender, but were significantly associated with the number of medications in the patient's treatment regimen (MMAS-8: Odds Ratio (OR) 1.947, 95% CI, P = 0.001; DBS analysis: OR 2.164, 95% CI, P = 0.001). The MMAS-8 results highlighted reasons for nonadherence to prescribed cardiovascular pharmacotherapy in this patient population whilst the objective DBS analysis approach gave valuable information about nonadherence to each medication in the patient's treatment regimen. DBS sampling, due its minimally invasive nature, convenience and ease of transport is a useful alternative matrix to monitor adherence objectively in Iraq to cardiovascular pharmacotherapy. This information combined with MMAS-8 can provide clinicians with an evidence-based novel approach to implement intervention strategies to optimise and personalise cardiovascular pharmacotherapy in the Iraqi population and thereby improve patient health outcomes.

Related Concept Videos
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:26
Therapeutic Drug Monitoring: Drug Analysis Methods
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.