Related Experiment Video
Updated: Nov 5, 2025

Technical Refinement of a Bilateral Renal Ischemia-Reperfusion Mouse Model for Acute Kidney Injury Research
Published on: November 3, 2023
Factors associated with non-survival from in-hospital maternal cardiac arrest: An analysis of Get With The
Carolyn M Zelop1, Richard E Shaw2, Dana P Edelson3
1Division of Maternal-Fetal Medicine, Department of Obstetrics and Gynecology, The Valley Hospital, Ridgewood, NJ, USA; Department of Obstetrics and Gynecology, New York University School of Medicine, New York, NY, USA.

Introduction:
Maternal mortality has risen in the United States during the 21st century. Factors influencing outcome of maternal cardiac arrest (MCA) remain largely unexplored.
Objective:
We sought to further elucidate the factors affecting maternal death from in-hospital (IH) MCA.
Methods:
Our query of the American Heart Association's GWTG®-Resuscitation voluntary registry from 2000-2017 revealed 561 index cases of IH MCA with complete outcome data. Logistic regression was performed using hospital death as the primary outcome and included variables with a p value = 0.1 or less based upon univariate analysis. Age, race, year of arrest, pre-existing conditions, first documented pulseless rhythm and location of arrest were used in the model. Sensitivity analyses and assessment of variable interaction were also performed to test model stability. Institutional review deemed this research exempt from ethical approval.
Results:
Among 561 cases of MCA, 57.2% (321/561) did not survive to hospital discharge. IH death was not associated with maternal age, race and year of event. In the final model, IH death was significantly associated with pre-arrest hypotension/hypoperfusion (OR = 1.80 (95% CI, 1.16-2.79); p = 0.009). The occurrence of MCA outside of the delivery suite (referent group) or operating room was associated with a significantly higher risk of death: ICU/Post-Anesthesia Care Unit (PACU) (OR = 3.32 (95% CI, 2.00-5.52); p < 0.001) and ER/other (OR = 1.89 (95% CI, 1.15-3.11); p = 0.012). While MCA cases with a shockable vs. non-shockable first documented pulseless rhythm had similar outcomes, those with an indeterminate rhythm were less likely to die, (OR = 0.41(95% CI, 0.20-0.84); p = 0.014). In a sensitivity analysis, removal of the indeterminate group did not alter outcomes regarding first documented pulseless rhythm or arrest location. Area under the curve for the final model was 0.715 (95% CI 0.673-0.757).
Conclusions:
Our study identified several novel factors associated with IH death of our MCA cohort. More research is required to further understand the pathophysiologic dynamics affecting outcomes of IH MCA in this unique population.
More Related Videos
 05:36
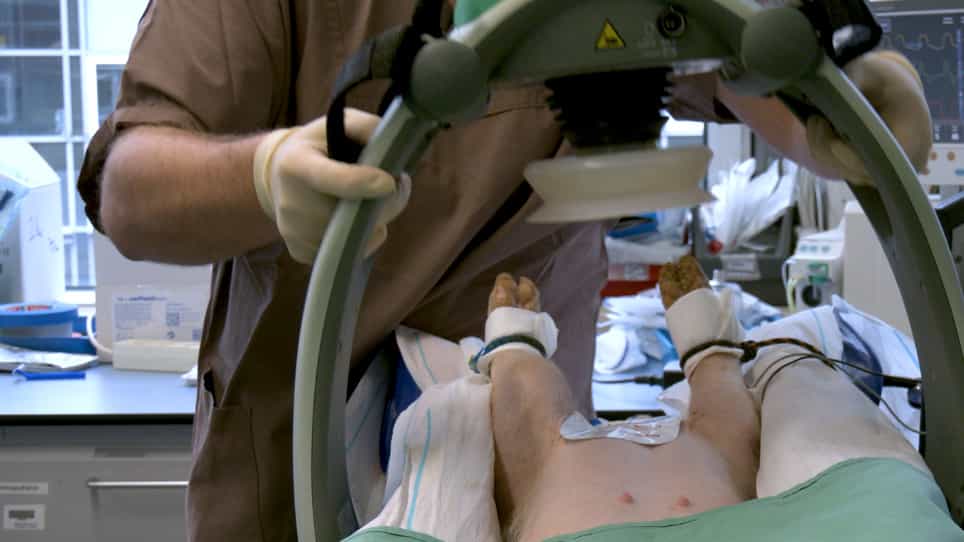
Standardized Model of Ventricular Fibrillation and Advanced Cardiac Life Support in Swine
Published on: January 30, 2020
 05:41
Left Anterior Descending Coronary Artery Ligation for Ischemia-Reperfusion Research: Model Improvement via Technical Modifications and Quality Control
Published on: December 16, 2022
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:30
Introduction Cardiac Emergencies
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:26
Acute Coronary Syndrome V: Nursing Management
 01:28
Acute Coronary Syndrome IV: Interprofessional Care