Related Experiment Video
Updated: Aug 15, 2026


Intravascular Delivery of Biologics to the Rat Kidney
Published on: September 1, 2016
Atheromatous renal disease

Insights
Atheromatous renal disease, often overlooked, causes severe renal failure through artery stenosis and cholesterol embolism. Early diagnosis via angiography and biopsy is crucial for timely intervention and better outcomes.
Area of Science:
- Nephrology
- Cardiovascular Medicine
- Pathology
Background:
- Atherosclerosis is a significant risk factor for cardiovascular disease.
- Renal failure can be a consequence of systemic vascular disease.
- The role of atheromatous disease in renal failure is often underestimated.
Purpose of the Study:
- To investigate the incidence and characteristics of atheromatous renal disease.
- To highlight the diagnostic challenges and therapeutic implications of this condition.
Main Methods:
- Retrospective analysis of 32 patients with renal failure and atheromatous renal disease over 12 years.
- Evaluation included clinical data, hypertension history, and renal function markers (serum creatinine).
- Diagnostic procedures involved angiography and renal biopsy in selected cases.
Main Results:
- Atheromatous renal disease was the primary cause of renal insufficiency in 22 cases, mainly due to renal artery stenosis.
- Cholesterol crystal embolism was confirmed in renal biopsies and clinically in additional cases.
- Complex intrarenal lesions and progression of stenoses were observed, often precluding surgical or interventional treatment.
Conclusions:
- Atheromatous renal disease is a frequent, yet overlooked, cause of chronic renal insufficiency.
- The condition involves both renal artery stenosis and intrarenal vascular pathology, including cholesterol embolism.
- Early diagnosis through angiography and biopsy is recommended before advanced complications arise, enabling potential surgical intervention.
Purpose:
Atheroma as a cause of renal failure has been largely overlooked. We wanted to report our experience with atheromatous renal disease over a 12-year period.
Patients And Methods:
Observations on 32 cases of various forms of renal failure in patients with atheromatous renal disease are presented. These patients had been hypertensive for an average of 10.2 +/- 9.2 years. The length of deterioration was an average of 17 months, and at presentation renal insufficiency was severe, with serum creatinine levels of (mean +/- SD) 616 +/- 358 mumol/liter (6.8 +/- 4.0 mg/dl). At this stage, the clinical picture was indistinguishable from other common causes of chronic renal failure in the elderly. Thus, the precise diagnosis would have been overlooked without an aggressive diagnostic workup. All patients underwent angiography and six patients underwent renal biopsy.
Results:
In 22 cases, renal insufficiency was mainly due to atheromatous stenosis of renal arteries. In six of six patients, the results of renal biopsy showed cholesterol crystal embolism. In four additional cases, there was clinical or histologic evidence of extrarenal cholesterol embolism. In eight, renal artery plaques coexisted with cholesterol embolism. In two patients, renal failure was due only to cholesterol embolism. Renal atheromatous stenoses were developing, as shown on serial angiographies performed in five cases. In seven cases, stenoses involved both the main trunks of renal arteries and several intrarenal branches of too small a diameter to allow reconstructive surgery or percutaneous transluminal angioplasty. In addition, the general condition of most patients was so poor as to preclude surgery. Dialysis was begun in 11 patients, four other patients died, and renal failure was managed conservatively in 11. When undertaken, reconstructive surgery was successful in five of six patients.
Conclusions:
Atheromatous renal disease is a frequent and easily overlooked cause of chronic renal insufficiency. It is not only due to renal artery stenosis but also to complex intrarenal lesions, with multiple stenoses of intrarenal vasculature and cholesterol embolism. It should be diagnosed by early angiography and renal biopsy, before the stage of multivisceral complications and at a time when surgery can still be undertaken.


Related Concept Videos
 01:21
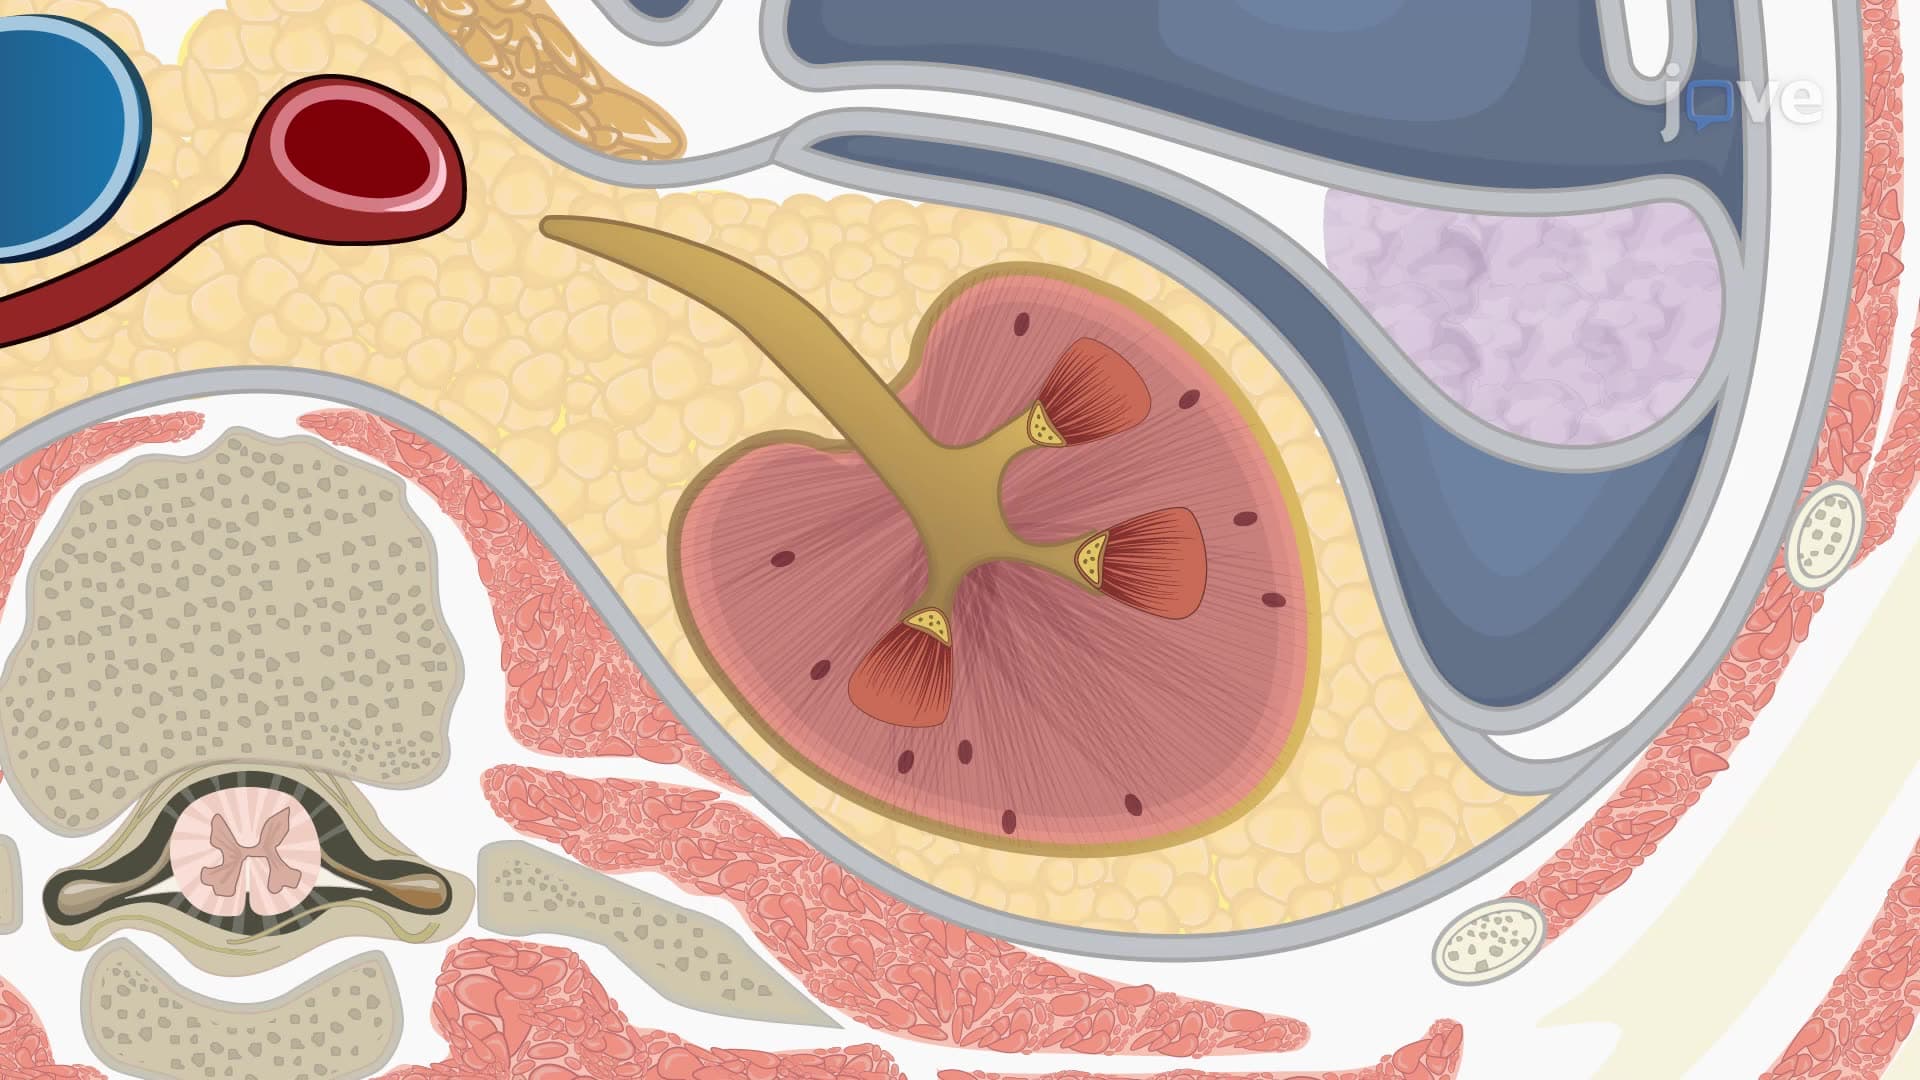
External Anatomy of the Kidney
The kidneys are located in the retroperitoneal space on either side of the vertebral column, protected posteriorly by the 11th and 12th ribs. The right kidney sits slightly lower than the left owing to the presence of the liver...
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous capillaries...
 01:30
Peripheral Artery Disease I: Introduction
 01:25
Chronic Kidney Disease I: Introduction
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:28
Diabetic Nephropathy