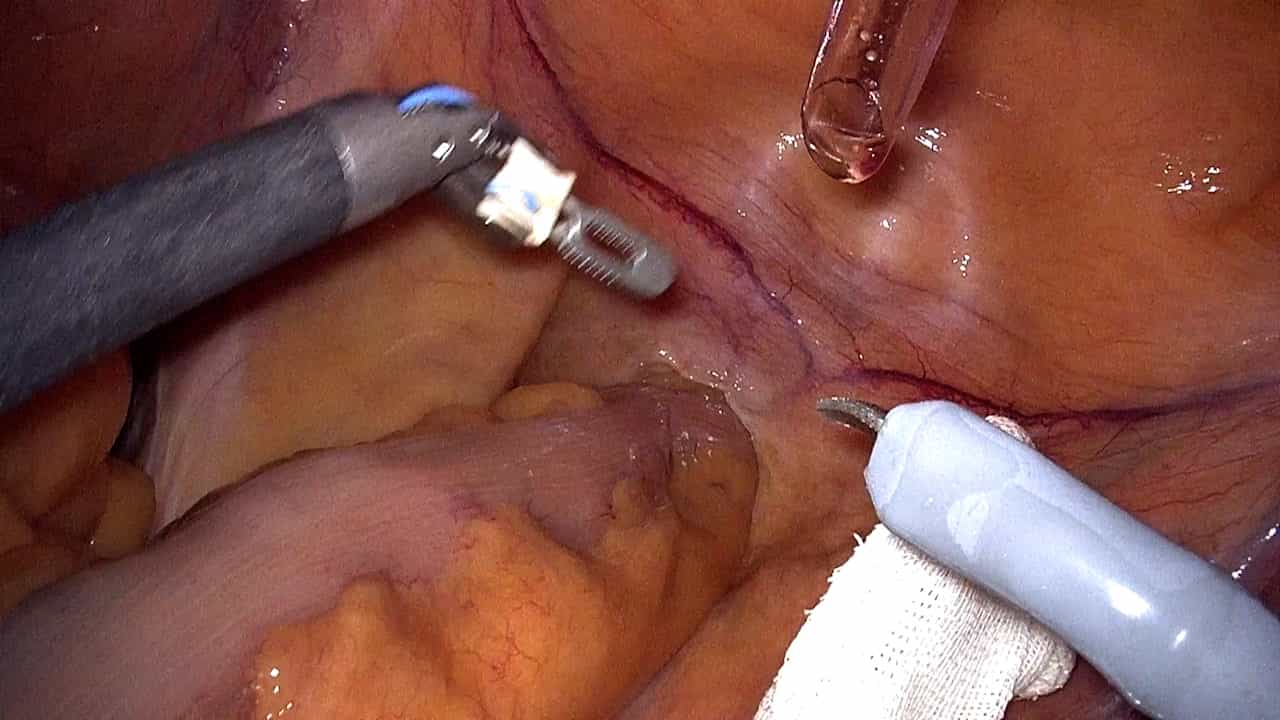
Related Experiment Video
Updated: Nov 5, 2025


Retzius-Sparing Robot-Assisted Radical Prostatectomy
Published on: May 19, 2022
Intra-corporeal robot-assisted versus open radical cystectomy: a propensity score-matched analysis comparing
Kenji Zennami1, Makoto Sumitomo2, Kiyoshi Takahara2
1Department of Urology, Fujita Health University School of Medicine, 1-98 Dengakugakubo, Kutsukake-cho, Toyoake, Aichi, 470-1192, Japan. zenken@fujita-hu.ac.jp.

Background:
To compare perioperative and long-term oncological outcomes and recurrence patterns between robot-assisted radical cystectomy with intra-corporeal urinary diversion (iRARC) and open radical cystectomy (ORC).
Methods:
We retrospectively analyzed 177 bladder cancer patients who received iRARC or ORC at Fujita Health University between 2008 and 2020. Our primary endpoint was long-term oncological outcomes. As a secondary endpoint, we examined perioperative outcomes, complications, and recurrence patterns. These outcome measures were compared between the propensity score (PS)-matched cohorts.
Results:
PS-matched analysis resulted in 60 matched pairs from iRARC and ORC groups. The iRARC cohort was associated with significantly longer operative time (p = 0.02), lower estimated blood loss (p < 0.001), lower blood transfusion rate (p < 0.001), shorter length of hospital stay (p < 0.001), fewer overall complications (p = 0.03), and lower rate of postoperative ileus (p = 0.02). There was no statistically significant difference between iRARC and ORC in 5-year RFS (p = 0.46), CSS (p = 0.63), and OS (p = 0.71). RFS and CSS were also comparable, even in locally advanced (≥ cT3) disease. Multivariate analysis identified lymphovascular invasion as a robust predictor of RFS, CSS, and OS. The number of recurrence was similar between the groups, while extra-pelvic lymph nodes were more frequent in iRARC than that in ORC (22.7% vs. 7.7%).
Conclusions:
iRARC has favorable perioperative outcomes, fewer complications, and comparable long-term survival outcomes, including locally advanced (≥ cT3) disease, compared to that in ORC. Our results need to be validated in prospective randomized clinical trials.