Related Experiment Video
Updated: May 5, 2026
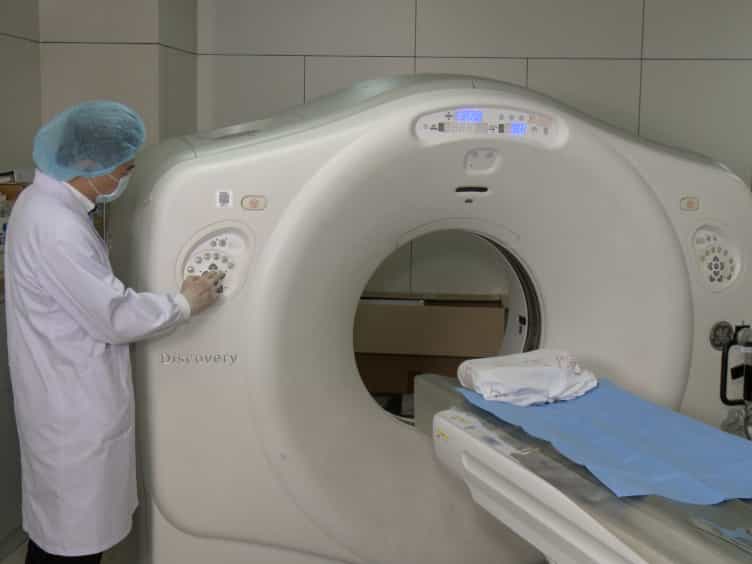
Gene Regulation and Targeted Therapy in Gastric Cancer Peritoneal Metastasis: Radiological Findings from Dual Energy CT and PET/CT
Published on: January 22, 2018
Chemotherapy de-escalation using an 18F-FDG-PET-based pathological response-adapted strategy in patients with
José Manuel Pérez-García1, Geraldine Gebhart2, Manuel Ruiz Borrego3
1International Breast Cancer Center, Quiron Group, Barcelona, Spain; Medica Scientia Innovation Research, Barcelona, Spain; Medica Scientia Innovation Research, Ridgewood, NJ, USA.

Background:
Several de-escalation approaches are under investigation in patients with HER2-positive, early-stage breast cancer. We assessed early metabolic responses to neoadjuvant trastuzumab and pertuzumab using 18F-fluorodeoxyglucose (18F-FDG)-PET (18F-FDG-PET) and the possibility of chemotherapy de-escalation using a pathological response-adapted strategy.
Methods:
We did a multicentre, randomised, open-label, non-comparative, phase 2 trial in 45 hospitals in Spain, France, Belgium, Germany, the UK, Italy, and Portugal. Eligible participants were women aged 18 years or older with centrally confirmed, HER2-positive, stage I-IIIA, invasive, operable breast cancer (≥1·5 cm tumour size) with at least one breast lesion evaluable by 18F-FDG-PET, an Eastern Cooperative Oncology Group performance status of 0 or 1, and a baseline left ventricular ejection fraction of at least 55%. We randomly assigned participants (1:4), via an interactive response system using central block randomisation with block sizes of five, stratified by hormone receptor status, to either docetaxel (75 mg/m2 intravenous), carboplatin (area under the concentration-time curve 6 mg/mL per min intravenous), trastuzumab (subcutaneous 600 mg fixed dose), and pertuzumab (intravenous 840 mg loading dose, 420 mg maintenance doses; group A); or trastuzumab and pertuzumab (group B). Hormone receptor-positive patients allocated to group B were additionally given letrozole if postmenopausal (2·5 mg/day orally) or tamoxifen if premenopausal (20 mg/day orally). Centrally reviewed 18F-FDG-PET scans were done before randomisation and after two treatment cycles. Patients assigned to group A completed six cycles of treatment (every 3 weeks) regardless of 18F-FDG-PET results. All patients assigned to group B initially received two cycles of trastuzumab and pertuzumab. 18F-FDG-PET responders in group B continued this treatment for six further cycles; 18F-FDG-PET non-responders in this group were switched to six cycles of docetaxel, carboplatin, trastuzumab, and pertuzumab. Surgery was done 2-6 weeks after the last dose of study treatment. Adjuvant treatment was selected according to the neoadjuvant treatment administered, pathological response, hormone receptor status, and clinical stage at diagnosis. The coprimary endpoints were the proportion of 18F-FDG-PET responders in group B with a pathological complete response in the breast and axilla (ypT0/is ypN0) as determined by a local pathologist after surgery after eight cycles of treatment, and 3-year invasive disease-free survival of patients in group B, both assessed by intention to treat. The definitive assessment of pathological complete response was done at this primary analysis; follow-up to assess invasive disease-free survival is continuing, hence these data are not included in this Article. Safety was assessed in all participants who received at least one dose of study drug. Health-related quality-of-life was assessed with EORTC QLQ-C30 and QLQ-BR23 questionnaires at baseline, after two cycles of treatment, and before surgery. This trial is registered with EudraCT (2016-002676-27) and ClinicalTrials.gov (NCT03161353), and is ongoing.
Findings:
Between June 26, 2017, and April 24, 2019, we randomly assigned 71 patients to group A and 285 to group B. Median follow-up was 5·7 months (IQR 5·3-6·0). 227 (80%) of 285 patients in group B were 18F-FDG-PET responders, of whom 86 (37·9%, 95% CI 31·6-44·5; p<0·0001 compared with the historical rate) of 227 had a pathological complete response. The most common haematological grade 3-4 adverse events were anaemia (six [9%] of 68 patients in group A vs four [1%] of 283 patients in group B), neutropenia (16 [24%] vs ten [4%]), and febrile neutropenia (14 [21%] vs 11 [4%]). Serious adverse events occurred in 20 (29%) of 68 patients in group A versus 13 (5%) of 283 patients in group B. No deaths were reported during neoadjuvant treatment. Global health status declined by at least 10% in 65·0% (95% CI 46·5-72·4) and 35·5% (29·7-41·7) of patients in groups A and B, respectively INTERPRETATION: 18F-FDG-PET identified patients with HER2-positive, early-stage breast cancer who were likely to benefit from chemotherapy-free dual HER2 blockade with trastuzumab and pertuzumab, and a reduced impact on global health status. Depending on the forthcoming results for the 3-year invasive disease-free survival endpoint, this strategy might be a valid approach to select patients not requiring chemotherapy.
Funding:
F Hoffmann-La Roche.
More Related Videos
 10:27
Testing Targeted Therapies in Cancer using Structural DNA Alteration Analysis and Patient-Derived Xenografts
Published on: July 25, 2020
 12:41
Multiparametric Tumor Organoid Drug Screening Using Widefield Live-Cell Imaging for Bulk and Single-Organoid Analysis
Published on: December 23, 2022
